Neurodiversity affirming Speech and Language Therapy

| |

Introduction

I am a neurodiversity affirming therapist and I love and endorse play-based therapy. I use it alongside a strengths-focused approach in all my sessions. Find out why we should use these transformative therapy methodologies in all our work and play with our children.

I always have a range of different toys and activities up my sleeve so that when one toy is no longer interesting, that’s fine. ‘Look here’s a new one, how about we try this one?’ When therapy feels like play, children are more likely to be engaged and attentive, which leads to better outcomes.

By using play as a context for Speech and Language Therapy we can create opportunities for children to use and practise their communication skills in a natural, real-life setting. This helps bridge the gap between the therapy room and everyday life.

Goals and targets

What about goals and targets I hear you say? Of course, as Speech and Language Therapists we always have our goals for any particular child. They can be speech goals (we want Bobbi to produce a ‘k’ sound at the end of words) or communication goals (we want Fatima to ask for something by pointing to it rather than grabbing it). And these goals can be achieved where there is a reciprocation and a positive, playful relationship between the adult and the child. That relationship comes through play and fun.

Play and fun

Play is how a child interacts and learns. If it’s fun, interesting, exciting or pleasurable then that is where the magic happens. And that is what we need to return to repeatedly and then see if we can fold our targets into the activity as we go.

As soon as we expect our child to do something and we try and shape their behaviours towards a certain outcome we no longer ‘play’. We are now in teaching mode, where we direct and where we are ‘in charge’. As a neurodiversity affirming therapist, I believe that all play is valid. We must not get into the trap of thinking that only functional play is valid, that there is only one way to play with that car ramp/puzzle/potato head. Our autistic children often need to play in a particular way to navigate their world and we must not try and stop that.

When we affirm and validate our child’s play and copy their play with enthusiasm and respect then, in my experience, all children regardless where they are on the neurodiversity spectrum will begin to engage with us, copy us, and learn how to communicate effectively about things that matter to them.

Play-based therapy allows therapists to tailor interventions to each child’s unique interests and abilities. This individualised approach increases the likelihood of success and progress.

Strengths-Focused Speech Therapy

Strengths-focused therapy emphasizes a child’s strengths and abilities rather than their deficits. It recognises that every person has unique strengths that can be harnessed to overcome challenges.

Focusing on strengths helps us build a positive self-image. This is especially important for children with communication disorders, as it can boost their confidence and self-esteem.

When we encourage children to play in ways that they enjoy and are good at they feel empowered and more in control of their lives and play. This can lead to increased motivation and a sense of ownership over their progress.

Now, imagine the powerful impact that can be achieved by combining play-based therapy and strengths-focused therapy in speech therapy sessions. This dynamic combination brings out the best of both worlds. It creates a therapeutic environment that is not only effective but also enjoyable for children and their families.

As Speech Therapists we can use the child’s strengths and interests as a foundation for play-based activities. This personalisation not only makes therapy more engaging but also more effective.

An example

Charlie, a 3-year-old with social communication challenges, had a deep interest in anything that spins. We used this strength and interest to create a variety of spinning activities. As he is allowed to engage in his spinners, we can practise lots of speech and language and provide great phrases alongside his interest and activities: Ready steady go! Stop! ‘another one’ ‘the red one’ ‘again again’ ‘I love it’ ‘it’s a spinner’ ‘Charlie loves this toy’ ‘it’s going fast’ ‘it’s so fun’ etc..

Over time Charlie started to copy some of these word models and then used them to create his own little phrases, such as ‘the blue one again’. When this occurred, we felt like celebrating because it had come naturally and appropriately to the situation without any coercion or direction. That is what communication is about! Well done Charlie!

Conclusion

Play-based and strengths-focused speech therapy approaches are powerful tools and by combining these approaches, we create a therapeutic environment that is not only effective but also enjoyable and empowering for our clients.

Contact me if you would like your child to have neurodiversity affirming speech and language therapy.


Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

0

Similar Posts

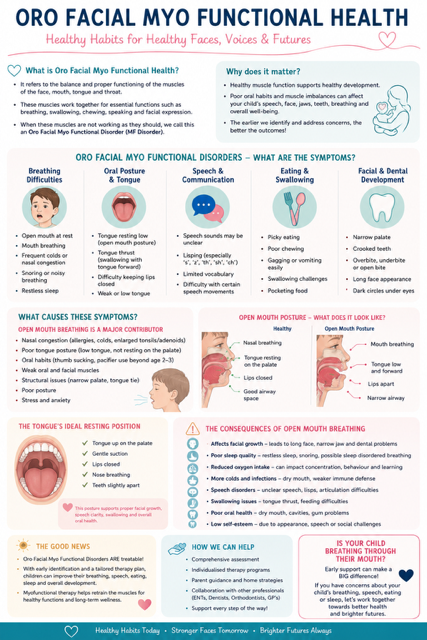
  • Could mouth breathing be affecting your child’s speech, sleep and development?

    Could mouth breathing be affecting your child's speech, sleep and development?

    Understanding Orofacial Myofunctional Disorders (OMDs)

    Many parents contact me at London Speech and Feeding because they are worried about their child’s speech. Perhaps their child is difficult to understand, has a persistent lisp, struggles with feeding, snores at night, or always seems to have their mouth open.

    What many families don’t realise is that these concerns may all be connected.

    Increasingly, research and clinical experience are highlighting the important role of Orofacial Myofunctional Health, the way the muscles of the face, mouth, tongue and airway work together to support breathing, eating, sleeping and communication.

    When these muscles are not functioning optimally, children may develop what are known as Orofacial Myofunctional Disorders (OMDs).

    What Is Orofacial Myofunctional Health?

    Orofacial Myofunctional Health refers to the healthy function and coordination of the:

    • lips
    • tongue
    • jaw
    • cheeks
    • facial muscles
    • airway.

    These structures play a vital role in:

    • breathing
    • swallowing
    • chewing
    • speaking
    • facial growth
    • dental development
    • sleep quality.

    When everything is working well, the lips remain gently closed at rest, breathing occurs through the nose, and the tongue rests against the roof of the mouth.

    This seemingly simple posture has a profound influence on how a child’s face, teeth and airway develop.

    What is an Orofacial Myofunctional Disorder?

    An Orofacial Myofunctional Disorder occurs when there is an abnormal pattern of muscle function involving the face, mouth, tongue or airway.

    Children with OMDs may experience difficulties with:

    • speech
    • feeding
    • swallowing
    • sleep
    • breathing
    • dental development
    • facial growth.

    In many cases, these difficulties are linked to chronic mouth breathing.

    Signs your child may have an Orofacial Myofunctional Disorder

    Breathing and sleep signs

    • mouth open at rest
    • mouth breathing during the day
    • snoring
    • noisy breathing
    • restless sleep
    • frequent waking
    • dark circles under the eyes
    • chronic congestion
    • fatigue despite a full night’s sleep.

    Speech signs

    • lisping
    • unclear speech
    • distorted speech sounds
    • difficulty producing certain sounds
    • persistent articulation difficulties
    • reduced speech intelligibility.

    Feeding and swallowing signs

    • picky eating
    • messy eating
    • food remaining in the cheeks
    • gagging easily
    • difficulty chewing
    • long mealtimes
    • tongue thrust swallowing.

    Facial and dental signs

    • narrow palate
    • crowded teeth
    • open bite
    • overbite
    • underbite
    • long face appearance
    • receding chin
    • poor lip seal.

    If several of these signs sound familiar, a comprehensive assessment may be worthwhile.

    Why does mouth breathing matter?

    Many parents assume mouth breathing is simply a habit.

    In reality, mouth breathing is often a symptom that something is preventing efficient nasal breathing.

    Common causes include:

    • enlarged tonsils
    • enlarged adenoids
    • allergies
    • chronic nasal congestion
    • recurrent infections
    • structural airway differences
    • tongue tie
    • prolonged dummy use
    • thumb sucking
    • poor oral posture.

    When nasal breathing becomes difficult, children naturally begin breathing through their mouths.

    Over time, this can affect how the face, jaws and airway develop.

    What does healthy oral posture look like?

    Healthy oral posture is surprisingly simple:

    • lips
      • gently closed
    • tongue
      • resting against the roof of the mouth
    • teeth
      • slightly apart
    • breathing
      • through the nose.

    This posture helps guide healthy jaw growth, facial development and airway formation.

    Think of the tongue as a natural orthodontic support system. When it rests in the correct position, it helps shape the upper jaw and supports healthy facial growth.

    The consequences of chronic mouth breathing

    1. Speech difficulties

    Children who breathe through their mouths often have altered tongue posture and reduced oral stability.

    This can contribute to:

    • lisping
    • distorted sounds
    • reduced speech clarity
    • difficulty learning new speech sounds.

    2. Feeding and swallowing difficulties

    A low tongue posture may affect:

    • chewing efficiency
    • swallowing patterns
    • food management
    • oral motor coordination.

    Many children develop a tongue thrust swallow, where the tongue pushes forward instead of moving efficiently during swallowing.

    3. Poor sleep quality

    Mouth breathing can contribute to:

    • snoring
    • restless sleep
    • frequent waking
    • daytime fatigue
    • reduced concentration.

    Poor sleep can have a significant impact on learning, behaviour and emotional regulation.

    4. Changes to facial growth

    Over time, chronic mouth breathing may influence:

    • jaw development
    • facial proportions
    • dental alignment
    • airway size.

    This can result in:

    • narrow palates
    • crowded teeth
    • long facial appearance
    • increased orthodontic needs.

    5. Oral health concerns

    The nose acts as a natural filter and humidifier.

    When children breathe through their mouths:

    • The mouth becomes dry.
    • Saliva protection is reduced.
    • Risk of tooth decay increases.
    • Gum health may be affected.

    Why this matters for speech therapy

    Speech does not develop in isolation.

    The tongue, lips, jaw and airway work together to support clear communication.

    At London Speech and Feeding, we look beyond speech sounds alone.

    A child who presents with:

    • persistent speech difficulties
    • lisping
    • feeding challenges
    • open mouth posture
    • snoring
    • poor sleep

    may benefit from an assessment that explores underlying orofacial myofunctional factors.

    Addressing these foundations can often support more effective progress in speech and feeding therapy.

    How London Speech and Feeding can help

    A comprehensive assessment may include observation of:

    • breathing patterns
    • lip posture
    • tongue posture
    • swallowing function
    • feeding skills
    • speech sound development
    • sleep concerns
    • oral structures.

    Where appropriate, recommendations may include:

    • orofacial myofunctional therapy
    • speech therapy
    • feeding therapy
    • home programmes
    • ENT referral
    • orthodontic referral
    • collaborative multidisciplinary support.

    The good news

    Orofacial Myofunctional Disorders are often highly treatable when identified early.

    Supporting healthy breathing, tongue posture and oral muscle function can positively influence:

    If your child regularly breathes through their mouth, snores, struggles with speech clarity or has feeding difficulties, a specialist assessment may help identify the underlying cause.

    • speech clarity
    • feeding skills
    • sleep quality
    • facial growth
    • dental development
    • overall wellbeing.

    At London Speech and Feeding, we are passionate about looking beyond symptoms and understanding the whole child. Contact me!

    Sometimes the key to clearer speech starts with a simple question:

    ‘Is my child breathing through their nose?’

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.

    Frequently Asked Questions

    Can mouth breathing cause speech problems?

    Yes. Mouth breathing can alter tongue posture, lip strength and oral stability, which may contribute to articulation difficulties and lisps.

    Should I be worried if my child snores?

    Regular snoring is not considered normal in children and may indicate airway obstruction or sleep-disordered breathing.

    Can enlarged tonsils affect speech?

    Yes. Enlarged tonsils may affect resonance, tongue positioning, swallowing and breathing patterns.

    What age can children be assessed?

    Children of all ages can be assessed if parents have concerns about speech, feeding, breathing or oral development.

    What is Orofacial Myofunctional Therapy?

    Orofacial Myofunctional Therapy focuses on improving breathing patterns, tongue posture, lip seal and oral muscle function to support overall health and development.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • · · ·

    The quiet power: Why silence and responsiveness boost communication in children with delays

    The quiet power: Why silence and responsiveness boost communication in children with delays
    Supplied by Sonja McGeachie, Practice Owner

    As parents and caregivers, our natural instinct when interacting with a child, especially one who struggles with communication, is often to fill every silence. We might ask lots of questions, offer constant commentary, or try to prompt him or her to speak. Our hearts are in the right place. We want to help him or her communicate! However, for children with language delays or those on the autism spectrum, this well-intentioned approach can sometimes inadvertently create more pressure and fewer opportunities for them to truly initiate and develop their own communication skills.

    What if I told you that one of the most powerful tools in your communication toolkit is often silence? And that responding to your child, rather than always initiating, can unlock incredible potential?

    Let’s explore why these seemingly simple strategies are so profoundly beneficial.

    The unspoken benefits of silence

    In our fast-paced world, silence can feel awkward, but for a child who is processing language differently, it’s a gift:

    1. Time to process: Children with language delays often need more time to process what they hear and to formulate their own thoughts or responses. When we bombard them with words, we don’t give their brains the crucial milliseconds they need to catch up. A pause of 5–10 seconds can make all the difference.
    2. Reduces pressure: Constant questioning or prompting can feel like a test. Silence removes this pressure, creating a more relaxed environment where the child feels safe to communicate without fear of being ‘wrong’ or rushed.
    3. Creates opportunity to initiate: If you’re always talking, when does your child get a turn to start the conversation? Silence opens up a space for him or her to initiate, whether it’s through a sound, a gesture, eye contact, or a word. This is vital for developing spontaneous communication.
    4. Encourages independent thinking: When a child is given space, he or she is more likely to try to figure things out himself or herself. This fosters problem-solving skills and reduces reliance on adult prompts.
    5. Prevents overwhelm (especially for ASD): Many children on the autism spectrum can be sensitive to auditory input. A constant stream of language can be overwhelming, leading to withdrawal or challenging behaviours. Strategic pauses can help them regulate and engage more effectively.

    The power of responding (not just initiating)

    Think of a tennis match: if only one person serves, it’s not a game. Communication is a rally, a back-and-forth exchange. When you primarily respond to your child’s communication attempts, you’re teaching him or her the rhythm of conversation:

    1. Follow the child’s lead: This is a cornerstone of effective language intervention, famously championed by programs like Hanen’s ‘It Takes Two to Talk’. When you respond to what your child is already interested in or doing, the interaction becomes immediately relevant and motivating for him or her.
    2. Validates his or her attempts: Every sound, gesture, glance, or partial word your child offers is a communication attempt. By responding to it, you’re telling him or her, ‘I see you. I hear you. Your communication matters.’ This builds immense confidence and encourages him or her to try again.
    3. Builds confidence and motivation: When a child feels understood and successful in his or her communication, he or she are more likely to communicate more often. It’s a positive feedback loop.
    4. Teaches turn-taking naturally: By taking your turn after his or hers, you model the natural flow of conversation. He or she learns that communication is a shared activity, not a one-sided lecture.
    5. Makes interactions meaningful: When you respond to his or her interests, you’re talking about things that are inherently motivating to him or her. This makes the language you use more easily understood and remembered.

    Practical strategies for parents: Observe, Wait, Listen (OWL)

    The Hanen Centre’s ‘Observe, Wait, Listen’ (OWL) strategy perfectly encapsulates these principles:

    • Observe: Watch your child closely. What is he or she looking at? What is he or she doing? What sounds is he or she making? What gestures is he or she using?
    • Wait: After you’ve observed, wait. Give him or her time. Resist the urge to jump in with a question or comment immediately. Count to five (or even ten) in your head. This silence is an invitation for him or her to communicate.
    • Listen: When he or she does communicate (in any way!), listen intently. Try to understand his or her message or intent.

    Beyond OWL – More tips:

    • Reduce questions, increase comments: Instead of ‘What’s that?’ try ‘Oh, a big red ball!’ or ‘The car is going fast!’ Comments provide language models without demanding a verbal response.
    • Expand, don’t just prompt: If your child says ‘Car’, you could respond with ‘Yes, That’s a big car!’ or ‘It’s really fast!’ You’re building on his or her communication with a slightly richer language model.
    • Create opportunities for communication: Place desired items slightly out of reach. This creates a natural reason for your child to communicate his or her wants (e.g., reaching, pointing, vocalising).
    • Respond to all communication: Don’t just wait for words. If your child points, look where he or she is pointing and comment. If he or she makes a sound, imitate it or respond with a related word.

    In summary

    Embracing silence and prioritising responsiveness might feel counterintuitive at first, especially when you’re eager for your child to talk. However, these powerful strategies create a nurturing, low-pressure environment that encourages spontaneous communication, builds confidence, and truly meets your child where he or she is. By giving your child the space and the meaningful responses he or she needs, you’re laying a strong foundation for his or her communication journey.

    Try incorporating these ‘quiet powers’ into your daily interactions and watch your child’s communication blossom.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • · ·

    Childhood Apraxia of Speech: Signs and first steps (2–5 years)

    If you’ve found yourself wondering ‘Why can my child say a word one day, but not at all the next?’ it might be that your child has a motor speech difficulty. This means the challenge isn’t that your child doesn’t know what they want to say; it’s that their brain finds it harder to plan and coordinate the movements needed for clear speech. This speech difficulty is called Childhood Apraxia of Speech (CAS)

    Sonja showing power words on a board

    In this post, I’ll explain what CAS can look like in 2–5 year olds, what an assessment usually involves, and what you can start doing at home to support your child without turning life into ‘speech homework all day long’.

    What is childhood apraxia of speech (CAS)?

    Children with CAS often have lots to communicate about (and strong ideas!) but their speech may come out as:

    • Unclear
    • inconsistent
    • hard to ‘copy’ on demand
    • frustrating for them and for you

    CAS is not caused by laziness and it is not a parenting issue. It is also not something children simply ‘grow out of’ without support. But with the right therapy approach, children can absolutely build clearer speech over time.

    If you’d like to read more about verbal dyspraxia, you may also find this helpful: Supporting children and families living with verbal dyspraxia.

    Why is CAS such a big topic right now?

    Many families come to me after months (or years) of being told:

    • ‘She’ll talk when she is ready’
    • ‘He’s just shy’
    • ‘It’s probably a speech delay’
    • ‘It’s normal for toddlers’

    And sometimes it is a general delay. But sometimes it’s something more specific, like CAS.

    There’s also been a huge rise in parents seeking information online, and CAS is often mentioned alongside speech sound difficulties such as:

    • phonological delay (pattern-based speech errors)
    • articulation difficulties (one sound that won’t come out clearly)
    • inconsistent speech disorder

    These can look similar at first glance, which is why a specialist assessment matters.

    Signs of childhood apraxia of speech in 2–5 year olds

    Children develop speech at different rates, and not every unclear speaker has CAS. But here are some common features that may raise a flag, especially when you notice several together.

    1) Inconsistent speech errors

    Your child might say the same word in different ways:

    • ‘banana’ → nana / baba / mana
    • ‘daddy’ → gaga / daddy / dadi

    This inconsistency is one of the biggest clues.

    2) Difficulty copying words on request

    Some children speak more easily in natural play, but when asked ‘Say ___’, they freeze or the word becomes much harder.

    3) Limited sound repertoire

    They may use only a small set of consonants (like /M/, /N/, /B/, /D/) and avoid others.

    4) Vowel distortions

    Many children with typical delays mainly struggle with consonants. But in CAS, vowels can also sound ‘off’ or change between attempts.

    5) Speech that sounds effortful

    You might notice your child:

    • pauses between sounds
    • tries multiple times
    • looks like they’re ‘searching’ for the right mouth movement

    6) Longer words are much harder

    ‘Car’ might be easier than ‘carry’, and ‘carry’ easier than ‘caterpillar’.

    7) Prosody differences (rhythm and stress)

    Some children with CAS sound a little unusual in their speech rhythm, stress, or intonation.

    8) Frustration or reduced confidence

    When a child is frequently misunderstood, they may:

    • talk less
    • use gestures more
    • become upset when asked to repeat themselves

    Important note: none of these signs alone prove CAS but they are a strong reason to seek a speech assessment rather than waiting.

    CAS vs phonological delay vs articulation difficulty (quick guide)

    These are some of the most common questions I hear.

    If it’s mainly an articulation difficulty…

    A child may consistently say one sound incorrectly (for example, ‘thun’ for ‘sun’- lisp- but everything else is developing well.

    If it’s mainly a phonological delay…

    You might notice clear patterns, like:

    • leaving off the ends of words (‘ca’ for ‘cat’)
    • swapping back sounds for front sounds (‘tar’ for ‘car’)

    Patterns are often consistent and respond well to phonology-based therapy.

    If it might be CAS…

    Speech often feels less predictable, harder to imitate, and more impacted by word length and complexity.

    If you’re unsure, that’s completely normal, and exactly why assessment matters.

    What happens in a CAS assessment?

    A high-quality speech assessment for possible CAS usually includes:

    1) Parent discussion and developmental history

    We talk about:

    • pregnancy and birth history (where relevant)
    • feeding history
    • early sounds and babbling
    • first words and how speech has progressed
    • family history of speech/language needs

    2) A speech sound assessment

    Your child might be shown pictures or play-based prompts so we can hear:

    • what sounds they can say
    • what they simplify
    • whether errors are consistent or inconsistent

    3) An oral-motor and movement check

    This isn’t about ‘strength’. It’s about coordination and planning. We look at how your child manages speech movements and transitions.

    4) Stimulability testing

    This means: how easily can your child learn a new sound or word with support?

    For CAS, we often explore how they respond to:

    • slowed-down speech
    • visual cues
    • rhythm/tapping
    • short, simple syllable shapes

    5) Functional communication and confidence

    We look at how speech impacts daily life:

    • being understood at nursery
    • joining in with peers
    • asking for help
    • managing emotions when misunderstood

    At the end, you should leave with:

    • a clear explanation of what we think is going on
    • a therapy plan
    • practical home strategies
    • realistic next steps

    What parents can do at home

    Here are CAS-friendly strategies you can start right away.

    1) Choose ‘power words’

    Pick 1–2 words that matter most in your child’s daily life, such as:

    • more
    • help
    • mummy
    • again
    • stop
    • open

    These words are motivating and functional.

    2) Keep it short and successful

    For many children with CAS, the goal is quality over quantity.

    Try five minutes a day rather than 30 minutes of struggle.

    3) Support speech with rhythm

    Some children benefit from:

    • tapping a beat on the table
    • clapping syllables
    • using a gentle ‘marching’ rhythm

    This can help the brain organise the sequence of movements.

    4) Celebrate approximations

    If your child says ‘moh’ for ‘more’, that’s communication!

    We want them to feel:

    • safe
    • understood
    • proud to try again

    Confidence is a key part of progress.

    A short parent story (anonymised)

    One mum said to me:

    ‘We kept being told to wait. But I could see my child understood everything; they just couldn’t get the words out. Once we had an assessment and a plan, it felt like we finally knew what to do. The biggest change was his confidence. He started trying more.’

    When should you seek support?

    You don’t need to wait until school.

    It’s worth getting an assessment if your child is:

    • hard to understand compared with peers
    • becoming frustrated or withdrawing from talking
    • inconsistent with words they used to say
    • struggling to imitate speech sounds
    • showing signs that match CAS

    Early support can reduce stress for the whole family and help your child feel successful in communication.

    Here’s how I can help:

    ✅ A detailed speech assessment (including whether CAS is likely)

    ✅ A clear therapy plan with realistic goals

    ✅ Practical home strategies you can use immediately

    ✅ Support for nurseries and schools (where needed)

    ✅ In-person sessions in North-West London and online options

    Book your consultation here.

    Final gentle reminder

    You are not overreacting. Trust your instincts.

    Your child is communicating the best way they can, and with the right support, speech can become easier, clearer, and more confident.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • Speech sound disorders

    Kids Speech Therapist London
    Speech Sound Disorders

    Treatment Approaches – A Typical Session

    There are various great ways to treat speech sound disorders and I use all the approaches available selectively; I decide what works with each individual child and I also vary the approach depending on the child’s frame of mind at any given time during my session.

    Some of the approaches are more “drill-based” and require a child to be able to pay attention and really participate actively in the therapy, and this is what I am showing you today with this video clip.

    My little student here has been working with me for some time and from only saying a handful of words which were not very easy to understand he has come a long way. He does have some features of Verbal Dyspraxia which I shall briefly outline here:

    • Making sounds in general is a struggle, especially when asked to copy certain sounds, example: ‘can you say: a ee ou oo?”
    • Repeating sound sequences or words sequences is hard, for example: “say p-t-k in sequence” or “say fish chips fish chips fish chips
    • When saying the same word again and again, different mistakes can be heard
    • Intonation difficulties: speech sounds monotonous
    • Vocabulary is very limited

    Some therapy approaches are more play based, for example the Core Word method: here we pick a few words at a time which are very significant to the child and therefore highly motivating to try and say. These could be characters of Pokemon or Minecraft for example, or simple words like “GO!”

    When you watch the video you will see that I use a lot of visual prompting, such as showing him where the tongue is moving to or from. I do this with my index finger and this approach is called Tactile Cueing or “Cued Articulation”. Part of the approach is to give a visual prompt and then reduce the prompt as the learner is more able to produce the correct sounds. Once he can produce the sound on its own, we quickly move to the sound within a word.

    I do mix and match my approaches and in fact here I am drilling but I also use the Core Word which for him (YELLOW) — it’s his favourite colour and I happen to have quite a few good games where a YELLOW something or other can be asked for….. WHO KNEW!? 🙂


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • · ·

    Why ‘Prosody’ Matters in Childhood Apraxia of Speech (CAS)

    Prosody refers to the ‘music’ of speech — the rhythm, pitch, stress, and volume that convey meaning and emotion beyond the literal words themselves. Think about a monotone statement like ‘Really?’ compared to one with a rising inflection, expressing genuine curiosity.

    When I work with children on producing speech sound sequences, we focus on mastering individual sounds and then putting them together into target words. A crucial element that can significantly impact a child’s speech production is ‘prosody’.

    In CAS, where the difficulty lies in planning and executing the motor movements for speech, prosody can be a powerful tool for producing clearer words and phrases.

    Here’s why working on prosody is an essential tool in CAS speech therapy:

    1.  It aids Motor Learning:

    Apraxia of Speech means that the planning and execution of speech movements are impaired. When we use exaggerated intonation or stress patterns while modelling words, we are providing additional prosodic variation and, therefore, additional auditory cues. These cues often help my student to carry out the correct motor movements for a word or syllable sequence.

    For instance, I might say ‘ball’ with a high-pitched emphasis on the ‘b’ sound. This auditory cue might be more effective in guiding the child’s tongue placement than simply repeating the word without variation.

    In this little video clip I get my student to say the word ‘snuggle’ (since we were working on that particular sound sequence: snuggle, snout, snore and sneeze) with a high voice and then a lower voice ‘like a bear’ — again it provides that extra auditory cue, but, in addition, the fun aspect also helps to take away the intense focus on a tricky movement pattern.

    By now the new pathways have been laid through repeated practice and now automaticity takes over and without too much effort my student can suddenly produce a motor pattern. It’s magical when it happens and gives me such a thrill.

    2. It makes speech more engaging and natural sounding:

    Children with CAS often sound robotic or flat due to challenges with prosodic elements. By incorporating variations in pitch, volume, and rhythm during therapy, we can help achieve a more natural flow of speech

    3. It makes it easier to express our emotions:

    Children with CAS often struggle to express themselves emotionally; partly through the difficulty of producing clear words — period, but also in addition due to the difficulties or absence of musicality and rhythm in their speech.

    Therefore, it is so important to incorporate activities focused on practising different emotions with varied intonation patterns. This can really empower our students to put emotions into their words.

    Good words to practise are fun words like ‘Wow!’ or ‘Yeiih’ or power words and phrases like ‘No!’ or ‘Gimme that’ etc.

    Making Therapy Fun and Engaging:

    Speech therapy for CAS doesn’t have to be all drills and exercises (though to be fair sometimes we can’t quite get round to making each and every word huge fun though we try…).

    I aim to make all my sessions fun and have intrinsic rewards built into the speech practice where possible.

    Home practice tips:

    Therapy shouldn’t exist in a bubble. Working on prosody during sessions is crucial, but it’s equally important to integrate these skills into everyday interactions. Parents and caregivers can model appropriate prosody during playtime, story time, or even simple conversations. This consistent reinforcement helps our children to generalise their newfound skills and use them naturally in their daily lives.

    • Sing songs and rhymes: Songs naturally incorporate variations in pitch and rhythm. Singing familiar songs and creating silly rhymes can be a delightful way to practise prosody.
    • Use puppets and toys: Assign different voices and personalities to puppets or toys. This encourages children to experiment with pitch and volume to differentiate characters.
    • Read aloud with enthusiasm: Model expressive reading, varying your voice for different characters and emphasising key words. This makes reading time engaging and helps children understand the power of prosody.

    Please feel free to contact me if your child has speech sound difficulties. It is my passion. I love supporting children with apraxia.

    Sonja McGeachie

    Early Intervention Speech and Language Therapist

    Feeding and Dysphagia (Swallowing) Specialist The London Speech and Feeding Practice

    The London Speech and Feeding Practice


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • ·

    Support your child’s communication using books: OI FROG

    Sonja's top recommendation: Oi Frog, written by Kes Gray and Jim Field. An exciting book for children to enhance their speech, language and communication.
    Oi Frog by Kes Gray and Jim Field

    Book corner with Oi Frog! by Kes Gray and Jim Field.

    Books are an engaging way to support your child’s communication development. Even if your little one dislikes reading in the traditional sense. They will become immersed in this adventure, without realising they are taking in language and developing vital communication skills. This is one of my favourite series for children.

    Increase fun and interaction

    These books are made for fun and excitement! It may seem silly putting on different voices for different characters, but this is one way in which you can engage your child. Why not try to use different intonation patterns (e.g., you may use a deep voice for the dog, and a higher pitch for the cat)? Make your story interactive: you could ‘rawww’ like a lion and see who can make the loudest noise. Make noises to encourage interaction (e.g., when scratching his chin, make a squeaky sound!). You could also relate the experience back to your child (e.g., ‘can you scratch your chin?’).

    Time to talk

    Talk about what you can see on the front cover (e.g., There’s a frog on a log, how funny!) You could also ask your child to choose the rhyming words on a page in the book. Can your child tell you what rhymes with certain words (e.g., can you guess what a parrot sits on?)? Make use of every page. You could comment on your favourite frog and see if your child can talk about their favourite. You can support them by giving them an example (“my favourite frog is the one swimming backwards because he looks funny”). Then you could use this scaffold to support their answer. Your favourite is [________________] because [_________________]

    If your child is reluctant to use language, the use of commenting can take the pressure of them (“look at all those frogs” or “he’s climbing up the stool”) is a powerful way in which you (as parents) can take the pressure off your child. A top tip I like to give is to make sure you pause regularly, which creates opportunities for your child to use language.

    This book uses a subject-verb-object sentence structure (e.g., ‘hares sit on chairs’) which allows your child to hear a good model of a sentence. You could also talk about things in the book that belong in a certain category (e.g., animals, food) or begin with a specific sound. See if your child will name any more.

    Reap the reward of repetitive language

    Oi Frog uses repetitive rhyming language and puts emphasis on these words. This is important because the more your child hears a word, the more likely they are to remember, understand and use it in the correct context.

    Emotions matter

    Talk about how the animals feel and why they may feel this emotion (e.g., the cat’s feeling annoyed because…, Lions sit on irons, how does the lion feel?). Reasons can be difficult for children with communication difficulties. Support them by giving an example or by giving them an option (e.g., “does the lion feel happy or sad? I think the lion feels sad because he’s burnt his bottom on the iron! It’s too hot!”)

    A collection of books
    OI Books

    Why not read similar stories? I highly recommend OI CAT, OI DOG and OI DUCK-BILLED PLATYPUS.

    Need support for your child’s communication? Contact me here.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    2

