The importance of child-led therapy

|

Child-led therapy is essentially what it says, therapy sessions that are directed by your child. You may think how can my child’s Speech and Language Therapist focus on goals if sessions are led by my child.

Let us explain…

Your child will be more receptive and motivated to take part in therapy if they have some form of input. E.g., they can choose what toys they want to play with, or how they want to play with the resources available. If sessions are child-centred then they are much more likely to engage and reach their goals, making intervention valuable. They will also be able to regulate their emotions, and use movement to support their need for regulation. E.g., some children like to jump whilst others like to run. As Speech and Language Therapists we need to use what is meaningful to your child to get the most out of intervention. By focusing on child-led therapy, we can build trust, which will allow us, in time, to use new techniques and activities that your child may enjoy. We want children to be themselves, to show their true personality. Therapy is about enhancing their skills in their own individualised way and child-led therapy allows for this.

This way of working may seem daunting to some, but it doesn’t have to feel this way. Parents often feel if they are prepared then activities may go smoother. It might be the case, but perhaps it doesn’t give your child the opportunity for spontaneity. We’d like to suggest something that may lead to some surprises. Put out an activity that is your child’s favourite and then a completely new activity. Remember these activities don’t have to be complicated. Often, the simpler the better!

So, no need to plan, just place two activities out and see what happens! Look out for anything which surprises you, which activity did they prefer? Do they have any sensory preferences? The freedom of choice is a wonderful thing to explore. So, just go with the flow!

The kind of activities that are useful for child-led play can include:

  • Hide and seek
  • Cooking or baking
  • An Exercise ball
  • Small world play
  • Pretend play
  • Musical instruments (you could even have a go at making your own)

Child-led therapy is a very useful resource. We have it at our fingertips. We don’t need special resources. You just need yourselves and your child! Sometimes, child-led therapy can be tricky to put in place. It sounds easy but is much harder in reality. So, make sure you give it time and reflect on your experiences. Ask yourselves ‘what went well’, and ‘what could be improved’. E.g., perhaps you gave your child time to lead to begin with, but you didn’t give them enough time to think about their options during the activity.

How can parents become more child-led in the home environment?

  • Pause and use silence. This gives your child the opportunity to lead.
  • It’s perfectly natural to want to talk. Afterall, this is how adults maintain conversations. If you find yourself talking too much, count to ten! This will allow your child time to respond or initiate in the conversation or interaction.
  • Move down to your child’s level. It’s much easier to see what’s going on if you’re at the same height.
  • Videoing you and your child can really help you to see where your strengths lie. You’ll also be able to make minor tweaks to improve your communication during child-led play.

Contact Sonja for more advice on speech, language and communication during child-led play.


Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

0

Similar Posts

  • · ·

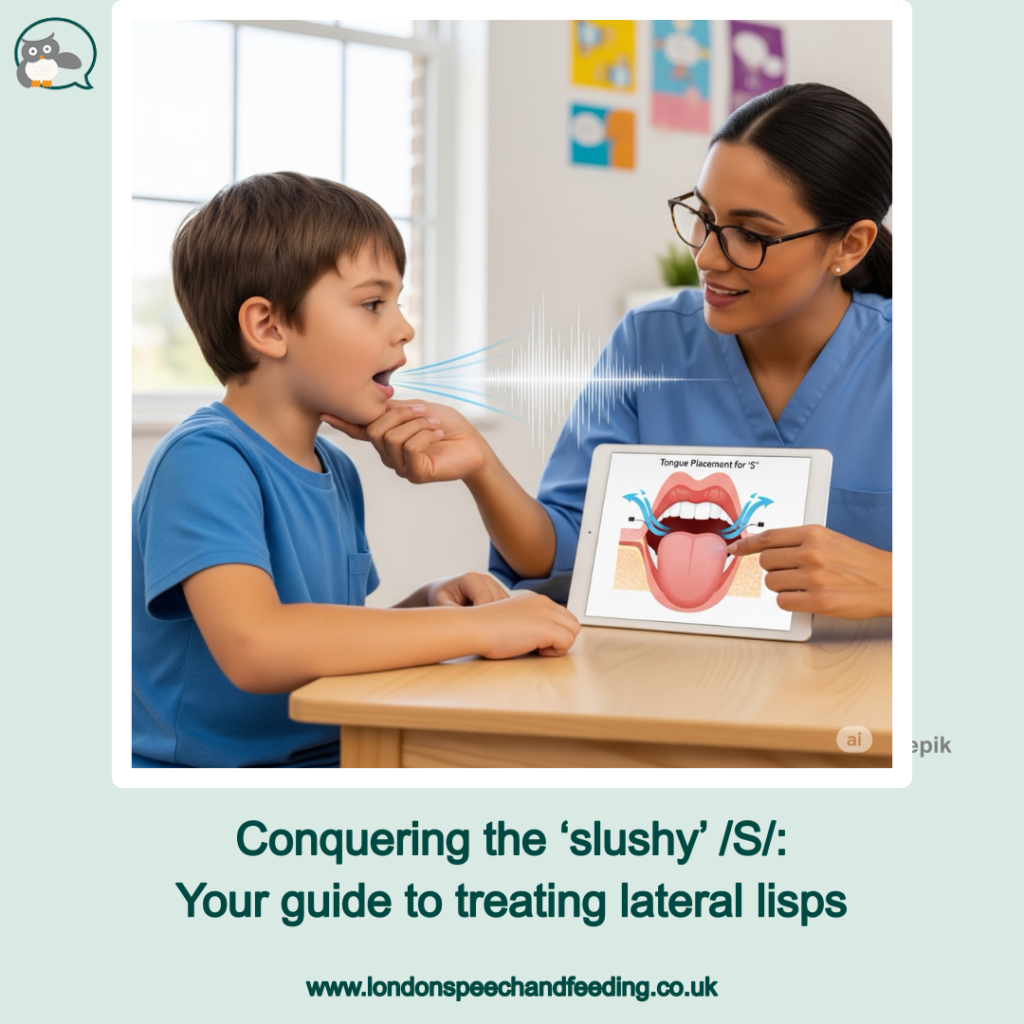
    Conquering the ‘slushy’ /S/: Your guide to treating lateral lisps

    Conquering the ‘slushy’ /S/: Your guide to treating lateral lisps

    As a speech therapist, few things are as rewarding as helping a child find their clear, confident voice. Among the various speech sound disorders, the ‘lateral lisp’ – often described as a ‘slushy’ or ‘wet’ /S/ sound – presents a unique challenge. While it can be tricky to treat, I’m thrilled to share that I’ve had significant success in helping children overcome this particular hurdle.

    What is a lateral lisp?

    Most people are familiar with a frontal lisp, where the tongue protrudes between the front teeth, resulting in a /TH/ sound for an /S/ (e.g., ‘thun’ for ‘sun’). A lateral lisp, however, is different. Instead of the air escaping over the front of the tongue, it escapes over the sides, often giving the /S/ and /Z/ sounds a distinct, muffled, or ‘slushy’ quality. This happens because the tongue is not forming the correct central groove, allowing air to spill out laterally.

    The science behind a perfect /S/ vs. a slushy one

    To understand how to fix a lateral lisp, it’s helpful to understand how a ‘perfect’ /S/ sound is made. Imagine a narrow, focused stream of air. For a clear /S/ sound, your tongue forms a shallow groove down its centre, directing a precise, thin stream of air right down the middle, over the tip of your tongue, and out through a tiny opening between your tongue and the roof of your mouth, just behind your front teeth. This focused airflow creates that crisp, sharp /SSSS/ sound we recognise.

    Now, picture what happens with a lateral lisp. Instead of that neat, central channel, the tongue is often flatter or positioned in a way that allows the air to escape over one or both sides. Think of it like a river overflowing its banks – the air, instead of flowing in a controlled stream, spills out sideways, creating that characteristic ‘slushy’ sound. This lateral airflow is what we need to retrain.

    Why is it tricky to treat?

    Treating a lateral lisp can be challenging for a few reasons:

    • Habitual muscle memory: The way the tongue moves and positions itself for a lateral lisp is deeply ingrained. It’s a motor habit that needs to be unlearned and replaced with a new, more precise movement.
    • Subtle differences: The difference between a lateral lisp and a correct /S/ sound can be quite subtle to perceive, both for the child and sometimes even for parents. This makes it harder for the child to self-monitor and correct.
    • Oral motor control: It requires fine motor control of the tongue muscles to create and maintain that central groove for airflow.

    My success with children aged six years and over

    I’ve found great success in treating lateral lisps, particularly with children aged six years and older. Why this age group? By this age, children typically have:

    • Increased awareness: They are more aware of their speech and often more motivated to make changes. They can better perceive the difference between their ‘slushy’ /S/ and a clear one.
    • Improved cognitive skills: They can understand and follow more complex instructions and strategies.
    • Better self-monitoring: Their ability to listen to themselves and correct their own speech improves significantly.
    • Enhanced oral motor control: Their fine motor skills, including those of the tongue, are more developed, allowing for greater precision.

    My approach focuses on a combination of auditory discrimination, tactile cues, and targeted myofunctional exercises to help children ‘feel’ the correct airflow and tongue placement. We use a variety of engaging activities to make the process fun and effective.

    It is crucial to understand tongue functioning and focusing on correcting improper oral resting posture and muscle function, which are often significant contributors to a lateral lisp. For example, if the tongue rests low and wide in the mouth consistently, or if there’s a tongue thrust during swallowing, these habits can prevent the tongue from achieving the precise, midline placement necessary for a clear /S/ or /Z/ sound. Through targeted exercises I aim to re-educate the oral and facial muscles, promoting correct tongue posture at rest, during swallowing, and, ultimately, during speech production. By strengthening the muscles responsible for tongue lifting and encouraging a more appropriate swallowing pattern we can establish the correct oral motor skills needed to overcome a lateral lisp and achieve clearer articulation.

    The recipe for success: Little and often

    The single most crucial ingredient for success in treating a lateral lisp is daily home practice of all the strategies given. This isn’t about long, arduous sessions; it’s about consistency. Think of it like building a muscle: short, frequent workouts yield better results than sporadic, intense ones.

    My recommended formula is ‘little and often’. This means:

    • Short, focused sessions: Aim for 5-10 minutes of practice, 2-3 times a day. This prevents fatigue and keeps the child engaged.
    • Integrate into daily routines: Practise while waiting for dinner, during a car ride, or before bedtime. Make it a natural part of their day.
    • Positive reinforcement: Celebrate every small success! Encouragement goes a long way in building confidence and motivation.
    • Parental involvement: Parents play a vital role in providing consistent cues and encouragement at home. I equip families with clear, easy-to-follow strategies.

    Overcoming a lateral lisp requires dedication, but with the right guidance and consistent practice, a clear, confident /S/ sound is achievable. If your child is struggling with a ‘slushy’ /S/, please don’t hesitate to reach out. Together, we can achieve success!

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • Speech sound disorders

    Kids Speech Therapist London
    Speech Sound Disorders

    Treatment Approaches – A Typical Session

    There are various great ways to treat speech sound disorders and I use all the approaches available selectively; I decide what works with each individual child and I also vary the approach depending on the child’s frame of mind at any given time during my session.

    Some of the approaches are more “drill-based” and require a child to be able to pay attention and really participate actively in the therapy, and this is what I am showing you today with this video clip.

    My little student here has been working with me for some time and from only saying a handful of words which were not very easy to understand he has come a long way. He does have some features of Verbal Dyspraxia which I shall briefly outline here:

    • Making sounds in general is a struggle, especially when asked to copy certain sounds, example: ‘can you say: a ee ou oo?”
    • Repeating sound sequences or words sequences is hard, for example: “say p-t-k in sequence” or “say fish chips fish chips fish chips
    • When saying the same word again and again, different mistakes can be heard
    • Intonation difficulties: speech sounds monotonous
    • Vocabulary is very limited

    Some therapy approaches are more play based, for example the Core Word method: here we pick a few words at a time which are very significant to the child and therefore highly motivating to try and say. These could be characters of Pokemon or Minecraft for example, or simple words like “GO!”

    When you watch the video you will see that I use a lot of visual prompting, such as showing him where the tongue is moving to or from. I do this with my index finger and this approach is called Tactile Cueing or “Cued Articulation”. Part of the approach is to give a visual prompt and then reduce the prompt as the learner is more able to produce the correct sounds. Once he can produce the sound on its own, we quickly move to the sound within a word.

    I do mix and match my approaches and in fact here I am drilling but I also use the Core Word which for him (YELLOW) — it’s his favourite colour and I happen to have quite a few good games where a YELLOW something or other can be asked for….. WHO KNEW!? 🙂


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • · ·

    Are the Gestalts I model easy to mix and match later on?

    Image by bearfotos on Freepik

    Here are some examples of great phrases and Gestalts that we could use:

    • Let’s get a banana / Let’s go out / Let’s play lego / Let’s go see daddy
    • That’s nice! / That’s really good! / That’s a green one / That’s a submarine
    • Need more help / Need a wee wee / Need that / Need to run
    • How about a biscuit / How about a cuddle / How about watching tv
    • We love bananas / We love a monkey / We love a cuddle

    Why or how could these examples be mixed and matched?

    You can see I have given several examples for each, that is how later a child can take one chunk (let’s) and add another (go out) or (need) + (go out).

    What about our own grammar? Should we be using grammatical phrases?

    In general for NLA 1 (Natural Language Acquisition stage 1) we want to use short phrases and keep them quite generic, something like:

    ‘Let’s go’ or ‘let’s play’ and pick 2-3 phrases per communicative function (see next point below).

    And if we are going to say longer sentences, for example: ‘let’s go and feed the ducks now’, then we should do so with good grammar and really varied intonation. It sometimes helps me to make up a little song/jingle on the spot that has a lot of intonation, more than I would perhaps use just by speaking.

    How many varied communicative functions do we cover with our modelling?

    We want to model a variety of Gestalts other than just requesting for example. In general, we are looking at our child having one or two Gestalts in the following areas before they are ready to move on into stage 2.

    These are the most common ones I see in my practice:

    • Requesting ‘want a banana/biscuit’ ‘Wanna play ball’
    • Transitioning: ‘what now?’ ‘what next?’
    • Ask for help: ‘need help’ ‘help me’ ‘mummy help’
    • Commenting: ‘it’s big’ ‘it’s red’ ‘it’s fast’ ‘too loud’
    • Speak up for self: ‘not that one’ ‘go now’ ‘stop it’

    Is the Gestalt I am modelling meaningful to my child?

    We don’t use all available Gestalts for every child. It has to be meaningful to the individual and has to match their interests. If our child is a big fan of feeding the ducks in the park then we can think about Gestalts like:

    • I see ducks!
    • They’re over there
    • Let’s feed them?
    • Let’s get some seeds
    • They’re coming!
    • They want food / They wanna eat!
    • That’s a big one
    • It’s so hungry
    • It loves the seeds!
    • No more! All done! Finished! Let’s go home

    What is my child actually trying to tell me?

    We have to be become word/phrase detectives! Is the phrase/script/Gestalt they are using right now actually meaning what they said or does it mean something else, and if so, what?

    Here is an example from my own personal experience in my practice:

    The little boy I was working/playing with was building a tall tower with blocks. When it finally fell with a great big bang he said in a sing-song voice ‘ring-a-ring-a roses’ … then he began to collect the blocks again to make a fresh tower. I sat there and thought: why ‘ring-a-ring-a roses’? What does that mean in this context? I then sang the song (silently) to myself with my detective hat on and realised as I came to the end that it finishes with ‘we all fall down’! it was a real AHA!!! moment for me as I saw right there what the meaning of his Gestalt was. He sang the first line of the song to say ‘all fall down!’

    So realising this I waited for the next tower to fall, and there it was again, he sang the first line of the song. I replied thus, copying him at first:

    ‘RING-A-RING-A ROSES – WE ALL FALL DOWN!…

    FALL DOWN

    WE LOVE IT FALLING DOWN.’

    The process to find what we should say is not always straight forward or easy at all, and often we don’t quite know in the moment what our child is trying to say. But we can try and get to know their interests and then gradually we do know more and more what the meaning behind the Gestalt is or could be.

    What pronouns should we use?

    This can be a tricky one.

    We don’t want to use language that uses the pronouns ‘you’ or ‘you’re’. The reason is that our child will likely copy us exactly as we have said it. Therefore, using pronouns ‘you’ and ‘you’re’ will then sound wrong.

    Always try to model language that is from the child’s perspective or in other words how they would say it if they could.

    Alternatively, you can model using WE or US. For example, if the child is tired, rather than saying ‘you are so tired’ model language from his or her point of view: ‘I’m tired’ or ‘let’s go have a lie down’.

    There is so much more to talk about. Stay tuned for a blog on NLA stage 2 coming soon.

    If you need help with your child, please do not hesitate to contact me.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    0
  • · · ·

    Seeing sounds: How visual gestures boost speech sound learning

    Learning to produce new speech sounds can be a complex process for young children, especially those facing challenges with speech sound disorders or motor planning difficulties. It’s not just about knowing what a sound ‘should’ sound like; it’s about figuring out where to put your tongue, how to shape your lips, and how much air to push out. This is where the power of visual gestures comes in – literally helping children see how to make sounds.

    As speech and language therapists, we frequently use visual cues and hand gestures to teach articulation. These techniques are incredibly effective, particularly when a child is struggling with the motor planning aspect of speech production.

    In the video clip above you see me teaching

    • the /SH/ sound: the hand makes a C-shape and moves forward showing both how the lips are positioned and the air flowing forward
    • the /S/ sound: the index finger shows a snake like movement going forward- also showing the air flow again
    • the /W/ sound: my right hand moves forward and fingers splay out showing that the lips open up at the end of the sound
    • the /K/ sound: my finger points to the back of my throat where the tongue needs to raise.

    An overview of motor planning for speech – what do we mean by that?

    Think about learning to ride a bike or play a musical instrument. You don’t just know how to do it instantly. You have to plan the movements, practise them, and make adjustments. Speaking is similar! Our brains must:

    1. Plan the sequence of movements needed for each sound and word (e.g., /B/ requires lips together, then release, while /T/ requires the tongue tip behind the top teeth, then release).
    2. Execute those plans rapidly and precisely.

    For some children, especially those with conditions like Childhood Apraxia of Speech (CAS) or other severe articulation disorders, this motor planning process is disrupted. They know what they want to say, but their brain struggles to send the correct, consistent messages to their articulators (lips, tongue, jaw, velum). This can make speech sound learning incredibly frustrating.

    Why use visual gestures?

    Visual gestures provide an additional, powerful sensory input that can help bridge the gap between knowing a sound and producing it. Here’s how and why they are so beneficial:

    1.      Providing a visual map:

    • How it helps: Many speech sounds are ‘hidden’ inside the mouth. It’s hard for a child to see where their tongue needs to go for a /K/ sound (back of the tongue to the roof of the mouth) or a /T/ sound (tongue tip behind teeth). A simple hand gesture can visually represent this mouth movement. For example, a hand gesture for /K/ might involve sweeping the hand back towards the throat, while for /T/, it might be a tap on the chin.
    • Why it works: Children are highly visual learners. Seeing a physical representation of an abstract mouth movement gives them a concrete ‘map’ to follow, making the process less mysterious and more manageable.

    2.      Enhancing motor planning and memory:

    • How it helps: When a child simultaneously moves their hand (the visual gesture) and attempts to make the sound, they are engaging multiple sensory systems (visual, tactile, proprioceptive – body awareness). This multi-sensory input strengthens the neural pathways associated with that speech sound.
    • Why it works: This multi-modal learning helps to solidify the motor plan for the sound in the brain. It’s like having more ‘hooks’ to hang the information on, making the sound easier to recall and produce consistently. The gesture becomes a built-in reminder.

    3.      Reducing cognitive load:

    • How it helps: Instead of just hearing the sound and trying to figure out the complex motor sequence, the child has a visual cue to guide them. This reduces the mental effort required to decode the sound production.
    • Why it works: When cognitive load is lower, the child can focus more effectively on the specific motor execution of the sound, leading to faster progress and less frustration.

    4.      Increasing engagement and success:

    • How it helps: Gestures can make therapy more interactive and fun! When a child successfully produces a sound with the help of a gesture, it’s a tangible victory.
    • Why it works: Success is a powerful motivator. When children experience success, they are more likely to stay engaged, participate actively, and feel more confident in their ability to learn new sounds.

    5.      Supporting self-correction:

    • How it helps: Once a child learns the gesture associated with a sound, he or she can use it as a self-monitoring tool. If he or she makes an error, he or she can use the gesture to remind himself or herself of the correct mouth position or movement.
    • Why it works: This promotes independent learning and reduces reliance on constant adult prompting.

    Conclusion

    The journey of speech development can be challenging, but visual gestures offer a powerful and effective tool for teaching new sounds, especially when motor planning is a factor. By providing a clear visual map, strengthening motor memory, reducing cognitive load, and fostering engagement, these gestures pave the way for clearer communication and greater confidence. If your child is struggling with speech sounds, consider talking to a Speech and Language Therapist to get guidance on how visual gestures might be incorporated into the therapy plan. Because sometimes, seeing truly is believing (and speaking!).

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • ·

    A bite-sized guide to Speech and Language Therapy: feeding and swallowing

    What is a Speech and Language – Feeding Therapist?

    You’ve probably heard of speech therapists helping people who stutter or struggle to pronounce words. But did you know that they also work with children and adults who have problems with eating and swallowing? This specialised area is called Speech and Language Therapy: Feeding and Swallowing, or Dysphagia Therapy.

    Why does a Speech Therapist help with eating and swallowing?

    The mouth, tongue, and throat are all involved in both speech and swallowing. When there’s a problem with any of these parts, it can affect both your ability to talk and to eat. For example:

    • Weak tongue muscles: Can make it hard to chew food and to form sounds.
    • Difficulty coordinating swallowing: Can lead to choking or aspiration (when food or liquid goes into the lungs).
    • Sensory issues: Can make certain textures or tastes feel unpleasant or overwhelming.
    • Communication: If we are not able to express ourselves we are likely to have difficulties during daily mealtimes: how do we ask for ‘more’ of something, how do we say we have had enough or we don’t like a particular food?

    How does a Speech and Language Therapist help?

    Our work involves a combination of assessment and therapy. We carefully observe how your child feeds, eats and swallows, and we look into your child’s mouth to help us see what the cause of the difficulties are: could be a very highly-arched palate, it could be a very flaccid/low tone tongue, it could be poor dentition. Then, we create a personalised treatment plan to address your specific needs.

    Here are some of the things we might do:

    • Teach swallowing techniques: We can help your child learn strategies to improve or facilitate a safe swallow.
    • Recommend dietary modifications: We may suggest changes to your child’s diet to make it easier to eat and swallow.
    • Provide sensory therapy: If your child has sensory needs we can help your child become more comfortable with different textures, tastes, and smells.
    • Work on oral motor skills: We can help to encourage more effective chewing, or drinking skills, or we can help your child to close his/her mouth more during chewing or drinking from a straw.
    • Collaborate with other professionals: We often work closely with doctors, nurses, occupational therapists, and dietitians to provide comprehensive care.

    What kinds of problems do Speech and Language Therapists help with?

    We see a wide range of feeding and swallowing difficulties, including:

    • Delayed feeding: Children who are slow to develop feeding skills or who have difficulty transitioning to solid foods.
    • Tongue-ties: Babies can have significant difficulties with feeding when the tongue is very tightly tethered to the floor of the mouth.
    • Refusal to eat: Children who refuse to eat certain foods or textures.
    • Aspiration: When food or liquid goes into the lungs, which can lead to pneumonia and other serious complications.
    • Chewing difficulties: Problems with chewing food, such as difficulty breaking down food or keeping food in the mouth.
    • Swallowing difficulties: Problems with swallowing, such as feeling like food is stuck or choking.
    • Neurological conditions: Conditions like cerebral palsy, down syndrome or other genetic syndromes can affect feeding and swallowing.
    • Developmental delays: Children with developmental delays may have difficulties with feeding and swallowing.

    Is there hope?

    If your child is struggling with feeding or swallowing, know that there is help available. Speech and Language Therapy can make a significant difference in your and your child’s quality of life. We’re here to support you every step of the way.

    Remember, you don’t have to suffer in silence. If you’re concerned about your child feeding or swallowing, please reach out. You can find a Speech and Language Therapist with a Feeding/dysphagia qualification near you via www.asltip.co.uk or contact me.

    Sonja McGeachie

    Early Intervention Speech and Language Therapist

    Feeding and Dysphagia (Swallowing) Specialist The London Speech and Feeding Practice

    The London Speech and Feeding Practice


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • Help! My child has a lisp. What can we do about it?

    What is a LISP?

    There are different types of LISPS. Let me explain:

    A lisp is the difficulty making a clear ‘S’ and ‘Z’. Other sounds can also be affected by the tongue protruding too far forward and touching the upper teeth or the upper lip even. ‘T’ and ‘D’ can be produced with ‘too much tongue at the front’ and this can also have an impact on ‘CH’ and often also ‘SH’.

    1. Interdental lisp

    Protruding the tongue between the front teeth while attempting ‘S’ or ‘Z’ is referred to as interdental lisp; it can make the speech sound ‘muffled’ or ‘hissy’. Often, we associate a lisp with the person sounding a bit immature. The good news is that this type of lisp is the easiest to correct and, in my practice. I have a 100% success rate with this type of lisp.

    1. Lateral lisp

    In a lateral lisp the person produces the ‘S’ and ‘Z’ sounds with the air escaping over the sides of the tongue. This renders the ‘S’ as sounding ‘slushy’ or ‘wet’. This type of lisp is a bit harder to correct than the interdental lisp. In my experience this can be fixed but it might need a bit longer, more intensive therapy than the interdental lisp.

    1. Palatal lisp

    With a palatal lisp the ‘S’ sound is attempted with the tongue touching the palate, much further back than it should be. The ‘S’ sounds ‘windy’ and ‘hissy’. This is a quite rare lisp production but it is also not difficult to correct.

    These types of speech difficulties come under the category of ‘speech delay of unknown origin’ and may persist into adolescence and adulthood as ‘residual errors‘.

    Some thoughts on Treatment in general:

    Lisps can be treated successfully by a Speech and Language Therapist. However, for the treatment to work well, a student needs to be able to cooperate and want to improve his or her speech. Lisp remediation entails a fair amount of repetitive work and very young children or unmotivated older children don’t make the best candidates for treatment for this reason. Often students present with other speech, language or social communication difficulties and here the lisp might not be the priority for treating. For example, it might be that due to a student’s Attention Deficit Disorder they are simply not able to focus on speech practice in their daily life.

    When should treatment of lisp begin?

    Waiting well past 4½ years is not advisable as the longer we wait and do nothing the stronger engrained the erroneous tongue/speech habit will become. The ‘right’ age for therapy for one child may be different from the ‘right’ age for another child even within the same family. So do make an appointment with a speech and language therapist to assess and see whether your child might be ready to start therapy.

    Do lots of children lisp—is it normal?

    Until the age of about 4–4.5 years old it can be a perfectly normal developmental phase for some children to have the interdental lisp. But when we see and hear a lateral or palatal lisp we ought to act and see a speech and language therapist for sure.

    After the age of 4.5 or 5 years old most speech therapists would agree on at least having a look to see if treatment could be started. The longer we wait the harder it is to retrain the brain pathways to adopt new speech habits.

    What happens during the first Speech and Language Consultation?

    The first consultation takes about an hour and involves screening relevant areas of communicative function. We take a detailed history, examine the anatomy of the child’s mouth and tongue movements. We check for tongue tie, teeth formation, palate structure and function, as well as swallowing patterns.

    Then we begin straight away to try and see if any of the alveolar sounds (T/D/L/N) can be produced correctly with the right tongue placement as that would be the starting point from where to shape a good, clear ‘S’ sound.

    The first consultation usually ends with home practice being given, explained to parents and another appointment being made for follow up.

    Therapy – what does a session look like?

    Each therapy session consists of:

    1. Listening to sounds, discriminating sounds, identifying sounds, listening to rhyming sounds, sound awareness. We call this Auditory discrimination of single sounds: can the student hear the difference between two words that are the same apart from the first sound: ‘sing’ and ‘thing’ or ‘sigh’ and ‘thigh’?
    2. Sound production: using a variety of different prompts and cues we will teach how to physically make the new sound. Often, we work on making a NEW sound, instead of correcting the OLD one. We work on imitation of single sounds then gradually we try and make new sounds in short words, then longer words and then phrases and sentences.
    3. Games! We play games and try and have fun in between listening and producing our new sounds to help students stay motivated and even enjoy the therapy session and process.

    How long does it take to ‘fix up’ a lisp?

    It tends to take about one term with weekly sessions to help a student make good ‘S’ sounds in phrases and sentences. If the student can do the home practice every day in between the weekly sessions, then in most cases I am able to pronounce the lisp as ‘fixed’ after about one term.

    After that the student needs to practise, practise, practise, at home and in daily life to keep reminding themselves of their new skills and their new sound production.

    It is a matter of reminding and wanting to get it right. Occasionally a student returns to me for another term of simply practising their skills together with me as they are finding it hard for any number of reasons to practise at home. But generally, 8/10 students will be fine after some 12–13 sessions and their speech will be perceived as perfectly typical by family and friends.

    If your child has a lisp or any other speech error, please do not hesitate to contact me.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    0