Paediatric Speech Therapy

  • ·

    Does my child need a myofunctional therapist? Lisps, tongue posture and oral function explained

    Have you ever been told that if your child’s lisp or /R/ sound isn’t improving after months of speech therapy, you should see a myofunctional therapist?

    The short answer is: possibly, but not automatically. Whether it will help depends on what is behind your child’s difficulty, and finding that out is exactly what a thorough assessment is for.

    I’m a Speech and Language Therapist with nearly 30 years’ experience in speech sound disorders, feeding and swallowing, and I have additional training in myofunctional therapy. Looking at how the mouth works has been an intrinsic part of my assessments for many years, so I’d like to explain what that involves and when it matters.

    What is myofunctional therapy?

    Myofunctional therapy (often called orofacial myofunctional therapy, or OMT) is about how the muscles of the mouth and face work. It overlaps with what speech and feeding therapists call oro-motor function, although OMT looks more specifically at things like resting posture, breathing and swallowing patterns. Depending on the therapist’s training and your child’s needs, it may include:

    • tongue movement, resting posture and positioning
    • lip closure and resting posture
    • jaw movement and coordination
    • oral habits, such as thumb sucking or dummy use
    • swallowing patterns
    • how oral function, feeding and speech affect one another.

    Some children have difficulties across several of these areas. Others have one specific speech sound difficulty and no wider problem with how their mouth works.

    Signs it may be worth having your child’s oral function checked

    You might want an assessment if your child:

    • has a lisp or a tricky /R/ that hasn’t changed with therapy
    • often has their mouth hanging open at rest
    • pushes their tongue forward against or between their teeth when speaking or swallowing (sometimes called tongue thrust)
    • is still dribbling or drooling after 18 months
    • finds chewing difficult, or struggles to move their tongue up, out or from side to side
    • breathes mostly through their mouth.

    If you are worried about tongue-tie, I can assess how your child’s tongue moves for speech and feeding. If a medical or dental opinion is needed, I will explain why, advise you on who to see and work alongside them, for example an ENT consultant or paediatric dentist.

    What does a comprehensive assessment look at?

    When a child has a speech sound difficulty, I look at their speech alongside how their mouth is built and how it works. Depending on the concern, that may include:

    • jaw: how steady it is, and how well it moves and coordinates with the lips and tongue
    • teeth and mouth structure: the position of the teeth, the bite, the palate and anything structural that may be relevant
    • lips: closure, movement and resting posture
    • tongue: how well it moves in different directions, where it rests and whether it pushes forward
    • swallowing: relevant aspects of how your child swallows and where the tongue sits
    • palate and voice: anything that may need further investigation, such as concerns about how the palate is working or an unusually nasal sound
    • habits and breathing: things like thumb sucking or mouth breathing, and any signs that a medical or dental check may be needed.

    Not every child needs every part of this. The questions we are trying to answer guide what I look at and what happens next.

    For example, a child with a lisp may find it hard to coordinate the tongue placement needed for an /S/ sound. They may rest their tongue low in the mouth, or they may have spent years making the /S/ sound with the tongue between the teeth. By looking at how the mouth moves, along with habits and history such as thumb sucking, I can understand what may be contributing and plan therapy accordingly.

    The findings help decide whether your child needs direct speech therapy, further assessment, a different approach, or input from another professional such as an ENT consultant, dentist or orthodontist. Assessment isn’t simply about spotting something that looks unusual. It is about understanding what it means for your child and deciding what, if anything, needs to be done. This kind of clinical reasoning is a natural, daily part of my work as a Speech and Language Therapist.

    What if my child isn’t making progress in speech therapy?

    If your child has been attending therapy for weeks or months without meaningful progress, it is reasonable to ask for a review. In my practice I monitor progress from one session to the next, and if things aren’t moving, I would rather review the plan than simply carry on with the same approach.

    Sometimes a child needs more time. Sometimes the approach needs to change. Sometimes we need more information or another professional’s input. Sometimes therapy needs to pause while an underlying issue is looked into.

    Whichever it is, you can expect a clear explanation of what we are working towards and how progress will be reviewed. A lack of progress should always prompt a review of the plan.

    Does myofunctional therapy help with speech difficulties?

    Sometimes. Some children have speech sound difficulties alongside differences in how their mouth works, which is why I assess both and consider whether they are related. A different tongue posture, an open-mouth resting posture or an unusual swallowing pattern is always worth noting, but it is not automatically the cause of a lisp or another speech sound disorder.

    For speech sound disorders, treatment should be chosen to match the nature of the speech difficulty and be supported by evidence. The routine use of non-speech oral-motor exercises, meaning exercises that don’t involve practising speech sounds, to improve speech is not supported by the available evidence (the Cochrane review of non-speech oral-motor treatment – Lee & Gibbon, 2015).

    That doesn’t mean work on oral function is never appropriate. The important question is what we are trying to achieve. If the aim is clearer speech, therapy needs to work on the speech itself, with plenty of practice of the relevant sounds, syllables and words. If your child also has a separate difficulty with feeding, swallowing or another aspect of oral function, such as resting posture, that may need its own assessment and targeted therapy. This is why I combine evidence-based speech practice with myofunctional assessment and therapy where a child’s oral function needs it, and I will always explain the aim and the reasoning behind what I recommend.

    Choosing the right therapist for your child

    Whoever you choose, I would encourage you to ask who will be treating your child, what their training covers and whether they are well placed to meet your child’s particular needs. Good clinical practice includes recognising the limits of your own expertise and referring on or working with others when appropriate. No practitioner should feel they have to manage every part of a child’s difficulties alone.

    When the main concern is your child’s speech sounds, speech clarity or expressive language, I would recommend starting with an experienced Speech and Language Therapist whose expertise matches your child’s needs. If that therapist also has additional training in myofunctional therapy, so much the better. You can check that any Speech and Language Therapist is registered using the HCPC online register, and it is always fine to ask about a practitioner’s original qualification, clinical experience and the scope of their training.

    So that you know who would be working with your child, here is a little about my own training: I am an HCPC-registered Speech and Language Therapist (BSc Clinical Communication Sciences, Royal Central School of Speech and Drama, 1996) with nearly 30 years’ experience, a postgraduate diploma in dysphagia (2000) and certification in the SOS Approach to Feeding (2018) and Orofacial Myofunctional Disorders training in 2026. I also completed IBCLC lactation consultant certification in 2019 (since lapsed, 2024) and worked as a neonatal Speech and Language Therapist and Lactation Consultant at Barnet Hospital in 2019–2020.

    Next steps

    If your child has a lisp, a tricky /R/, an open-mouth resting posture, a tongue thrust, dribbling or difficulty chewing, I would be happy to look at the whole picture. I assess speech and oral function together, and if your child needs a dentist, orthodontist or ENT consultant, I will tell you.

    You can find out more on my Speech and Feeding Difficulties page, or get in touch to arrange an assessment. If you’re not sure whether your child needs one, contact me and we can talk it through.

    Sonja McGeachie

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    Reference

    Lee AS-Y, Gibbon FE. Non-speech oral motor treatment for children with developmental speech sound disorders. Cochrane Database of Systematic Reviews 2015, Issue 3. Art. No.: CD009383. DOI: 10.1002/14651858.CD009383.pub2.

    3
  • Could mouth breathing be affecting your child’s speech, sleep and development?

    Could mouth breathing be affecting your child's speech, sleep and development?

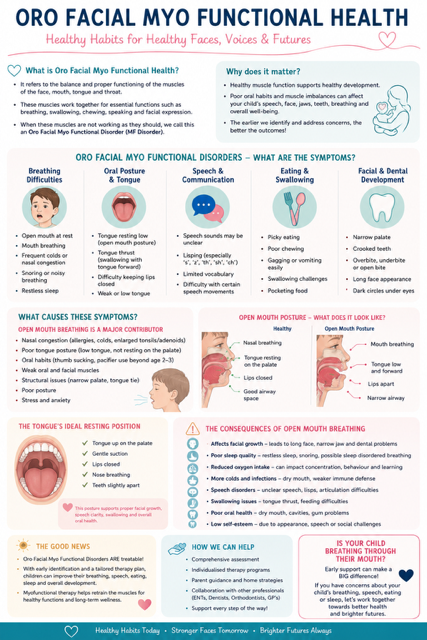
    Understanding Orofacial Myofunctional Disorders (OMDs)

    Many parents contact me at London Speech and Feeding because they are worried about their child’s speech. Perhaps their child is difficult to understand, has a persistent lisp, struggles with feeding, snores at night, or always seems to have their mouth open.

    What many families don’t realise is that these concerns may all be connected.

    Increasingly, research and clinical experience are highlighting the important role of Orofacial Myofunctional Health, the way the muscles of the face, mouth, tongue and airway work together to support breathing, eating, sleeping and communication.

    When these muscles are not functioning optimally, children may develop what are known as Orofacial Myofunctional Disorders (OMDs).

    What Is Orofacial Myofunctional Health?

    Orofacial Myofunctional Health refers to the healthy function and coordination of the:

    • lips
    • tongue
    • jaw
    • cheeks
    • facial muscles
    • airway.

    These structures play a vital role in:

    • breathing
    • swallowing
    • chewing
    • speaking
    • facial growth
    • dental development
    • sleep quality.

    When everything is working well, the lips remain gently closed at rest, breathing occurs through the nose, and the tongue rests against the roof of the mouth.

    This seemingly simple posture has a profound influence on how a child’s face, teeth and airway develop.

    What is an Orofacial Myofunctional Disorder?

    An Orofacial Myofunctional Disorder occurs when there is an abnormal pattern of muscle function involving the face, mouth, tongue or airway.

    Children with OMDs may experience difficulties with:

    • speech
    • feeding
    • swallowing
    • sleep
    • breathing
    • dental development
    • facial growth.

    In many cases, these difficulties are linked to chronic mouth breathing.

    Signs your child may have an Orofacial Myofunctional Disorder

    Breathing and sleep signs

    • mouth open at rest
    • mouth breathing during the day
    • snoring
    • noisy breathing
    • restless sleep
    • frequent waking
    • dark circles under the eyes
    • chronic congestion
    • fatigue despite a full night’s sleep.

    Speech signs

    • lisping
    • unclear speech
    • distorted speech sounds
    • difficulty producing certain sounds
    • persistent articulation difficulties
    • reduced speech intelligibility.

    Feeding and swallowing signs

    • picky eating
    • messy eating
    • food remaining in the cheeks
    • gagging easily
    • difficulty chewing
    • long mealtimes
    • tongue thrust swallowing.

    Facial and dental signs

    • narrow palate
    • crowded teeth
    • open bite
    • overbite
    • underbite
    • long face appearance
    • receding chin
    • poor lip seal.

    If several of these signs sound familiar, a comprehensive assessment may be worthwhile.

    Why does mouth breathing matter?

    Many parents assume mouth breathing is simply a habit.

    In reality, mouth breathing is often a symptom that something is preventing efficient nasal breathing.

    Common causes include:

    • enlarged tonsils
    • enlarged adenoids
    • allergies
    • chronic nasal congestion
    • recurrent infections
    • structural airway differences
    • tongue tie
    • prolonged dummy use
    • thumb sucking
    • poor oral posture.

    When nasal breathing becomes difficult, children naturally begin breathing through their mouths.

    Over time, this can affect how the face, jaws and airway develop.

    What does healthy oral posture look like?

    Healthy oral posture is surprisingly simple:

    • lips
      • gently closed
    • tongue
      • resting against the roof of the mouth
    • teeth
      • slightly apart
    • breathing
      • through the nose.

    This posture helps guide healthy jaw growth, facial development and airway formation.

    Think of the tongue as a natural orthodontic support system. When it rests in the correct position, it helps shape the upper jaw and supports healthy facial growth.

    The consequences of chronic mouth breathing

    1. Speech difficulties

    Children who breathe through their mouths often have altered tongue posture and reduced oral stability.

    This can contribute to:

    • lisping
    • distorted sounds
    • reduced speech clarity
    • difficulty learning new speech sounds.

    2. Feeding and swallowing difficulties

    A low tongue posture may affect:

    • chewing efficiency
    • swallowing patterns
    • food management
    • oral motor coordination.

    Many children develop a tongue thrust swallow, where the tongue pushes forward instead of moving efficiently during swallowing.

    3. Poor sleep quality

    Mouth breathing can contribute to:

    • snoring
    • restless sleep
    • frequent waking
    • daytime fatigue
    • reduced concentration.

    Poor sleep can have a significant impact on learning, behaviour and emotional regulation.

    4. Changes to facial growth

    Over time, chronic mouth breathing may influence:

    • jaw development
    • facial proportions
    • dental alignment
    • airway size.

    This can result in:

    • narrow palates
    • crowded teeth
    • long facial appearance
    • increased orthodontic needs.

    5. Oral health concerns

    The nose acts as a natural filter and humidifier.

    When children breathe through their mouths:

    • The mouth becomes dry.
    • Saliva protection is reduced.
    • Risk of tooth decay increases.
    • Gum health may be affected.

    Why this matters for speech therapy

    Speech does not develop in isolation.

    The tongue, lips, jaw and airway work together to support clear communication.

    At London Speech and Feeding, we look beyond speech sounds alone.

    A child who presents with:

    • persistent speech difficulties
    • lisping
    • feeding challenges
    • open mouth posture
    • snoring
    • poor sleep

    may benefit from an assessment that explores underlying orofacial myofunctional factors.

    Addressing these foundations can often support more effective progress in speech and feeding therapy.

    How London Speech and Feeding can help

    A comprehensive assessment may include observation of:

    • breathing patterns
    • lip posture
    • tongue posture
    • swallowing function
    • feeding skills
    • speech sound development
    • sleep concerns
    • oral structures.

    Where appropriate, recommendations may include:

    • orofacial myofunctional therapy
    • speech therapy
    • feeding therapy
    • home programmes
    • ENT referral
    • orthodontic referral
    • collaborative multidisciplinary support.

    The good news

    Orofacial Myofunctional Disorders are often highly treatable when identified early.

    Supporting healthy breathing, tongue posture and oral muscle function can positively influence:

    If your child regularly breathes through their mouth, snores, struggles with speech clarity or has feeding difficulties, a specialist assessment may help identify the underlying cause.

    • speech clarity
    • feeding skills
    • sleep quality
    • facial growth
    • dental development
    • overall wellbeing.

    At London Speech and Feeding, we are passionate about looking beyond symptoms and understanding the whole child. Contact me!

    Sometimes the key to clearer speech starts with a simple question:

    ‘Is my child breathing through their nose?’

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.

    Frequently Asked Questions

    Can mouth breathing cause speech problems?

    Yes. Mouth breathing can alter tongue posture, lip strength and oral stability, which may contribute to articulation difficulties and lisps.

    Should I be worried if my child snores?

    Regular snoring is not considered normal in children and may indicate airway obstruction or sleep-disordered breathing.

    Can enlarged tonsils affect speech?

    Yes. Enlarged tonsils may affect resonance, tongue positioning, swallowing and breathing patterns.

    What age can children be assessed?

    Children of all ages can be assessed if parents have concerns about speech, feeding, breathing or oral development.

    What is Orofacial Myofunctional Therapy?

    Orofacial Myofunctional Therapy focuses on improving breathing patterns, tongue posture, lip seal and oral muscle function to support overall health and development.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3