Could mouth breathing be affecting your child’s speech, sleep and development?
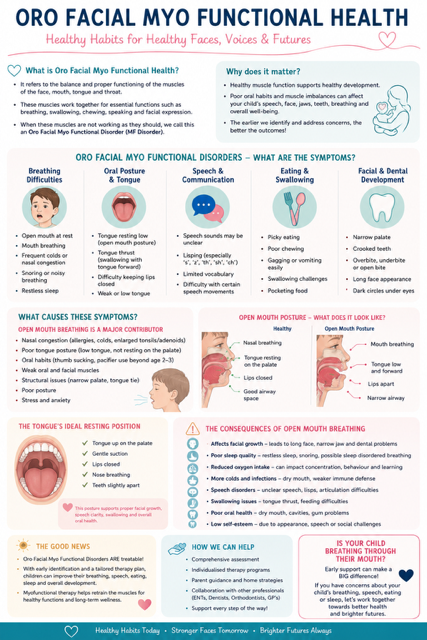
Could mouth breathing be affecting your child's speech, sleep and development?

Understanding Orofacial Myofunctional Disorders (OMDs)

Many parents contact me at London Speech and Feeding because they are worried about their child’s speech. Perhaps their child is difficult to understand, has a persistent lisp, struggles with feeding, snores at night, or always seems to have their mouth open.

What many families don’t realise is that these concerns may all be connected.

Increasingly, research and clinical experience are highlighting the important role of Orofacial Myofunctional Health, the way the muscles of the face, mouth, tongue and airway work together to support breathing, eating, sleeping and communication.

When these muscles are not functioning optimally, children may develop what are known as Orofacial Myofunctional Disorders (OMDs).

What Is Orofacial Myofunctional Health?

Orofacial Myofunctional Health refers to the healthy function and coordination of the:

  • lips
  • tongue
  • jaw
  • cheeks
  • facial muscles
  • airway.

These structures play a vital role in:

  • breathing
  • swallowing
  • chewing
  • speaking
  • facial growth
  • dental development
  • sleep quality.

When everything is working well, the lips remain gently closed at rest, breathing occurs through the nose, and the tongue rests against the roof of the mouth.

This seemingly simple posture has a profound influence on how a child’s face, teeth and airway develop.

What is an Orofacial Myofunctional Disorder?

An Orofacial Myofunctional Disorder occurs when there is an abnormal pattern of muscle function involving the face, mouth, tongue or airway.

Children with OMDs may experience difficulties with:

  • speech
  • feeding
  • swallowing
  • sleep
  • breathing
  • dental development
  • facial growth.

In many cases, these difficulties are linked to chronic mouth breathing.

Signs your child may have an Orofacial Myofunctional Disorder

Breathing and sleep signs

  • mouth open at rest
  • mouth breathing during the day
  • snoring
  • noisy breathing
  • restless sleep
  • frequent waking
  • dark circles under the eyes
  • chronic congestion
  • fatigue despite a full night’s sleep.

Speech signs

  • lisping
  • unclear speech
  • distorted speech sounds
  • difficulty producing certain sounds
  • persistent articulation difficulties
  • reduced speech intelligibility.

Feeding and swallowing signs

  • picky eating
  • messy eating
  • food remaining in the cheeks
  • gagging easily
  • difficulty chewing
  • long mealtimes
  • tongue thrust swallowing.

Facial and dental signs

  • narrow palate
  • crowded teeth
  • open bite
  • overbite
  • underbite
  • long face appearance
  • receding chin
  • poor lip seal.

If several of these signs sound familiar, a comprehensive assessment may be worthwhile.

Why does mouth breathing matter?

Many parents assume mouth breathing is simply a habit.

In reality, mouth breathing is often a symptom that something is preventing efficient nasal breathing.

Common causes include:

  • enlarged tonsils
  • enlarged adenoids
  • allergies
  • chronic nasal congestion
  • recurrent infections
  • structural airway differences
  • tongue tie
  • prolonged dummy use
  • thumb sucking
  • poor oral posture.

When nasal breathing becomes difficult, children naturally begin breathing through their mouths.

Over time, this can affect how the face, jaws and airway develop.

What does healthy oral posture look like?

Healthy oral posture is surprisingly simple:

  • lips
    • gently closed
  • tongue
    • resting against the roof of the mouth
  • teeth
    • slightly apart
  • breathing
    • through the nose.

This posture helps guide healthy jaw growth, facial development and airway formation.

Think of the tongue as a natural orthodontic support system. When it rests in the correct position, it helps shape the upper jaw and supports healthy facial growth.

The consequences of chronic mouth breathing

1. Speech difficulties

Children who breathe through their mouths often have altered tongue posture and reduced oral stability.

This can contribute to:

  • lisping
  • distorted sounds
  • reduced speech clarity
  • difficulty learning new speech sounds.

2. Feeding and swallowing difficulties

A low tongue posture may affect:

  • chewing efficiency
  • swallowing patterns
  • food management
  • oral motor coordination.

Many children develop a tongue thrust swallow, where the tongue pushes forward instead of moving efficiently during swallowing.

3. Poor sleep quality

Mouth breathing can contribute to:

  • snoring
  • restless sleep
  • frequent waking
  • daytime fatigue
  • reduced concentration.

Poor sleep can have a significant impact on learning, behaviour and emotional regulation.

4. Changes to facial growth

Over time, chronic mouth breathing may influence:

  • jaw development
  • facial proportions
  • dental alignment
  • airway size.

This can result in:

  • narrow palates
  • crowded teeth
  • long facial appearance
  • increased orthodontic needs.

5. Oral health concerns

The nose acts as a natural filter and humidifier.

When children breathe through their mouths:

  • The mouth becomes dry.
  • Saliva protection is reduced.
  • Risk of tooth decay increases.
  • Gum health may be affected.

Why this matters for speech therapy

Speech does not develop in isolation.

The tongue, lips, jaw and airway work together to support clear communication.

At London Speech and Feeding, we look beyond speech sounds alone.

A child who presents with:

  • persistent speech difficulties
  • lisping
  • feeding challenges
  • open mouth posture
  • snoring
  • poor sleep

may benefit from an assessment that explores underlying orofacial myofunctional factors.

Addressing these foundations can often support more effective progress in speech and feeding therapy.

How London Speech and Feeding can help

A comprehensive assessment may include observation of:

  • breathing patterns
  • lip posture
  • tongue posture
  • swallowing function
  • feeding skills
  • speech sound development
  • sleep concerns
  • oral structures.

Where appropriate, recommendations may include:

  • orofacial myofunctional therapy
  • speech therapy
  • feeding therapy
  • home programmes
  • ENT referral
  • orthodontic referral
  • collaborative multidisciplinary support.

The good news

Orofacial Myofunctional Disorders are often highly treatable when identified early.

Supporting healthy breathing, tongue posture and oral muscle function can positively influence:

If your child regularly breathes through their mouth, snores, struggles with speech clarity or has feeding difficulties, a specialist assessment may help identify the underlying cause.

  • speech clarity
  • feeding skills
  • sleep quality
  • facial growth
  • dental development
  • overall wellbeing.

At London Speech and Feeding, we are passionate about looking beyond symptoms and understanding the whole child. Contact me!

Sometimes the key to clearer speech starts with a simple question:

‘Is my child breathing through their nose?’

Sonja McGeachie

Highly Specialist Speech and Language Therapist

Owner of The London Speech and Feeding Practice.

Frequently Asked Questions

Can mouth breathing cause speech problems?

Yes. Mouth breathing can alter tongue posture, lip strength and oral stability, which may contribute to articulation difficulties and lisps.

Should I be worried if my child snores?

Regular snoring is not considered normal in children and may indicate airway obstruction or sleep-disordered breathing.

Can enlarged tonsils affect speech?

Yes. Enlarged tonsils may affect resonance, tongue positioning, swallowing and breathing patterns.

What age can children be assessed?

Children of all ages can be assessed if parents have concerns about speech, feeding, breathing or oral development.

What is Orofacial Myofunctional Therapy?

Orofacial Myofunctional Therapy focuses on improving breathing patterns, tongue posture, lip seal and oral muscle function to support overall health and development.


Health Professions Council registered
Royal College of Speech & Language Therapists Member
Member of ASLTIP

Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

3

Similar Posts

  • · ·

    Neurodiversity affirming Speech and Language Therapy

    Introduction

    I am a neurodiversity affirming therapist and I love and endorse play-based therapy. I use it alongside a strengths-focused approach in all my sessions. Find out why we should use these transformative therapy methodologies in all our work and play with our children.

    I always have a range of different toys and activities up my sleeve so that when one toy is no longer interesting, that’s fine. ‘Look here’s a new one, how about we try this one?’ When therapy feels like play, children are more likely to be engaged and attentive, which leads to better outcomes.

    By using play as a context for Speech and Language Therapy we can create opportunities for children to use and practise their communication skills in a natural, real-life setting. This helps bridge the gap between the therapy room and everyday life.

    Goals and targets

    What about goals and targets I hear you say? Of course, as Speech and Language Therapists we always have our goals for any particular child. They can be speech goals (we want Bobbi to produce a ‘k’ sound at the end of words) or communication goals (we want Fatima to ask for something by pointing to it rather than grabbing it). And these goals can be achieved where there is a reciprocation and a positive, playful relationship between the adult and the child. That relationship comes through play and fun.

    Play and fun

    Play is how a child interacts and learns. If it’s fun, interesting, exciting or pleasurable then that is where the magic happens. And that is what we need to return to repeatedly and then see if we can fold our targets into the activity as we go.

    As soon as we expect our child to do something and we try and shape their behaviours towards a certain outcome we no longer ‘play’. We are now in teaching mode, where we direct and where we are ‘in charge’. As a neurodiversity affirming therapist, I believe that all play is valid. We must not get into the trap of thinking that only functional play is valid, that there is only one way to play with that car ramp/puzzle/potato head. Our autistic children often need to play in a particular way to navigate their world and we must not try and stop that.

    When we affirm and validate our child’s play and copy their play with enthusiasm and respect then, in my experience, all children regardless where they are on the neurodiversity spectrum will begin to engage with us, copy us, and learn how to communicate effectively about things that matter to them.

    Play-based therapy allows therapists to tailor interventions to each child’s unique interests and abilities. This individualised approach increases the likelihood of success and progress.

    Strengths-Focused Speech Therapy

    Strengths-focused therapy emphasizes a child’s strengths and abilities rather than their deficits. It recognises that every person has unique strengths that can be harnessed to overcome challenges.

    Focusing on strengths helps us build a positive self-image. This is especially important for children with communication disorders, as it can boost their confidence and self-esteem.

    When we encourage children to play in ways that they enjoy and are good at they feel empowered and more in control of their lives and play. This can lead to increased motivation and a sense of ownership over their progress.

    Now, imagine the powerful impact that can be achieved by combining play-based therapy and strengths-focused therapy in speech therapy sessions. This dynamic combination brings out the best of both worlds. It creates a therapeutic environment that is not only effective but also enjoyable for children and their families.

    As Speech Therapists we can use the child’s strengths and interests as a foundation for play-based activities. This personalisation not only makes therapy more engaging but also more effective.

    An example

    Charlie, a 3-year-old with social communication challenges, had a deep interest in anything that spins. We used this strength and interest to create a variety of spinning activities. As he is allowed to engage in his spinners, we can practise lots of speech and language and provide great phrases alongside his interest and activities: Ready steady go! Stop! ‘another one’ ‘the red one’ ‘again again’ ‘I love it’ ‘it’s a spinner’ ‘Charlie loves this toy’ ‘it’s going fast’ ‘it’s so fun’ etc..

    Over time Charlie started to copy some of these word models and then used them to create his own little phrases, such as ‘the blue one again’. When this occurred, we felt like celebrating because it had come naturally and appropriately to the situation without any coercion or direction. That is what communication is about! Well done Charlie!

    Conclusion

    Play-based and strengths-focused speech therapy approaches are powerful tools and by combining these approaches, we create a therapeutic environment that is not only effective but also enjoyable and empowering for our clients.

    Contact me if you would like your child to have neurodiversity affirming speech and language therapy.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    0
  • Submucous cleft palate: What is it and how does it impact on speech?

    Submucous cleft palate: What is it and how does it impact on speech?

    What exactly is a submucous cleft palate?

    A submucous cleft palate (SMCP) is much less obvious than its counterparts, cleft of lip and/or palate, and can profoundly impact a child’s speech development. It leads to often extreme hyper nasal speech and difficulty with producing many sounds (/K/ /G/ /T/ /D/ /P/ /B/ /S/ /Z/ /F/ /V/).

    In short, the muscles and bone of the soft palate, and sometimes the hard palate, do not fuse completely during foetal development and the mucous membrane that lines the roof of the mouth remains intact, effectively camouflaging the underlying muscular and bony deficit.

    So, while the surface of the palate appears normal, the essential muscle and functions responsible for sealing off the nasal cavity from the oral cavity during speech are compromised. This cleft (or lack of muscle) can be seen as a bluish midline discoloration of the soft palate, often a bifid (split) uvula, and at times a notch in the posterior border of the hard palate can be felt upon palpation. However, these signs aren’t always present or easily discernible, contributing to the difficulty arriving at a diagnosis.

    Diagnosing a submucous cleft palate is often akin to searching for a needle in a haystack, especially for the untrained eye. Unlike overt clefts that are visually apparent at birth, an SMCP can go undiagnosed for years, sometimes well into childhood or even adolescence. Paediatricians and even ENT surgeons have been known to miss it during routine checks due to the intact mucosal lining. Parents might notice their child’s speech sounds ‘different’ or ‘nasal’ but struggle to pinpoint the cause. Children might undergo extensive speech therapy without a proper diagnosis, as the underlying structural issue continues to hinder progress.

    My experience as a speech therapist in private practice:

    Over my years of practice, I have encountered several children presenting with persistent hyper-nasal speech and significant difficulties producing plosive and fricative sounds.

    It has been incredibly rewarding, though at times challenging, to successfully diagnose SMCP in a number of these children. My approach often involves:

    • a meticulous oral motor examination,
    • careful listening for the specific qualities of hypernasality,
    • and a deep understanding of the physiological requirements for clear speech sound production.

    When I suspect an SMCP, I refer these children to Great Ormond Street Hospital where a fantastic multidisciplinary team, typically including ENT surgeons and a specialist speech-language therapist can conduct more definitive assessments. These assessments often involve instrumental analyses such as videofluoroscopy or nasoendoscopy, which provide objective measures of velopharyngeal function and visual confirmation of the anatomical deficit.

    The path to resolution: surgery, therapy, and successful outcomes

    Surgery

    The journey for these children, once diagnosed, often involves surgical intervention. It’s not uncommon for children with SMCP to undergo multiple operations to achieve optimal velopharyngeal closure. These procedures aim to reconstruct or augment the velopharyngeal mechanism, enabling it to effectively separate the oral and nasal cavities during speech. The specific surgical approach depends on the individual child’s anatomy and the severity of the velopharyngeal insufficiency. It’s a testament to the skill of these specialised surgeons that such intricate repairs can be performed with remarkable success.

    Speech therapy

    Following surgery these children embark on the crucial phase of speech therapy. While surgery addresses the structural problem, speech therapy helps a child learn to utilise their newly improved anatomy. It involves intensive work on developing oral airflow, establishing correct articulatory placement, and reducing learned compensatory strategies that have developed due to the original structural deficit. It is immensely gratifying to witness the transformation. Children who once struggled to produce basic sounds, whose speech was difficult to understand, gradually develop clear speech.

    Next steps?

    If you’re a parent concerned about your child’s speech and feeding, you’re not alone. The journey can feel confusing, but professional guidance can make all the difference. Never hesitate to have a second opinion when you have that niggling feeling that there is something that has not yet been explored. At London Speech and Feeding I specialise in being thorough and thinking outside the box.

    I am here to provide the support you need. Reach out to schedule a consultation and take the first step towards helping your child communicate and thrive.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • ·

    Target activities and games

    Target Activities and Games For Kids
    Target Activities and Games For Kids

    Target Activities and Games

    AMAZINGLY EASY Activities that we can do at home and in the clinic to help our children practise those targets!

    I bet you have wondered what amazing things are done by a therapist in the clinic that you could not possibly do at home…? Well, if so I am here to tell you that you will be absolutely fine with just a few select toys and games and you will be able to get those targets done in a jiffy!

    What we clinicians do very well and what you probably can’t do yourself is formulate and design the targets that are important for your child to practice. Once we have assessed or reviewed your child’s progress and needs we can then design the perfect next step of targets for you.

    So for example, we have decided your little one needs to be practicing their ‘r’ sounds at the beginning of short words. We decided that based on our clinical expertise and our assessment and we have already worked with your child and managed to get this tricky ‘r’ sound just about right on its own. Now we are ready for short word practice.

    It has been researched that in order for the brain pathways to re-shape or reform we need to get about 100 words in per day of our target sound. That sounds like quite a lot, right? But actually….. it’s not that bad. After all you only need to say 5-7 words about 20 times and hey presto that’s about 80-100 words.

    So here are some simple games I use in my clinic all the time and these games are easily available online or in your local toy shops and this is how to do them:

    Pop the Pirate

    Pop the Pirate, sooo good and popular:

    Lay out your target words which you will have been given by your speech therapist and put a few swords on each word.

    Each time your child picks up a sword they will need to say the target word 5 x, like:

    rip rip rip rip rip or run run run run run just like that in a row, bish bash bosh.

    Then they can stick the sword into the barrel. Onto the next sword which they can pick and then again

    race race race race race and stick in another sword

    So with this little lot I put out 5 target words and 3 swords on each.

    You will therefore get…… 15 words per picture, and that makes….75 words , there that is nearly all you need to do.

    If you then do another little game like this one:

    Magnetic board game

    This is a Magnetic Board game, and they are suddenly EVERYWHERE. But you could also just take a baking sheet and some fridge magnet you might have kicking about.

    Same principle as before, but now since this is your SECOND game of the day and you have already got 75 targets under your belt you only need to do one more round of 5 target words each:

    Each time your child picks up a magnet piece they will say the target word 5 more times:

    Ray ray ray ray ray and DONE you will now at the end of this short round have 105!! target words done with just two little fun games.

    How good is this? Your child won’t hardly notice that they are in fact doing their speech therapy homework.

    You’re welcome 🙂

    Get in touch if you would like me to help finding good targets for your child to work on. They can be speech and/or language targets with this game method.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • Speech sound disorders

    Kids Speech Therapist London
    Speech Sound Disorders

    Treatment Approaches – A Typical Session

    There are various great ways to treat speech sound disorders and I use all the approaches available selectively; I decide what works with each individual child and I also vary the approach depending on the child’s frame of mind at any given time during my session.

    Some of the approaches are more “drill-based” and require a child to be able to pay attention and really participate actively in the therapy, and this is what I am showing you today with this video clip.

    My little student here has been working with me for some time and from only saying a handful of words which were not very easy to understand he has come a long way. He does have some features of Verbal Dyspraxia which I shall briefly outline here:

    • Making sounds in general is a struggle, especially when asked to copy certain sounds, example: ‘can you say: a ee ou oo?”
    • Repeating sound sequences or words sequences is hard, for example: “say p-t-k in sequence” or “say fish chips fish chips fish chips
    • When saying the same word again and again, different mistakes can be heard
    • Intonation difficulties: speech sounds monotonous
    • Vocabulary is very limited

    Some therapy approaches are more play based, for example the Core Word method: here we pick a few words at a time which are very significant to the child and therefore highly motivating to try and say. These could be characters of Pokemon or Minecraft for example, or simple words like “GO!”

    When you watch the video you will see that I use a lot of visual prompting, such as showing him where the tongue is moving to or from. I do this with my index finger and this approach is called Tactile Cueing or “Cued Articulation”. Part of the approach is to give a visual prompt and then reduce the prompt as the learner is more able to produce the correct sounds. Once he can produce the sound on its own, we quickly move to the sound within a word.

    I do mix and match my approaches and in fact here I am drilling but I also use the Core Word which for him (YELLOW) — it’s his favourite colour and I happen to have quite a few good games where a YELLOW something or other can be asked for….. WHO KNEW!? 🙂


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • ·

    Support your child’s communication using books: OI FROG

    Sonja's top recommendation: Oi Frog, written by Kes Gray and Jim Field. An exciting book for children to enhance their speech, language and communication.
    Oi Frog by Kes Gray and Jim Field

    Book corner with Oi Frog! by Kes Gray and Jim Field.

    Books are an engaging way to support your child’s communication development. Even if your little one dislikes reading in the traditional sense. They will become immersed in this adventure, without realising they are taking in language and developing vital communication skills. This is one of my favourite series for children.

    Increase fun and interaction

    These books are made for fun and excitement! It may seem silly putting on different voices for different characters, but this is one way in which you can engage your child. Why not try to use different intonation patterns (e.g., you may use a deep voice for the dog, and a higher pitch for the cat)? Make your story interactive: you could ‘rawww’ like a lion and see who can make the loudest noise. Make noises to encourage interaction (e.g., when scratching his chin, make a squeaky sound!). You could also relate the experience back to your child (e.g., ‘can you scratch your chin?’).

    Time to talk

    Talk about what you can see on the front cover (e.g., There’s a frog on a log, how funny!) You could also ask your child to choose the rhyming words on a page in the book. Can your child tell you what rhymes with certain words (e.g., can you guess what a parrot sits on?)? Make use of every page. You could comment on your favourite frog and see if your child can talk about their favourite. You can support them by giving them an example (“my favourite frog is the one swimming backwards because he looks funny”). Then you could use this scaffold to support their answer. Your favourite is [________________] because [_________________]

    If your child is reluctant to use language, the use of commenting can take the pressure of them (“look at all those frogs” or “he’s climbing up the stool”) is a powerful way in which you (as parents) can take the pressure off your child. A top tip I like to give is to make sure you pause regularly, which creates opportunities for your child to use language.

    This book uses a subject-verb-object sentence structure (e.g., ‘hares sit on chairs’) which allows your child to hear a good model of a sentence. You could also talk about things in the book that belong in a certain category (e.g., animals, food) or begin with a specific sound. See if your child will name any more.

    Reap the reward of repetitive language

    Oi Frog uses repetitive rhyming language and puts emphasis on these words. This is important because the more your child hears a word, the more likely they are to remember, understand and use it in the correct context.

    Emotions matter

    Talk about how the animals feel and why they may feel this emotion (e.g., the cat’s feeling annoyed because…, Lions sit on irons, how does the lion feel?). Reasons can be difficult for children with communication difficulties. Support them by giving an example or by giving them an option (e.g., “does the lion feel happy or sad? I think the lion feels sad because he’s burnt his bottom on the iron! It’s too hot!”)

    A collection of books
    OI Books

    Why not read similar stories? I highly recommend OI CAT, OI DOG and OI DUCK-BILLED PLATYPUS.

    Need support for your child’s communication? Contact me here.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    2
  • ·

    Supporting children and families living with verbal dyspraxia

    “It’s brill-i-ant, it’s brill-ant, it’s brillnt”

    Have you ever wondered why children may pronounce a word correctly one minute and in the next breath they struggle to say the same word? It’s equally as frustrating for you as it is for your child. The biggest question of all is WHY? Why does this happen and what causes it? Whilst there are many explanations. When it persists, it might be a condition called verbal dyspraxia.

    What is verbal dyspraxia

    Verbal dyspraxia is a neurological motor speech disorder that affects the coordination and planning of muscle movements that are needed for speech production. A child may have difficulty making the precise movements needed for speech, which may result in inconsistent and unintelligible speech. Children may also have trouble sequencing sounds and syllables, producing speech sounds accurately, and coordinating the movements of their articulators (e.g., lips, tongue, teeth, jaw). This can lead to a range of speech errors (including sound distortions, substitutions, omissions, and difficulty with rhythm and prosody).

    We know that these speech errors, and not being able to get a message across, can be frustrating for children with speech difficulties. Can you imagine talking and limited people understanding you? It’s so tough on children and the people trying to communicate with them.

    Creating a person-centred therapy plan is vital. This allows your child to stay motivated, as intervention is likely to be long term. This planning may include favourite words to use during their hobby or favourite activity, or person-centred goals such as ‘giving Alexa an instruction’.

    Children with verbal dyspraxia can have several different ways of producing words, which often makes it trickier for them as there’s no consistent pattern to work with. So, we’ve put together some top tips to support their communication and make their (and your) lives a little easier in the process.

    Ten ways to make communication easier for your child with verbal dyspraxia

    • Have a list of frequently used words and practise this set. Little and often is best!
    • Use cued articulation to support speech production (ask your Speech and Language Therapist for the gestures)
    • Give time and use active listening. This means showing interest and trying not to think about what is on your never ending ‘to do’ list
    • Reduce frustration in any way that you can. This might mean allowing your child to demonstrate using gestures rather than speech. You might also give top tips for other adults or children who communicate with your child when out and about
    • Talk about the structure of words with your child (i.e., there are two beats/syllables in this word)
    • Show the written form of the word to go alongside their production
    • Split down tasks, so that your child only has to respond to one question at a time, reducing their motor capacity
    • Recognise when your child is working well and when they may need support of an Alternative and Augmentative Communication device
    • Allow all environments to have the same training and equipment (i.e., at school, home, out and about)
    • Have regular periods in the day where your child can practise their specific words in different environments. This can be effective for children with verbal dyspraxia

    Do you still have questions? Contact Sonja for support.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    0
