There are various great ways to treat speech sound disorders and I use all the approaches available selectively; I decide what works with each individual child and I also vary the approach depending on the child’s frame of mind at any given time during my session.
Some of the approaches are more “drill-based” and require a child to be able to pay attention and really participate actively in the therapy, and this is what I am showing you today with this video clip.
My little student here has been working with me for some time and from only saying a handful of words which were not very easy to understand he has come a long way. He does have some features of Verbal Dyspraxia which I shall briefly outline here:
Making sounds in general is a struggle, especially when asked to copy certain sounds, example: ‘can you say: a ee ou oo?”
Repeating sound sequences or words sequences is hard, for example: “say p-t-k in sequence” or “say fish chips fish chips fish chips
When saying the same word again and again, different mistakes can be heard
Intonation difficulties: speech sounds monotonous
Vocabulary is very limited
Some therapy approaches are more play based, for example the Core Word method: here we pick a few words at a time which are very significant to the child and therefore highly motivating to try and say. These could be characters of Pokemon or Minecraft for example, or simple words like “GO!”
When you watch the video you will see that I use a lot of visual prompting, such as showing him where the tongue is moving to or from. I do this with my index finger and this approach is called Tactile Cueing or “Cued Articulation”. Part of the approach is to give a visual prompt and then reduce the prompt as the learner is more able to produce the correct sounds. Once he can produce the sound on its own, we quickly move to the sound within a word.
I do mix and match my approaches and in fact here I am drilling but I also use the Core Word which for him (YELLOW) — it’s his favourite colour and I happen to have quite a few good games where a YELLOW something or other can be asked for….. WHO KNEW!? 🙂
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
As parents, we spend a massive portion of our days multi-tasking. We are talking to our toddlers while washing dishes, shouting encouraging words from across the living room while folding laundry, or answering their questions from a few feet above them while walking through the supermarket. It is a completely natural dynamic, after all, the adult world happens up here, and their world happens down there.
But when it comes to actively boosting your child’s speech and language development, one of the simplest, most profound changes you can make costs absolutely nothing and requires no special training.
It is simply this: Get down on the floor, sit cross-legged, and get face-to-face.
At London Speech and Feeding I call this physical positioning ‘face to face’. It is also one of the major ‘Hanen Programme’ Strategies. It completely reshapes how your child interacts with you, transforms how they process language, and turns ordinary playtime into an instant communication opportunity.
Our mouth is the magic: Visual cueing and speech imitation
When a child is learning to talk, they aren’t just listening to the sounds you make; they are watching how you make them.
Speech is an incredibly complex motor skill. To say a single word, the brain must coordinate the lips, tongue, teeth, jaw, and vocal cords in a fraction of a second. When you speak to your child from a standing or even a seated chair position while they are on the floor, your mouth is entirely out of their direct line of sight. They miss the visual roadmap of speech.
When you sit right in front of them at eye level:
They see mouth shapes: They can see how your lips round for an /OO/ sound, how your teeth touch your lip for an /F/ sound, or how wide your mouth opens for an /AH/.
They read facial expressions: Emotions give context to words. Seeing your eyes widen with excitement or your eyebrows lift in surprise helps them map meaning onto the vocabulary you are using.
They mimic naturally: By putting your face directly in your child’s field of vision, you make it infinitely easier for her or him to try and copy your oral movements.
If you are working on a specific word like ‘pop’ while blowing bubbles or ‘more’ during snack time getting your face just a foot or two away from your child gives her or him the front-row seat she or he needs to learn the mechanics of that word.
Unlocking joint attention: The foundation of all languages
Before a child can say their first words, they need to master a milestone called joint attention.
What is joint attention?
It is the magic moment when a child looks at an object (like a toy train), looks up at you to share their excitement, and then looks back at the object. It is a three-way loop of shared experience.
Without joint attention, communication cannot thrive. If a child is entirely hyper-focused on a toy and ignoring your presence, or if you are commenting on a book they aren’t looking at, true communication isn’t happening.
When you get down on the floor on a play mat, you naturally insert yourself into their bubble. You aren’t a distant narrator anymore; you are a co-player. Being at their level makes it incredibly easy for their eyes to flick from the toy straight to your face. This shared gaze is the exact moment language takes root. It signals to the child, ‘We are experiencing this together, and this thing we are doing has a name.’
The ‘wait and see’ technique
Once you are down on the floor, the temptation is often to take over by pointing at everything, asking a million questions like ‘What’s that?’, ‘Is that a blue train?’, or somehow driving the play.
Instead, the most powerful thing you can do at eye level is to practise the ‘Wait and See’ technique.
In the video clip you can see this exact dynamic in action. Look at how I am sitting cross-legged on the mat, at eye level with the toddler. Notice how my hands are on the toy container, but my eyes are locked on the child. I am not forcing the interaction; instead, I am waiting.
Here is how you can use this strategy at home:
Set the stage: Get down on their level with a high-interest toy that requires help (like a wind-up toy, bubbles, or a tight-lidded box with toys inside).
Create anticipation: Hold the object near your face or place your hands on it, but don’t open or activate it right away.
Lean in and wait: Lean slightly forward, open your eyes wide, adopt an expectant facial expression, and completely pause. Count to five or ten in your head. Do not say anything.
Capture the gaze: Wait for the exact moment your child looks up from the toy to meet your eyes, as if to say, ‘Well? Are you going to open it?’
Reward the eye contact: The instant they make eye contact, deliver the language reward! Model a simple, functional word like ‘Open!’, ‘Go!’, or ‘Look!’ as you immediately do the action.
By pausing and waiting at eye level, you create a ‘communication temptation’. The child learns that looking at you and engaging with your face is the key that unlocks the fun.
Making it a daily habit
You don’t need to spend hours a day sitting on the floor to see a difference. Start small by dedicating just 10 to 15 minutes of undivided, face-to-face play time each day. Turn off the television, put your phone in another room, get down on their level, and let them lead the play while you focus on being their visual communication partner.
Whether you’re opening a little toy briefcase, pushing a plastic train along a track, or stacking blocks, remember: your face is the best toy in the room.
Are you wondering if your toddler’s speech and language milestones are on track? At London Speech and Feeding I love helping families navigate early communication. Feel free to explore my services page and reach out directly to schedule a consultation.
Sonja McGeachie
Highly Specialist Speech and Language Therapist
Owner of The London Speech and Feeding Practice.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
Childhood Apraxia of Speech (CAS) is a complex neurological disorder that affects a child’s ability to plan and coordinate the movements necessary for speech production. Children with CAS often have difficulty with articulation, prosody, and fluency, making it challenging for them to communicate effectively. While there is no cure for CAS, speech and language therapy can significantly improve a child’s communication skills and overall quality of life. Understanding the principles of motor learning is crucial for both parents and speech therapists to support children with CAS on their speech journey.
What is MOTOR LEARNING?
Motor learning refers to the process of acquiring and refining new skills through practice and experience. This applies to all aspects of movement, including speech production. The brain constantly receives sensory information about the movements being made and adjusts them based on the desired outcome. A breakdown or interruption of this process can make it difficult for children to plan, sequence, and coordinate the intricate movements involved in speech.
What key principles do we use in speech and language therapy for motor learning?
Task Specificity: Speech Therapy activities that directly target the specific speech sounds or skills your child is working on. For example, if your child is struggling with /p/, practising isolated /p/ sounds, words with /p/, and phrases with /p/ would be most beneficial.
Massed vs. Distributed Practice: We consider the optimal amount and distribution of practice sessions throughout the day. Massed practice involves concentrated practice in a single session, while distributed practice spreads practice sessions throughout the day. The best approach depends on the individual child’s learning style and attention span.
Feedback: We provide clear and immediate feedback to help your child understand the accuracy and effectiveness of their attempts. This feedback can be auditory, visual, or touch based.
Error Correction: We aim to gently correct errors so that we can help your child refine their movements and avoid developing bad habits. The focus is on providing specific cues and guidance rather than simply pointing out mistakes.
Variety and Progression: We gradually introduce new challenges and variations in speech therapy activities to prevent plateaus and maintain motivation.
Motivation and Engagement: A big part of our work is to make therapy sessions fun and engaging to keep your child motivated and actively participating. We use games, songs, and activities that your child enjoys while incorporating targeted practice opportunities.
What about home work?
Yes we need your help and here are some examples of how this could look:
Task Specificity: During story time, focus on practising target sounds present in the story. Have your child repeat words or phrases containing the sound and encourage them to identify the sound in other words.
Massed vs. Distributed Practice: Instead of one long practice session, try shorter, more frequent sessions throughout the day. This can help maintain focus and prevent fatigue. It is recommended to go for 100 repetitions of the target sound per day, every day in between the sessions. We can decide together how you can best do that through either massed or distributed practice. We can decide after the session.
Feedback: Use a mirror to provide visual feedback on lip and tongue placement during sound production. Record the child’s speech and play it back to help them self-monitor their accuracy.
I quite like this mirror below but any table top mirror will work as long as it is not too small. Your child should see their whole face easily.
Error Correction: If the child makes an error, gently model the correct sound or movement without shaming or criticising. Provide specific cues such as ‘lips together’ for /p/ or ‘tongue up’ for /t/.
Variety and Progression: We will guide you on exactly what words to practise so this is something you need not worry about.
Motivation and Engagement: Use games, songs, and activities that your child enjoys. Play a game of ‘I Spy’ focusing on words with the target sound or create silly sentences with the sound to make practice fun.
Let’s work together!
It is crucial for parents, therapists, and other caregivers to work collaboratively to ensure a consistent and comprehensive approach to supporting your child’s speech development. Speech and Language Therapists can provide guidance and resources on implementing these principles at home, while parents can share observations and progress updates to inform therapy sessions.
Remember, every child with CAS learns at their own pace. By understanding and applying the principles of motor learning, parents and speech therapists can create a supportive and stimulating environment that empowers children with CAS to reach their full communication potential.
Do get in touch if you would like some in-person or on-line 1:1 support with this. It can be overwhelming to figure it all out alone.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
When a child’s speech is difficult to understand, it can feel overwhelming for everyone involved. As a parent, your instinct is often to focus on helping your child ‘talk properly’. And that makes complete sense. Speech is important. But here’s the key message I want to share with you:
Speech is just one way to communicate.
And when speech is not yet clear, not yet reliable, or not yet available, children need other ways to get their message across.
This is where Total Communication comes in.
What is Total Communication?
Total Communication is an approach that encourages the use of all available ways to communicate, not just speech.
This can include:
spoken words
gestures and pointing
facial expressions
signing (such as Makaton)
pictures or symbols
drawing
electronic AAC (Augmentative and Alternative Communication), such as apps like LAMP Words for Life
It’s not about replacing speech. It’s about supporting communication in every possible way.
Think of it like this: if speech is currently unclear or limited, why restrict a child to the hardest route? Why not give them more tools to succeed?
‘But won’t this stop my child from talking?’
This is one of the most common concerns I hear in clinic.
Parents often worry that if a child starts using signs or a communication device, they will become ‘dependent’ on it and stop trying to talk.
The research tells us something very different.
Studies consistently show that AAC does not prevent speech development. In fact, it often supports it.
A review by Millar, Light & Schlosser (2006) found that AAC interventions do not reduce speech production and may actually increase it.
Romski & Sevcik (2005) demonstrated that children given AAC often develop stronger overall communication skills, including spoken language.
More recent work continues to show that providing AAC early can accelerate language development, not delay it.
So rather than ‘giving up on speech’, using AAC is actually building the foundations that speech needs.
Why Total Communication matters, especially for unintelligible children
When a child is very difficult to understand, they are often experiencing a hidden frustration:
‘I know what I want to say, but no one understands me.’
Over time, this can lead to:
reduced confidence
behavioural frustration
withdrawal from communication
fewer opportunities to practise language
If a child cannot successfully communicate, they communicate less. And when they communicate less, their language development slows down.
Total Communication breaks this cycle.
By giving a child reliable ways to be understood, we:
reduce frustration
increase interaction
build confidence
create more opportunities for language learning
And importantly, we allow them to show us what they already know.
AAC is a bridge, not a barrier
Using AAC (whether that’s pointing to pictures, signing, or using a device) does something powerful:
It separates language from speech.
A child might have lots of ideas, vocabulary, and understanding but their speech system (especially in cases like phonological disorder or childhood apraxia of speech) cannot yet keep up.
AAC allows the child to:
express complex ideas now
practise sentence structure
develop vocabulary
take part in conversations
All while their speech is still developing.
In other words, AAC doesn’t replace speech. It keeps language moving forward while speech catches up.
What does this look like in real life?
In therapy, I often use a combination of approaches:
modelling simple signs alongside speech
pointing to symbols while talking
encouraging children to gesture or show
using drawings to support understanding
incorporating an AAC device such as LAMP Words for Life
You might see a child:
say part of a word
point to a symbol
use a gesture
and look at you expectantly
That is communication success.
And success builds motivation.
‘I just want them to talk’
Of course you do. And I do too!! That’s always the goal.
But here’s the important shift in thinking:
Children learn to talk by communicating, not by waiting until speech is perfect.
If we hold out for clear speech before allowing other communication methods, we risk:
limiting their ability to interact
reducing practice opportunities
increasing frustration
But if we support all communication, we give them:
more chances to express themselves
more positive communication experiences
more input and feedback
And that is what drives progress.
A balanced approach
Total Communication doesn’t mean ‘speech is no longer important’.
It means:
we continue targeted speech therapy
we work on sounds and clarity
and we support communication in the meantime
It’s not either/or.
It’s both/and.
Final thought
If your child’s speech is difficult to understand, the most important question is not:
‘Are they talking clearly yet?’
It’s:
‘Can they successfully communicate?’
Because communication is the foundation of:
relationships
learning
confidence
wellbeing
And every child deserves a voice, in whatever form that voice takes right now.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
If you were to peek through the window of one of my speech therapy sessions, you might notice two things: a room full of engaging games and activities, and a therapist who is carefully guiding a child towards a specific goal.
There will be laughter, encouragement and opportunities to play. But there will also be moments when I ask a child to stop, listen carefully, try a sound again or adjust the way they are producing it.
To an outside observer, this might sometimes look quite structured. And that raises an important question: does effective speech therapy need to be more than simply playing with a child?
My answer is yes.
Play has a valuable place in speech therapy, but when a child is working on a speech sound disorder, we also need clinical expertise, purposeful practice, careful listening and clear goals. Children deserve sessions that are enjoyable and supportive, while also helping them develop the skills they need to communicate more clearly and confidently.
For me, the key is combining warmth and encouragement with high expectations, appropriate structure and an approach tailored to each individual child.
Here is why I believe this balance matters.
1. Speech sound therapy involves learning a new skill
Learning to produce a speech sound accurately is not simply a matter of telling a child what to do. Speech involves highly coordinated movements, and children who have difficulty producing particular sounds may need considerable support to develop new or more consistent ways of producing them.
Think about learning to play a musical instrument. Understanding what a note should sound like is not the same as being able to play it accurately. It takes practice, feedback and time to develop the necessary skills.
Speech sound therapy can be similar. A child may understand that they need to make a /K/ sound, for example, but continue to produce a /T/ sound instead. They may need help to notice the difference, understand where the sound is produced in the mouth and practise the new movement with appropriate support.
This is where purposeful practice becomes important.
During a session, I listen closely to how a child produces a sound. I may model the sound, use a visual cue, help the child notice their tongue position or break the task into smaller, more manageable steps.
Sometimes a child can produce a sound accurately straight away. At other times, we need to slow down, change our approach or practise at an easier level before moving on.
The aim is not simply to produce lots of sounds. It is to help a child practise in a way that supports accurate, increasingly consistent speech.
That means I will sometimes ask a child to try again. Not because I expect perfection, but because I want to help them discover what works and build on their successes.
2. Clear structure can help children know what to expect
Some children arrive at therapy full of energy. Others may find it difficult to concentrate on a task, manage transitions or persist when something feels challenging.
Expecting every child to sit still and work in exactly the same way would not be realistic, nor would it be appropriate.
However, children often benefit from knowing what is happening, what we are working towards and what comes next.
For example, I might explain:
‘First, let’s practise five careful /S/ sounds together. Then we’ll take our turn in the game.’
This gives the child a clear, achievable goal and a predictable next step. For another child, I might use a visual timetable, shorter practice bursts, movement breaks or a more playful activity to support participation.
Structure does not mean that every session must look the same. It means that the activities have a purpose and that I am making thoughtful decisions about how best to help the child learn.
If a child becomes tired, frustrated or overwhelmed, I may need to adapt the task rather than simply insist that they continue. Sometimes a short break or a different approach is exactly what enables the child to return to the activity successfully.
My responsibility is to recognise what the child needs while keeping sight of the therapeutic goal.
3. Warmth and high expectations belong together
I believe one of the most important qualities of a good speech and language therapist is the ability to combine a positive relationship with clear clinical guidance.
Children need to feel safe enough to try something difficult, make mistakes and have another go. They also need a therapist who can recognise when they are ready for the next step and help them work towards it.
In my sessions, encouragement might sound like this:
‘That was a good try. Let’s see if we can make that sound even clearer together.’
‘I know this sound is tricky. Let’s slow it down and find the mouth position that works.’
‘You did that one really carefully! Can you remember what you did with your tongue?’
These are small moments, but they matter. They help children understand that speech sounds can take practice, that mistakes are part of learning and that they can make progress with the right support.
I celebrate genuine achievements, whether that means producing a difficult sound accurately for the first time, becoming more aware of how a sound feels, or managing to use a new skill more consistently.
I also want children to understand that they are not expected to get everything right immediately. My job is to guide them, give them appropriate feedback and help them develop their skills step by step.
High expectations should never mean expecting every child to progress at the same pace. They mean taking each child’s potential seriously and giving them the support they need to move forward.
4. Play can be powerful when it has a purpose
I love using games and playful activities in therapy. They can motivate children, create opportunities for interaction and make repeated practice much more enjoyable.
But the game itself is not the therapy. It is one of the ways I help a child engage with the therapeutic task.
For example, a simple board game might provide opportunities to practise a target sound in carefully chosen words. A picture activity might help a child listen for the difference between two sounds. A motivating toy might encourage a child to practise a word several times without the session feeling repetitive.
While the child is playing, I am listening, observing, adjusting the level of difficulty and deciding what support to offer next.
If a child is not yet able to produce a sound accurately in a particular word, I may return to an easier level of practice. If they are achieving the target consistently, I may begin to introduce more challenging words or activities that help them use the sound in a wider range of situations.
The activities may look simple, but the clinical reasoning behind them is important.
Parents should be able to understand what their child is working on, why a particular approach has been chosen and how progress is being monitored.
For me, effective therapy is about making the session purposeful, responsive and productive.
5. Progress takes clinical expertise, practice and partnership
When parents seek specialist speech and language therapy, they understandably want to see progress. They want their child to be understood more easily, to feel more confident communicating and to experience fewer frustrations when speaking.
My role is to assess the child’s speech carefully, identify the areas that need support and develop an appropriate plan.
Depending on the child’s needs, this may involve working on individual speech sounds, helping them distinguish between sounds, addressing patterns that affect several sounds, or using a more specialised approach where speech motor planning is a concern.
There is no single programme that suits every child. The type of intervention, the amount of practice and the pace of progress will depend on the child’s individual profile and response to therapy.
I monitor how a child is progressing and adjust my approach accordingly. I also explain what we are working towards and, where appropriate, suggest practical ways parents can support learning between sessions.
Home practice is particularly valuable, and it needs to be realistic and manageable for each family. Even a short period of well-supported practice provide useful opportunities to build on what a child has been learning in therapy.
Ultimately, I want parents to feel informed and involved, with a clear understanding of their child’s goals and the steps we are taking to work towards them.
The takeaway: Structure with warmth
I believe children deserve speech therapy that combines a warm, trusting relationship with skilled clinical intervention.
I will encourage a child, celebrate their achievements and make sessions enjoyable. I will also listen carefully, give feedback, revisit difficult sounds and help them work towards their goals.
Sometimes that means asking for another attempt. Sometimes it means changing the activity, taking a break or approaching the task in a completely different way.
The important thing is understanding when to encourage, when to challenge and when to adapt.
High expectations are not about making children comply. They are about believing in their capacity to learn while giving them the individual support they need to succeed.
For me, that is the balance at the heart of effective speech sound therapy: warmth, structure, clinical expertise and a genuine commitment to helping every child make meaningful progress.
Looking for specialist speech sound therapy?
If your child has difficulty producing particular speech sounds, is difficult to understand or is becoming frustrated when trying to communicate, an individual assessment can help clarify their needs and identify appropriate next steps.
At London Speech and Feeding, I provide tailored speech and language therapy with clear goals, careful clinical guidance and an approach that recognises each child as an individual.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
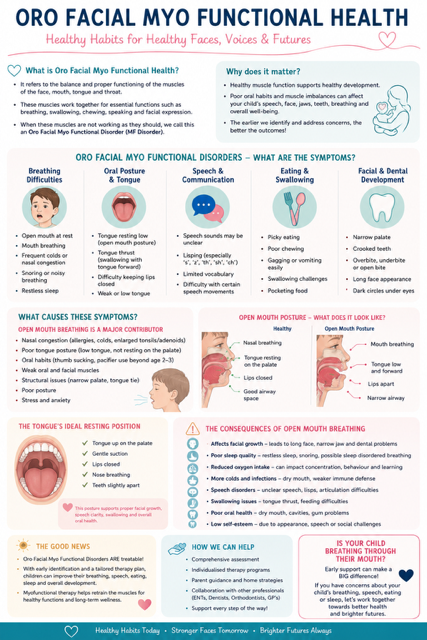
Many parents contact me at London Speech and Feeding because they are worried about their child’s speech. Perhaps their child is difficult to understand, has a persistent lisp, struggles with feeding, snores at night, or always seems to have their mouth open.
What many families don’t realise is that these concerns may all be connected.
Increasingly, research and clinical experience are highlighting the important role of Orofacial Myofunctional Health, the way the muscles of the face, mouth, tongue and airway work together to support breathing, eating, sleeping and communication.
When these muscles are not functioning optimally, children may develop what are known as Orofacial Myofunctional Disorders (OMDs).
What Is Orofacial Myofunctional Health?
Orofacial Myofunctional Health refers to the healthy function and coordination of the:
lips
tongue
jaw
cheeks
facial muscles
airway.
These structures play a vital role in:
breathing
swallowing
chewing
speaking
facial growth
dental development
sleep quality.
When everything is working well, the lips remain gently closed at rest, breathing occurs through the nose, and the tongue rests against the roof of the mouth.
This seemingly simple posture has a profound influence on how a child’s face, teeth and airway develop.
What is an Orofacial Myofunctional Disorder?
An Orofacial Myofunctional Disorder occurs when there is an abnormal pattern of muscle function involving the face, mouth, tongue or airway.
Children with OMDs may experience difficulties with:
speech
feeding
swallowing
sleep
breathing
dental development
facial growth.
In many cases, these difficulties are linked to chronic mouth breathing.
Signs your child may have an Orofacial Myofunctional Disorder
Breathing and sleep signs
mouth open at rest
mouth breathing during the day
snoring
noisy breathing
restless sleep
frequent waking
dark circles under the eyes
chronic congestion
fatigue despite a full night’s sleep.
Speech signs
lisping
unclear speech
distorted speech sounds
difficulty producing certain sounds
persistent articulation difficulties
reduced speech intelligibility.
Feeding and swallowing signs
picky eating
messy eating
food remaining in the cheeks
gagging easily
difficulty chewing
long mealtimes
tongue thrust swallowing.
Facial and dental signs
narrow palate
crowded teeth
open bite
overbite
underbite
long face appearance
receding chin
poor lip seal.
If several of these signs sound familiar, a comprehensive assessment may be worthwhile.
Why does mouth breathing matter?
Many parents assume mouth breathing is simply a habit.
In reality, mouth breathing is often a symptom that something is preventing efficient nasal breathing.
Common causes include:
enlarged tonsils
enlarged adenoids
allergies
chronic nasal congestion
recurrent infections
structural airway differences
tongue tie
prolonged dummy use
thumb sucking
poor oral posture.
When nasal breathing becomes difficult, children naturally begin breathing through their mouths.
Over time, this can affect how the face, jaws and airway develop.
What does healthy oral posture look like?
Healthy oral posture is surprisingly simple:
lips
gently closed
tongue
resting against the roof of the mouth
teeth
slightly apart
breathing
through the nose.
This posture helps guide healthy jaw growth, facial development and airway formation.
Think of the tongue as a natural orthodontic support system. When it rests in the correct position, it helps shape the upper jaw and supports healthy facial growth.
The consequences of chronic mouth breathing
1. Speech difficulties
Children who breathe through their mouths often have altered tongue posture and reduced oral stability.
This can contribute to:
lisping
distorted sounds
reduced speech clarity
difficulty learning new speech sounds.
2. Feeding and swallowing difficulties
A low tongue posture may affect:
chewing efficiency
swallowing patterns
food management
oral motor coordination.
Many children develop a tongue thrust swallow, where the tongue pushes forward instead of moving efficiently during swallowing.
3. Poor sleep quality
Mouth breathing can contribute to:
snoring
restless sleep
frequent waking
daytime fatigue
reduced concentration.
Poor sleep can have a significant impact on learning, behaviour and emotional regulation.
4. Changes to facial growth
Over time, chronic mouth breathing may influence:
jaw development
facial proportions
dental alignment
airway size.
This can result in:
narrow palates
crowded teeth
long facial appearance
increased orthodontic needs.
5. Oral health concerns
The nose acts as a natural filter and humidifier.
When children breathe through their mouths:
The mouth becomes dry.
Saliva protection is reduced.
Risk of tooth decay increases.
Gum health may be affected.
Why this matters for speech therapy
Speech does not develop in isolation.
The tongue, lips, jaw and airway work together to support clear communication.
At London Speech and Feeding, we look beyond speech sounds alone.
A child who presents with:
persistent speech difficulties
lisping
feeding challenges
open mouth posture
snoring
poor sleep
may benefit from an assessment that explores underlying orofacial myofunctional factors.
Addressing these foundations can often support more effective progress in speech and feeding therapy.
How London Speech and Feeding can help
A comprehensive assessment may include observation of:
breathing patterns
lip posture
tongue posture
swallowing function
feeding skills
speech sound development
sleep concerns
oral structures.
Where appropriate, recommendations may include:
orofacial myofunctional therapy
speech therapy
feeding therapy
home programmes
ENT referral
orthodontic referral
collaborative multidisciplinary support.
The good news
Orofacial Myofunctional Disorders are often highly treatable when identified early.
Supporting healthy breathing, tongue posture and oral muscle function can positively influence:
If your child regularly breathes through their mouth, snores, struggles with speech clarity or has feeding difficulties, a specialist assessment may help identify the underlying cause.
speech clarity
feeding skills
sleep quality
facial growth
dental development
overall wellbeing.
At London Speech and Feeding, we are passionate about looking beyond symptoms and understanding the whole child. Contact me!
Sometimes the key to clearer speech starts with a simple question:
‘Is my child breathing through their nose?’
Sonja McGeachie
Highly Specialist Speech and Language Therapist
Owner of The London Speech and Feeding Practice.
Frequently Asked Questions
Can mouth breathing cause speech problems?
Yes. Mouth breathing can alter tongue posture, lip strength and oral stability, which may contribute to articulation difficulties and lisps.
Should I be worried if my child snores?
Regular snoring is not considered normal in children and may indicate airway obstruction or sleep-disordered breathing.
Can enlarged tonsils affect speech?
Yes. Enlarged tonsils may affect resonance, tongue positioning, swallowing and breathing patterns.
What age can children be assessed?
Children of all ages can be assessed if parents have concerns about speech, feeding, breathing or oral development.
What is Orofacial Myofunctional Therapy?
Orofacial Myofunctional Therapy focuses on improving breathing patterns, tongue posture, lip seal and oral muscle function to support overall health and development.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
If you have ever wondered what happens when you bring your child to a speech and language therapy assessment, then this blog will shed light on the ins and outs of it for you.
At its heart, a speech and language therapy assessment is a systematic and thorough evaluation of your child’s communication or eating/swallowing abilities. It’s more than just asking a few questions. It is a carefully constructed process designed to identify strengths, pinpoint challenges, and ultimately pave the way for effective intervention.
Establishing a detailed profile – a few bullet points:
Identification of communication and swallowing difficulties: I aim to determine if a communication or swallowing disorder exists. I will establish if the difficulty is a delay or a more complex disorder.
Diagnosis of the specific disorder/autism: The assessment delves deeper to pinpoint the specific type and nature of the difficulty. For instance, is your child’s language delay due to a specific learning disability, a developmental delay, or another underlying condition?
Knowing the aetiology or what is causing a difficulty is crucial for targeted intervention. And whilst we are on the topic let’s talk about an autism assessment: I am trained and experienced in assessing and diagnosing autism. However, when it comes to the diagnosis of autism I provide a preliminary ‘working hypothesis’ rather than giving a definite final diagnosis. The reason for this is that it is considered the ‘gold standard’ and ‘best practice’ to diagnose autism in a multi-disciplinary setting and context. Since I work on my own, I always refer to highly recommended multi-disciplinary clinics for the ultimate diagnostic assessment.
Determination of severity: Understanding the severity of the difficulty is essential for prioritising intervention and measuring progress. Is your child’s difficulty mild, moderate, or severe? This helps me choose a particular approach and then tailor it to suit each individual child.
Identification of underlying strengths and weaknesses: An assessment doesn’t just focus on what’s wrong. It also highlights your child’s strengths and areas of relative ease. This information is invaluable for building upon existing skills during therapy. Understanding weaknesses provides specific targets for intervention.
Guiding intervention planning: The assessment provides the crucial information I need to develop an individualised intervention plan. The findings directly inform the selection of therapy goals, strategies, and techniques. Without a thorough assessment, therapy would be a shot in the dark.
A multi-faceted approach
A speech and language therapy assessment is not a ‘one-size-fits-all’ procedure. The specific tools and techniques used will vary depending on a child’s age, the nature of the suspected difficulty, and other relevant factors. However, most comprehensive assessments incorporate several key components:
Case history: This involves gathering information about your child’s developmental, medical, social, and educational background. We will go through all the relevant milestones and throughout the process I will make notes which will help bring all the puzzle pieces together.
Observation: I will observe how parent and child play together and we also look at how the child plays by themselves. Additionally of interest is how a child plays with me, the therapist. Through discussion I will also endeavour to find out how your child plays with other children, be it at the nursery or within the family.
Standardised assessments: These are commercially available tests with specific administration and scoring procedures. They provide norm-referenced data, allowing to compare the individual child’s performance to that of his or her peers. Examples include articulation tests, language comprehension and production tests, and fluency assessments. I tend not to use these assessments a lot.
Instead, I use non-standardised assessments: These are more flexible and allow to probe specific areas of concern in more detail. This might include language samples (analysing spontaneous speech), dynamic assessment (testing and teaching to identify learning potential), and informal observation of play or interaction.
Immediate feedback and report writing: During and thenfollowing the assessment, I will bring all the gathered information together and I will discuss with the parents what my findings are and what my recommendations in the short term are. Parents always go home with a good handful of useful strategies that they can implement at home right away. In addition, I provide a comprehensive report outlining the findings, diagnosis (if applicable), severity, strengths and weaknesses, and recommendations for intervention.
In conclusion, a speech and language therapy assessment is a dynamic and essential process. It is a journey of discovery, aiming to understand a child and the child’s family and his or her unique communication or feeding profile. The assessment is usually the start of our wonderful learning journey together.
Below is a short video clip of an assessment where you see me in action explaining a particular therapy approach to a set of parents. It perhaps shows a tiny bit of how relaxed we are in our sessions and that assessment is not at all daunting, but a hugely informative event overall which will leave you feeling empowered and hopeful.
What happens after an assessment?
Please feel free to get in touch with me via my contact form if you wish to have an assessment for your child’s communication difficulties or feeding difficulties.
An assessment is always a stand-alone event and does not mean you need to automatically book follow up sessions at all. It will give a lot of information and based on this you can decide if you would like more therapy or follow up for you and your child. Many times ongoing therapy is not needed! I only recommend a course of therapy if it is really needed and where it would be immediately beneficial for your child.
Sonja McGeachie
Highly Specialist Speech and Language Therapist
Owner of The London Speech and Feeding Practice.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.