The purpose and nature of a speech and language therapy assessment

| | |

If you have ever wondered what happens when you bring your child to a speech and language therapy assessment, then this blog will shed light on the ins and outs of it for you.

At its heart, a speech and language therapy assessment is a systematic and thorough evaluation of your child’s communication or eating/swallowing abilities. It’s more than just asking a few questions. It is a carefully constructed process designed to identify strengths, pinpoint challenges, and ultimately pave the way for effective intervention.

Establishing a detailed profile – a few bullet points:

  • Identification of communication and swallowing difficulties: I aim to determine if a communication or swallowing disorder exists. I will establish if the difficulty is a delay or a more complex disorder.
  • Diagnosis of the specific disorder/autism: The assessment delves deeper to pinpoint the specific type and nature of the difficulty. For instance, is your child’s language delay due to a specific learning disability, a developmental delay, or another underlying condition?
  • Knowing the aetiology or what is causing a difficulty is crucial for targeted intervention. And whilst we are on the topic let’s talk about an autism assessment: I am trained and experienced in assessing and diagnosing autism. However, when it comes to the diagnosis of autism I provide a preliminary ‘working hypothesis’ rather than giving a definite final diagnosis. The reason for this is that it is considered the ‘gold standard’ and ‘best practice’ to diagnose autism in a multi-disciplinary setting and context. Since I work on my own, I always refer to highly recommended multi-disciplinary clinics for the ultimate diagnostic assessment.
  • Determination of severity: Understanding the severity of the difficulty is essential for prioritising intervention and measuring progress. Is your child’s difficulty mild, moderate, or severe? This helps me choose a particular approach and then tailor it to suit each individual child.
  • Identification of underlying strengths and weaknesses: An assessment doesn’t just focus on what’s wrong. It also highlights your child’s strengths and areas of relative ease. This information is invaluable for building upon existing skills during therapy. Understanding weaknesses provides specific targets for intervention.
  • Guiding intervention planning: The assessment provides the crucial information I need to develop an individualised intervention plan. The findings directly inform the selection of therapy goals, strategies, and techniques. Without a thorough assessment, therapy would be a shot in the dark.

A multi-faceted approach

A speech and language therapy assessment is not a ‘one-size-fits-all’ procedure. The specific tools and techniques used will vary depending on a child’s age, the nature of the suspected difficulty, and other relevant factors. However, most comprehensive assessments incorporate several key components:

  • Case history: This involves gathering information about your child’s developmental, medical, social, and educational background. We will go through all the relevant milestones and throughout the process I will make notes which will help bring all the puzzle pieces together.
  • Observation: I will observe how parent and child play together and we also look at how the child plays by themselves. Additionally of interest is how a child plays with me, the therapist. Through discussion I will also endeavour to find out how your child plays with other children, be it at the nursery or within the family.
  • Standardised assessments: These are commercially available tests with specific administration and scoring procedures. They provide norm-referenced data, allowing to compare the individual child’s performance to that of his or her peers. Examples include articulation tests, language comprehension and production tests, and fluency assessments. I tend not to use these assessments a lot.
  • Instead, I use non-standardised assessments: These are more flexible and allow to probe specific areas of concern in more detail. This might include language samples (analysing spontaneous speech), dynamic assessment (testing and teaching to identify learning potential), and informal observation of play or interaction.
  • Immediate feedback and report writing: During and thenfollowing the assessment, I will bring all the gathered information together and I will discuss with the parents what my findings are and what my recommendations in the short term are. Parents always go home with a good handful of useful strategies that they can implement at home right away. In addition, I provide a comprehensive report outlining the findings, diagnosis (if applicable), severity, strengths and weaknesses, and recommendations for intervention.

In conclusion, a speech and language therapy assessment is a dynamic and essential process. It is a journey of discovery, aiming to understand a child and the child’s family and his or her unique communication or feeding profile. The assessment is usually the start of our wonderful learning journey together.

Below is a short video clip of an assessment where you see me in action explaining a particular therapy approach to a set of parents. It perhaps shows a tiny bit of how relaxed we are in our sessions and that assessment is not at all daunting, but a hugely informative event overall which will leave you feeling empowered and hopeful.

What happens after an assessment?

Please feel free to get in touch with me via my contact form if you wish to have an assessment for your child’s communication difficulties or feeding difficulties.

An assessment is always a stand-alone event and does not mean you need to automatically book follow up sessions at all. It will give a lot of information and based on this you can decide if you would like more therapy or follow up for you and your child. Many times ongoing therapy is not needed! I only recommend a course of therapy if it is really needed and where it would be immediately beneficial for your child.

Sonja McGeachie

Highly Specialist Speech and Language Therapist

Owner of The London Speech and Feeding Practice.


Health Professions Council registered
Royal College of Speech & Language Therapists Member
Member of ASLTIP

Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

1

Similar Posts

  • · ·

    Childhood Apraxia of Speech: Signs and first steps (2–5 years)

    If you’ve found yourself wondering ‘Why can my child say a word one day, but not at all the next?’ it might be that your child has a motor speech difficulty. This means the challenge isn’t that your child doesn’t know what they want to say; it’s that their brain finds it harder to plan and coordinate the movements needed for clear speech. This speech difficulty is called Childhood Apraxia of Speech (CAS)

    Sonja showing power words on a board

    In this post, I’ll explain what CAS can look like in 2–5 year olds, what an assessment usually involves, and what you can start doing at home to support your child without turning life into ‘speech homework all day long’.

    What is childhood apraxia of speech (CAS)?

    Children with CAS often have lots to communicate about (and strong ideas!) but their speech may come out as:

    • Unclear
    • inconsistent
    • hard to ‘copy’ on demand
    • frustrating for them and for you

    CAS is not caused by laziness and it is not a parenting issue. It is also not something children simply ‘grow out of’ without support. But with the right therapy approach, children can absolutely build clearer speech over time.

    If you’d like to read more about verbal dyspraxia, you may also find this helpful: Supporting children and families living with verbal dyspraxia.

    Why is CAS such a big topic right now?

    Many families come to me after months (or years) of being told:

    • ‘She’ll talk when she is ready’
    • ‘He’s just shy’
    • ‘It’s probably a speech delay’
    • ‘It’s normal for toddlers’

    And sometimes it is a general delay. But sometimes it’s something more specific, like CAS.

    There’s also been a huge rise in parents seeking information online, and CAS is often mentioned alongside speech sound difficulties such as:

    • phonological delay (pattern-based speech errors)
    • articulation difficulties (one sound that won’t come out clearly)
    • inconsistent speech disorder

    These can look similar at first glance, which is why a specialist assessment matters.

    Signs of childhood apraxia of speech in 2–5 year olds

    Children develop speech at different rates, and not every unclear speaker has CAS. But here are some common features that may raise a flag, especially when you notice several together.

    1) Inconsistent speech errors

    Your child might say the same word in different ways:

    • ‘banana’ → nana / baba / mana
    • ‘daddy’ → gaga / daddy / dadi

    This inconsistency is one of the biggest clues.

    2) Difficulty copying words on request

    Some children speak more easily in natural play, but when asked ‘Say ___’, they freeze or the word becomes much harder.

    3) Limited sound repertoire

    They may use only a small set of consonants (like /M/, /N/, /B/, /D/) and avoid others.

    4) Vowel distortions

    Many children with typical delays mainly struggle with consonants. But in CAS, vowels can also sound ‘off’ or change between attempts.

    5) Speech that sounds effortful

    You might notice your child:

    • pauses between sounds
    • tries multiple times
    • looks like they’re ‘searching’ for the right mouth movement

    6) Longer words are much harder

    ‘Car’ might be easier than ‘carry’, and ‘carry’ easier than ‘caterpillar’.

    7) Prosody differences (rhythm and stress)

    Some children with CAS sound a little unusual in their speech rhythm, stress, or intonation.

    8) Frustration or reduced confidence

    When a child is frequently misunderstood, they may:

    • talk less
    • use gestures more
    • become upset when asked to repeat themselves

    Important note: none of these signs alone prove CAS but they are a strong reason to seek a speech assessment rather than waiting.

    CAS vs phonological delay vs articulation difficulty (quick guide)

    These are some of the most common questions I hear.

    If it’s mainly an articulation difficulty…

    A child may consistently say one sound incorrectly (for example, ‘thun’ for ‘sun’- lisp- but everything else is developing well.

    If it’s mainly a phonological delay…

    You might notice clear patterns, like:

    • leaving off the ends of words (‘ca’ for ‘cat’)
    • swapping back sounds for front sounds (‘tar’ for ‘car’)

    Patterns are often consistent and respond well to phonology-based therapy.

    If it might be CAS…

    Speech often feels less predictable, harder to imitate, and more impacted by word length and complexity.

    If you’re unsure, that’s completely normal, and exactly why assessment matters.

    What happens in a CAS assessment?

    A high-quality speech assessment for possible CAS usually includes:

    1) Parent discussion and developmental history

    We talk about:

    • pregnancy and birth history (where relevant)
    • feeding history
    • early sounds and babbling
    • first words and how speech has progressed
    • family history of speech/language needs

    2) A speech sound assessment

    Your child might be shown pictures or play-based prompts so we can hear:

    • what sounds they can say
    • what they simplify
    • whether errors are consistent or inconsistent

    3) An oral-motor and movement check

    This isn’t about ‘strength’. It’s about coordination and planning. We look at how your child manages speech movements and transitions.

    4) Stimulability testing

    This means: how easily can your child learn a new sound or word with support?

    For CAS, we often explore how they respond to:

    • slowed-down speech
    • visual cues
    • rhythm/tapping
    • short, simple syllable shapes

    5) Functional communication and confidence

    We look at how speech impacts daily life:

    • being understood at nursery
    • joining in with peers
    • asking for help
    • managing emotions when misunderstood

    At the end, you should leave with:

    • a clear explanation of what we think is going on
    • a therapy plan
    • practical home strategies
    • realistic next steps

    What parents can do at home

    Here are CAS-friendly strategies you can start right away.

    1) Choose ‘power words’

    Pick 1–2 words that matter most in your child’s daily life, such as:

    • more
    • help
    • mummy
    • again
    • stop
    • open

    These words are motivating and functional.

    2) Keep it short and successful

    For many children with CAS, the goal is quality over quantity.

    Try five minutes a day rather than 30 minutes of struggle.

    3) Support speech with rhythm

    Some children benefit from:

    • tapping a beat on the table
    • clapping syllables
    • using a gentle ‘marching’ rhythm

    This can help the brain organise the sequence of movements.

    4) Celebrate approximations

    If your child says ‘moh’ for ‘more’, that’s communication!

    We want them to feel:

    • safe
    • understood
    • proud to try again

    Confidence is a key part of progress.

    A short parent story (anonymised)

    One mum said to me:

    ‘We kept being told to wait. But I could see my child understood everything; they just couldn’t get the words out. Once we had an assessment and a plan, it felt like we finally knew what to do. The biggest change was his confidence. He started trying more.’

    When should you seek support?

    You don’t need to wait until school.

    It’s worth getting an assessment if your child is:

    • hard to understand compared with peers
    • becoming frustrated or withdrawing from talking
    • inconsistent with words they used to say
    • struggling to imitate speech sounds
    • showing signs that match CAS

    Early support can reduce stress for the whole family and help your child feel successful in communication.

    Here’s how I can help:

    ✅ A detailed speech assessment (including whether CAS is likely)

    ✅ A clear therapy plan with realistic goals

    ✅ Practical home strategies you can use immediately

    ✅ Support for nurseries and schools (where needed)

    ✅ In-person sessions in North-West London and online options

    Book your consultation here.

    Final gentle reminder

    You are not overreacting. Trust your instincts.

    Your child is communicating the best way they can, and with the right support, speech can become easier, clearer, and more confident.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
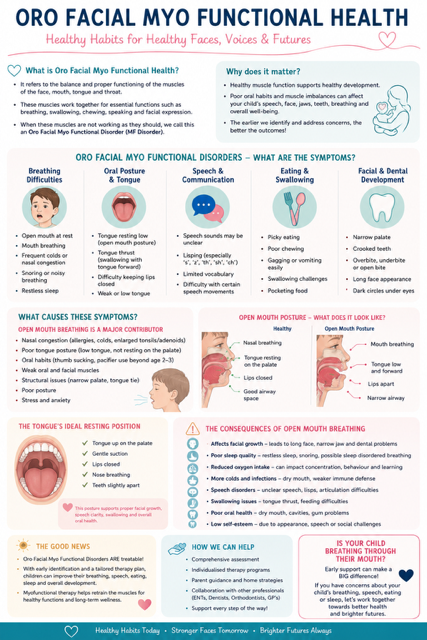
  • Could mouth breathing be affecting your child’s speech, sleep and development?

    Could mouth breathing be affecting your child's speech, sleep and development?

    Understanding Orofacial Myofunctional Disorders (OMDs)

    Many parents contact me at London Speech and Feeding because they are worried about their child’s speech. Perhaps their child is difficult to understand, has a persistent lisp, struggles with feeding, snores at night, or always seems to have their mouth open.

    What many families don’t realise is that these concerns may all be connected.

    Increasingly, research and clinical experience are highlighting the important role of Orofacial Myofunctional Health, the way the muscles of the face, mouth, tongue and airway work together to support breathing, eating, sleeping and communication.

    When these muscles are not functioning optimally, children may develop what are known as Orofacial Myofunctional Disorders (OMDs).

    What Is Orofacial Myofunctional Health?

    Orofacial Myofunctional Health refers to the healthy function and coordination of the:

    • lips
    • tongue
    • jaw
    • cheeks
    • facial muscles
    • airway.

    These structures play a vital role in:

    • breathing
    • swallowing
    • chewing
    • speaking
    • facial growth
    • dental development
    • sleep quality.

    When everything is working well, the lips remain gently closed at rest, breathing occurs through the nose, and the tongue rests against the roof of the mouth.

    This seemingly simple posture has a profound influence on how a child’s face, teeth and airway develop.

    What is an Orofacial Myofunctional Disorder?

    An Orofacial Myofunctional Disorder occurs when there is an abnormal pattern of muscle function involving the face, mouth, tongue or airway.

    Children with OMDs may experience difficulties with:

    • speech
    • feeding
    • swallowing
    • sleep
    • breathing
    • dental development
    • facial growth.

    In many cases, these difficulties are linked to chronic mouth breathing.

    Signs your child may have an Orofacial Myofunctional Disorder

    Breathing and sleep signs

    • mouth open at rest
    • mouth breathing during the day
    • snoring
    • noisy breathing
    • restless sleep
    • frequent waking
    • dark circles under the eyes
    • chronic congestion
    • fatigue despite a full night’s sleep.

    Speech signs

    • lisping
    • unclear speech
    • distorted speech sounds
    • difficulty producing certain sounds
    • persistent articulation difficulties
    • reduced speech intelligibility.

    Feeding and swallowing signs

    • picky eating
    • messy eating
    • food remaining in the cheeks
    • gagging easily
    • difficulty chewing
    • long mealtimes
    • tongue thrust swallowing.

    Facial and dental signs

    • narrow palate
    • crowded teeth
    • open bite
    • overbite
    • underbite
    • long face appearance
    • receding chin
    • poor lip seal.

    If several of these signs sound familiar, a comprehensive assessment may be worthwhile.

    Why does mouth breathing matter?

    Many parents assume mouth breathing is simply a habit.

    In reality, mouth breathing is often a symptom that something is preventing efficient nasal breathing.

    Common causes include:

    • enlarged tonsils
    • enlarged adenoids
    • allergies
    • chronic nasal congestion
    • recurrent infections
    • structural airway differences
    • tongue tie
    • prolonged dummy use
    • thumb sucking
    • poor oral posture.

    When nasal breathing becomes difficult, children naturally begin breathing through their mouths.

    Over time, this can affect how the face, jaws and airway develop.

    What does healthy oral posture look like?

    Healthy oral posture is surprisingly simple:

    • lips
      • gently closed
    • tongue
      • resting against the roof of the mouth
    • teeth
      • slightly apart
    • breathing
      • through the nose.

    This posture helps guide healthy jaw growth, facial development and airway formation.

    Think of the tongue as a natural orthodontic support system. When it rests in the correct position, it helps shape the upper jaw and supports healthy facial growth.

    The consequences of chronic mouth breathing

    1. Speech difficulties

    Children who breathe through their mouths often have altered tongue posture and reduced oral stability.

    This can contribute to:

    • lisping
    • distorted sounds
    • reduced speech clarity
    • difficulty learning new speech sounds.

    2. Feeding and swallowing difficulties

    A low tongue posture may affect:

    • chewing efficiency
    • swallowing patterns
    • food management
    • oral motor coordination.

    Many children develop a tongue thrust swallow, where the tongue pushes forward instead of moving efficiently during swallowing.

    3. Poor sleep quality

    Mouth breathing can contribute to:

    • snoring
    • restless sleep
    • frequent waking
    • daytime fatigue
    • reduced concentration.

    Poor sleep can have a significant impact on learning, behaviour and emotional regulation.

    4. Changes to facial growth

    Over time, chronic mouth breathing may influence:

    • jaw development
    • facial proportions
    • dental alignment
    • airway size.

    This can result in:

    • narrow palates
    • crowded teeth
    • long facial appearance
    • increased orthodontic needs.

    5. Oral health concerns

    The nose acts as a natural filter and humidifier.

    When children breathe through their mouths:

    • The mouth becomes dry.
    • Saliva protection is reduced.
    • Risk of tooth decay increases.
    • Gum health may be affected.

    Why this matters for speech therapy

    Speech does not develop in isolation.

    The tongue, lips, jaw and airway work together to support clear communication.

    At London Speech and Feeding, we look beyond speech sounds alone.

    A child who presents with:

    • persistent speech difficulties
    • lisping
    • feeding challenges
    • open mouth posture
    • snoring
    • poor sleep

    may benefit from an assessment that explores underlying orofacial myofunctional factors.

    Addressing these foundations can often support more effective progress in speech and feeding therapy.

    How London Speech and Feeding can help

    A comprehensive assessment may include observation of:

    • breathing patterns
    • lip posture
    • tongue posture
    • swallowing function
    • feeding skills
    • speech sound development
    • sleep concerns
    • oral structures.

    Where appropriate, recommendations may include:

    • orofacial myofunctional therapy
    • speech therapy
    • feeding therapy
    • home programmes
    • ENT referral
    • orthodontic referral
    • collaborative multidisciplinary support.

    The good news

    Orofacial Myofunctional Disorders are often highly treatable when identified early.

    Supporting healthy breathing, tongue posture and oral muscle function can positively influence:

    If your child regularly breathes through their mouth, snores, struggles with speech clarity or has feeding difficulties, a specialist assessment may help identify the underlying cause.

    • speech clarity
    • feeding skills
    • sleep quality
    • facial growth
    • dental development
    • overall wellbeing.

    At London Speech and Feeding, we are passionate about looking beyond symptoms and understanding the whole child. Contact me!

    Sometimes the key to clearer speech starts with a simple question:

    ‘Is my child breathing through their nose?’

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.

    Frequently Asked Questions

    Can mouth breathing cause speech problems?

    Yes. Mouth breathing can alter tongue posture, lip strength and oral stability, which may contribute to articulation difficulties and lisps.

    Should I be worried if my child snores?

    Regular snoring is not considered normal in children and may indicate airway obstruction or sleep-disordered breathing.

    Can enlarged tonsils affect speech?

    Yes. Enlarged tonsils may affect resonance, tongue positioning, swallowing and breathing patterns.

    What age can children be assessed?

    Children of all ages can be assessed if parents have concerns about speech, feeding, breathing or oral development.

    What is Orofacial Myofunctional Therapy?

    Orofacial Myofunctional Therapy focuses on improving breathing patterns, tongue posture, lip seal and oral muscle function to support overall health and development.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • · ·

    From ‘Nailed it!’ in therapy to ‘Whoops!’ at home: Why generalising speech sounds is tricky

    As a parent, you’ve likely experienced the triumphant feeling when your child, who’s been working so hard on his or her /S/ sound, produces it perfectly in a therapy session. He or she is rocking those ‘sun’ and ‘socks’ words, his or her lisp seemingly a distant memory. You leave feeling elated, confident that all that hard work is finally paying off.

    Then you get home. And within minutes, you hear it: ‘Thooper!’ instead of ‘Super!’ Or maybe the clear /R/ in ‘rabbit’ from therapy reverts to a ‘wabbit’ when his or she is playing with his or her toys. It’s frustrating, confusing, and can feel like you’re back to square one.

    So, what’s going on? Why is it so difficult for children to take those amazing skills learned in a focused therapy session and seamlessly apply them to their everyday conversations? You’re not alone in wondering this. It’s a common challenge in speech therapy and understanding the ‘why’ can help both parents and children navigate this crucial stage.

    The brain’s habits: Old pathways are strong pathways

    Think of your child’s brain as having established ‘pathways’ for how he or she produces certain sounds. If he or she has been lisping his or her /S/ sound for years, that neural pathway is deeply ingrained. It’s like a well-worn path through a field: easy to follow because it’s always been there.

    In therapy, we’re essentially trying to forge a new path. We’re teaching him or her a new, more accurate way to make the sound. This new path is initially faint, like a barely visible trail. It takes conscious effort and repeated practice to strengthen it. Outside of the structured therapy environment, his or her brain often defaults to the old, comfortable, and well-established pathway, even if it’s not the most accurate.

    The demands of daily conversation: A multitasking challenge

    Therapy sessions are designed to be focused and controlled. We isolate sounds, practice them in specific words, and provide immediate feedback. There are minimal distractions, and your child’s full attention is on his or her speech production.

    Now, consider daily conversation:

    • Speed: We speak much faster in natural conversation than we do during structured practice. There is less time to think about individual sounds.
    • Cognitive load: Children are simultaneously thinking about what they want to say, understanding what others are saying, processing social cues, and managing their emotions. Adding the conscious effort of producing a new speech sound correctly on top of all that is a huge cognitive demand.
    • Variety of contexts: In therapy, we might practise ‘sun’ and ‘socks’. In real life, the /S/ sound appears in countless words, in different positions within words, and alongside a vast array of other sounds. Each new word and phonetic context present a fresh challenge.
    • Lack of immediate feedback: In therapy, the speech therapist is right there to provide instant correction and reinforcement. In a playground, during a family dinner, or while playing with friends, that immediate, consistent feedback isn’t present.

    The role of automaticity: Making it second nature

    The ultimate goal of speech therapy isn’t just correct sound production; it’s automaticity. This means producing the sound correctly without having to consciously think about it. It’s like learning to ride a bike. Initially, every pedal stroke and steering adjustment is deliberate. Eventually, it becomes second nature.

    Generalisation is the process of moving from conscious, controlled production to unconscious, automatic production. This takes time, consistent practice, and exposure to a wide variety of real-life speaking situations.

    How can we help? Bridging the gap

    So, what can parents do to help their children bridge this gap between therapy success and everyday speech?

    1. Be patient and positive: This is a marathon, not a sprint. Celebrate the small victories and avoid getting discouraged by setbacks. Your positive reinforcement is crucial.
    2. Practise little and often: Instead of long, infrequent practice sessions, aim for short, consistent bursts throughout the day. ‘Sprinkle’ in opportunities to practise their target sounds in natural conversations.
    3. Create ‘sound awareness’ moments: Gently draw your child’s attention to his or her target sounds in everyday words. For example, if he or she is working on /R/, you might say, ‘Oh, you said ‘wabbit.’ Can you try to make your /RRR/ sound for ‘rabbit’?’
    4. Model correct production: Continue to model the correct production of their target sounds in your own speech.
    5. Collaborate with your speech therapist: Your therapist is your best resource! Ask them for specific strategies and activities you can do at home to support generalisation. They can also provide guidance on when and how to gently correct your child.

    Tips and tricks

    Below I have listed a few good tips and tricks that can help the transition from therapy room to daily life:

    Empowering your child as the ‘sound detective’:

    • ‘Secret sound listener’: Instead of you doing the correcting, make your child the detective. When you’re having a conversation, say ‘your /S/ sounds are sometimes a bit “slippery”’ (or whatever fun, non-judgmental term you like). Ask your child to quietly listen for your /S/ sounds. You can even purposely make a few ‘slippery’ ones (or correct yourself immediately after) and see if they notice. This shifts the focus from being corrected to actively listening and identifying the sound in a non-threatening way.
    • ‘Sound scorecard’: For a short period (maybe 10–15 minutes during a specific activity, like dinner or a game), provide a small notepad and pencil. Explain that your child is going to listen for his or her /S/ sounds and gently mark a tally every time he or she uses it correctly. The goal isn’t perfection, but awareness. This gives your child agency and a visual representation of progress. You can even make it a game: ‘Let’s see how many /S/ sounds we can catch in five minutes!’
    • /S/ sound song/rhyme creation: Work together to create silly songs or rhymes that are packed with /S/ sounds. The sillier, the better! You can sing them in the car, while doing chores, etc.
    • /S/ sound superpower: Frame the new sound skill as a ‘superpower’. ‘You’re getting so good at using your /S/ superpower! It’s going to help you speak so clearly and confidently.’
    • Highlighting successes: Always go out of your way to acknowledge and praise successful /S/ productions in natural conversation. ‘I really understood you clearly when you said ”s_top”.’ or ‘That /S/ sound was perfect when you told me about the “s_tory”!’

    Important considerations:

    • Keep it low-pressure: The goal is generalisation, not perfection. If your child is feeling pressured, he or she will likely revert to old patterns.
    • Focus on awareness, not just correction: Help your child become aware of his or her own speech rather than relying on you for corrections.
    • Short, frequent bursts: A few minutes of subtle focus multiple times a day is more effective than one long, forced session.
    • Acknowledge feelings: If your child expresses frustration about ‘being corrected’, validate these feelings. ‘I understand it can feel like a lot of listening, but we’re just trying to help you use that super /S/ sound all the time!’

    By incorporating these strategies, you can help your child naturally integrate the new /S/ sound into daily speech, fostering independence and confidence without it feeling like constant ‘testing’ or ‘correction’. Generalising new speech sounds is arguably the hardest part of speech therapy, but it’s also the most rewarding. With patience, consistent effort, and a collaborative approach between parents and therapists, children can successfully integrate their new, clearer speech sounds into every aspect of their daily lives.

    Any comments or if you need help and support with your child’s speech please do not hesitate to get in touch with me: simply fill out the contact form here on the website. I endeavour to reply within 48 hours.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • Empty Set and Phonology approaches

    I have been avoiding the use of the Empty Set approach for the longest time as I was not sure if it would work seeing that I am challenging two sounds my student struggles with at the same time. But I decided to give it a go and it works a treat!

    With this approach, we use two sounds that our student is struggling with. For example, in my video this student cannot produce /sh/ and /r/. Both sounds have different rules, so I decided to contrast them with each other.

    • The rules of /sh/ are: no voice, air is pushed out through teeth, produced at the front.
    • The rules for /r/ are: use your voice, produce the sound in the middle of the mouth by shaping your tongue in a particular way.

    So I chose the words ‘shoes’ and ‘ruse’ as their rules are quite different. Contrasting two sounds the student does not know has been shown to lead to greater change in the child’s articulation. And I can certainly vouch for this as my student is making the best progress with this approach.

    Phonology Therapy – what is it, why and how?

    Phonology is the study of the sound system of a language. It’s distinct from articulation therapy which focuses on the physical production of sounds.

    Phonology therapy focuses on rules. For example, sounds that are produced at the front of the mouth, in contrast to sounds that are produced at the back of the mouth, or sounds that are produced with a long air stream: /s/ or /f/ versus short sounds like /p/ or /t/; sounds are produced with voice or without voice.

    Many children, and sometimes adults, are unaware of some of the speech rules and confuse and replace individual sounds. They might say TAT instead of CAT or SIP instead of SHIP.

    A quick overview of phonology approaches I use:

    Minimal Pairs:

    This approach is good for single sound substitutions. We offer word pairs that differ by only one sound, like ‘ship’ and ‘sip.’ One of our first goal in therapy is to highlight the difference between the target sound (e.g., /sh/) and the sound the child uses (e.g., /s/). This helps discriminate and eventually produce the correct sound.

    Multiple Oppositions:

    A child might replace lots of sounds with a single sound like a /d/. So instead of ‘four’, ‘chore’ and ‘store’ our child says ‘door’, making speech very unintelligible.

    The approach is typically geared towards shaking up the phonological system. Our goal is to choose two to four targets that are different from each other, and different from the substituted sound. If our child’s favourite sound is /d/ they can use their voice and make a short sound by stopping their airflow. So I will choose a different target sound to change up the speech system. For example I might choose an /f/, a /m/ and a /k/ sound. So I would contrast: ‘door’ with ‘four’, ‘more’ and ‘core’.

    Maximal Oppositions:

    In the Maximal Oppositions approach the treatment sets consists of words that are minimally contrasted and that have maximal or near maximal feature differences between each word pair. One word in a pair represents a sound the child ‘knows’ (can say at word level) and the other represents a sound the child does not know (cannot say).

    For example, a child may ‘know’ /m/ and be able to say words like ‘man’, ‘mat’ and ‘mine’. However, the same child may be unable to say /f/ as in ‘fan’, ‘fat’ and ‘fine’. The consonants /f/ and /m/ are maximally opposed as follows.

    I am always delighted to work on speech sound disorders, I love the challenge and the successes we can celebrate together. Get in touch with me!

    Sonja McGeachie

    Early Intervention Speech and Language Therapist

    Feeding and Dysphagia (Swallowing) Specialist The London Speech and Feeding Practice

    The London Speech and Feeding Practice


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
    1
  • · ·

    When speech difficulties overlap: Helping children with phonological delay and childhood apraxia of speech

    One of the questions parents often ask is:

    ‘What kind of speech difficulty does my child have?’

    It’s a very understandable question. We often hear different terms such as phonological delay, articulation difficulties, or Childhood Apraxia of Speech (CAS), and it can be confusing.

    The reality is that many children don’t fit neatly into one single category.

    In fact, quite often I see children whose speech profile includes a mixture of difficulties. They might have some phonological patterns (where they substitute one sound for another) alongside challenges with motor speech planning, where coordinating the movements needed for speech is harder.

    When this happens, therapy needs to be flexible, responsive, and tailored to the child sitting in front of us.

    Example

    Recently I filmed a short clip from one of my therapy sessions which shows exactly how this works in practice.

    The child I was working with has difficulties with several speech sounds. Part of the challenge relates to a phonological pattern called fronting.

    Fronting is when sounds that should be made further back in the mouth (like /K/ or /G/) are produced further forward instead.

    At the same time, this child also shows signs of motor speech planning difficulty, which means the brain has to work harder to organise and sequence the movements of the tongue, lips and jaw for speech.

    This type of profile can sometimes overlap with characteristics seen in Childhood Apraxia of Speech (CAS).

    When difficulties overlap like this, therapy cannot rely on a single approach. Instead, it needs to draw on multiple evidence-based strategies.

    That is exactly what you see happening in the clip. We started out generalising the /K/ sound which until recently had been replaced by a /T/ sound. Whilst looking at a sound loaded picture of /K/ sounds we somehow got talking about a ‘dent’ (I don’t recall how we got there!) but the ‘dent’ was a ‘det’ and I decided to tackle this there and then because there are other great words that end in ‘nt’ like : ‘count’ ‘giant’ ‘point’ or ‘paint’.

    Using visual cues to support motor planning

    Speech is incredibly complex. For children with motor speech difficulties, the challenge is not only knowing what sound they want to say, but also how to move their mouth to produce it.

    This is where visual cues can be incredibly helpful.

    In the clip, you can see me using a whiteboard with pictures and simple visual prompts. These help to:

    • Focus attention on the target sound
    • Understand where the sound occurs in the word
    • Remember the sequence of sounds needed

    Visual supports can act almost like a map for the mouth, guiding children as they practise new speech movements.

    For children with motor planning difficulties, this type of cueing can make a huge difference.

    Why repetition of a single word (massed practice) is so important

    Another key feature you will notice in the clip is lots of repetition.

    This is very deliberate.

    When we are supporting children with motor speech challenges, the brain needs repeated opportunities to practise the correct movement patterns. Just like learning a musical instrument or a new sport, repetition helps the brain build stronger and more efficient pathways.

    In therapy we call this massed practice.

    Rather than saying a word only once or twice, we practise it many times in a structured way, helping the child stabilise the new speech pattern.

    But repetition alone is not enough. The child also needs to understand why the sound matters.

    Showing children that sounds change meaning

    This is where another powerful therapy approach comes in: minimal pairs.

    Minimal pairs are word pairs that differ by only one sound. For example:

    • debt
    • dent

    In the clip, I use these two words to help the child realise that the /N/ sound makes a meaningful difference.

    Without the /N/, the word becomes something else entirely.

    This approach helps children recognise that speech sounds are not random: they carry meaning. If a sound is missing or substituted, the message may change.

    Helping children notice these differences can be a very motivating moment in therapy. Suddenly the sound is no longer just an abstract exercise; it becomes part of real communication.

    Blending approaches for the best outcomes

    In this short therapy moment, I am combining:

    • Visual cueing

    • Motor speech practice

    • High repetition (massed practice)

    • Minimal pair contrasts

    • Listening and awareness of sound differences

    Each element supports a different part of the speech system.

    Some strategies help with motor planning, others support phonological awareness, and others build accuracy and consistency.

    Together they create a therapy session that is both structured and responsive.

    Every child’s speech journey is unique

    One of the most important things I want to convey is that speech development is not always straightforward.

    Two children may both struggle with speech sounds, yet the underlying reasons may be very different.

    This is why careful assessment is essential, and why therapy needs to stay flexible as we learn more about how a child’s speech system works.

    Sometimes a child needs more motor-based work.

    Sometimes the focus shifts towards phonological contrasts.

    Often, as in this example, the most effective therapy uses both.

    Small steps lead to big progress

    Every session helps us understand a little more about how a child’s speech system works and what support will help them move forward.

    And when the pieces start to come together, when a child realises that one tiny sound can change a whole word, that is when the real progress begins.

    If you are concerned about your child’s speech sounds, clarity of speech, or possible motor speech difficulties, early support can make a significant difference. A detailed assessment can help identify the nature of the difficulty and guide a therapy approach tailored to your child’s individual needs.

    Feel free to contact me on www.londonspeechandfeeding.co.uk

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    Reference

    McNeill, B. C., Gillon, G. T., & Dodd, B. (2009). Effectiveness of an integrated phonological awareness approach for children with childhood apraxia of speech (CAS). Child Language Teaching and Therapy, 25(3), 341-366.

    3
  • ·

    Target activities and games

    Target Activities and Games For Kids
    Target Activities and Games For Kids

    Target Activities and Games

    AMAZINGLY EASY Activities that we can do at home and in the clinic to help our children practise those targets!

    I bet you have wondered what amazing things are done by a therapist in the clinic that you could not possibly do at home…? Well, if so I am here to tell you that you will be absolutely fine with just a few select toys and games and you will be able to get those targets done in a jiffy!

    What we clinicians do very well and what you probably can’t do yourself is formulate and design the targets that are important for your child to practice. Once we have assessed or reviewed your child’s progress and needs we can then design the perfect next step of targets for you.

    So for example, we have decided your little one needs to be practicing their ‘r’ sounds at the beginning of short words. We decided that based on our clinical expertise and our assessment and we have already worked with your child and managed to get this tricky ‘r’ sound just about right on its own. Now we are ready for short word practice.

    It has been researched that in order for the brain pathways to re-shape or reform we need to get about 100 words in per day of our target sound. That sounds like quite a lot, right? But actually….. it’s not that bad. After all you only need to say 5-7 words about 20 times and hey presto that’s about 80-100 words.

    So here are some simple games I use in my clinic all the time and these games are easily available online or in your local toy shops and this is how to do them:

    Pop the Pirate

    Pop the Pirate, sooo good and popular:

    Lay out your target words which you will have been given by your speech therapist and put a few swords on each word.

    Each time your child picks up a sword they will need to say the target word 5 x, like:

    rip rip rip rip rip or run run run run run just like that in a row, bish bash bosh.

    Then they can stick the sword into the barrel. Onto the next sword which they can pick and then again

    race race race race race and stick in another sword

    So with this little lot I put out 5 target words and 3 swords on each.

    You will therefore get…… 15 words per picture, and that makes….75 words , there that is nearly all you need to do.

    If you then do another little game like this one:

    Magnetic board game

    This is a Magnetic Board game, and they are suddenly EVERYWHERE. But you could also just take a baking sheet and some fridge magnet you might have kicking about.

    Same principle as before, but now since this is your SECOND game of the day and you have already got 75 targets under your belt you only need to do one more round of 5 target words each:

    Each time your child picks up a magnet piece they will say the target word 5 more times:

    Ray ray ray ray ray and DONE you will now at the end of this short round have 105!! target words done with just two little fun games.

    How good is this? Your child won’t hardly notice that they are in fact doing their speech therapy homework.

    You’re welcome 🙂

    Get in touch if you would like me to help finding good targets for your child to work on. They can be speech and/or language targets with this game method.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.


