Angelman Syndrome (AS) is a complex neurological disorder that affects development. It’s caused by a missing or functionally incorrect gene (UBE3A) on chromosome 15. While AS is rare, understanding its characteristics is crucial for parents and caregivers.
What are the key characteristics of Angelman Syndrome?
Children with AS typically exhibit a range of unique characteristics, which can include:
Developmental delay: Significant delays in reaching developmental milestones, such as sitting, crawling, and walking.
Speech impairment: Limited or absent speech. Individuals with AS may use few or no words.
Movement and balance issues: Difficulties with coordination, balance, and movement, sometimes causing a jerky or unsteady gait.
Happy demeanour: Frequent smiling, laughter, and a generally happy, excitable personality.
Intellectual disability: Varying degrees of intellectual disability.
Seizures: Seizures are common and often begin in early childhood.
Sleep difficulties: Disrupted sleep patterns and difficulty falling asleep.
The role of Speech and Language Therapy
Speech development and social communication is significantly affected in Angelman Syndrome, and therefore, Speech and Language Therapy plays a vital role in helping individuals with AS to communicate. As Speech and Language Therapists (SLT) we can work with the child and family support any of the following:
Assess communication skills: We evaluate the child’s current communication abilities, including any vocalisations, gestures, or signs they may use. With younger children we do this through play and playful social games as well as observation of a child playing and interacting with their siblings or caregivers.
Develop alternative communication strategies: Since spoken language may be limited, SLTs can help the child learn other ways to communicate, such as nonverbal communication, e.g
Gestures: use of pointing, waving and miming certain activities.
More formal sign language: Teaching basic signs to express needs and wants.
Core boards: Using pictures and symbols to represent everyday common words, actions, and feelings.
Augmentative and Alternative Communication (AAC) devices: Providing electronic devices that can produce speech.
Encourage vocalisations: When words don’t readily develop, SLTs can encourage the child to make vocalisations and sounds, as these can be a form of communication.
Support language development: SLTs can work on understanding of language, even if expressive language is limited.
Educate and support families: SLTs provide families with strategies and techniques to support their child’s communication at home.
The importance of a multidisciplinary approach
Caring for a child with Angelman Syndrome requires a team effort. A multidisciplinary approach, involving various healthcare professionals, is essential to address the diverse needs of the individual. This team may include:
Paediatrician: Provides overall medical care and monitors the child’s health.
Physiotherapist: Helps with movement, balance, and coordination.
Occupational therapist: Works on daily living skills, such as feeding, dressing, and self-care.
Speech and Language Therapist: Addresses communication and language needs.
By working together, we can provide comprehensive care, address the unique challenges of Angelman Syndrome, and help the child reach their full potential.
Conclusion
Angelman Syndrome presents unique challenges and opportunities. With early diagnosis, appropriate interventions, and a strong multidisciplinary team, children with AS can make good progress and live fulfilling, joyful lives. As Speech Therapists we delight in supporting parents in their role in advocating for their child.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
The festive season is a wonderful time for many families, but for children with feeding challenges, sensory differences, or autism traits, December can feel overwhelming. Changes in routine, busier environments, travel, new foods, disrupted sleep, and well-meaning relatives giving ‘advice’ can all affect a child’s feeding, communication and overall regulation.
As a speech and language therapist specialising in Early Years, I see the same pattern each year: children often make progress during the term, only to struggle in late December when everything becomes unpredictable. The good news? With a bit of preparation, children can not only cope better, but they can actually make significant developmental gains during the holidays.
This blog will help you feel confident, supported and prepared for the transition from ‘festive mode’ to a smoother, regulated start in January.
1. Why routines matter so much. Especially now
Young children thrive on predictability. For neurodivergent children or those with sensory, feeding or communication needs, routine isn’t just helpful: it’s the backbone of emotional regulation.
In December, typical patterns change:
Mealtimes shift or become irregular
Bedtime slides
New foods appear
Loud social gatherings overwhelm
Travel disrupts naps and comfort routines
Therapies pause
Childcare closes
Any one of these can lead to feeding refusals, more meltdowns, increased stimming, reduced communication attempts or regression in speech sounds.
It’s simply the nervous system responding to too much change.
2. Protecting feeding progress during holiday mealtimes
My last blog and insta post have a nice social story on festive meals. They are often the trickiest part of the season for families I support. Children with sensory-based feeding challenges, or ARFID traits may find holiday foods completely unfamiliar and challenging.
What helps:
Offer one ‘safe food’ at every meal
Keep portion sizes tiny
Use the ‘buffet rule’
Rehearse tricky moments
3. Supporting communication when routines are disrupted
Holiday time actually offers more opportunities for communication, just in different ways.
Strategies:
Slow down and follow your child’s lead
Use everyday routines as language opportunities
Keep AAC going even if casually
4. Understanding holiday ‘regressions’ and know they’re temporary
This is almost always due to nervous system overload. Children don’t truly ‘lose’ skills; they temporarily prioritise regulation over learning.
5. A gentle January reset: How to start the New Year smoothly
Re-establish predictability early
Return to preferred foods
Book early support if needed
Focus on regulation first
Sonja McGeachie
Highly Specialist Speech and Language Therapist
Owner of The London Speech and Feeding Practice.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
Your Speech Therapist might have been advising you to introduce words to your child with the help of a CORE BOARD. What on earth is she talking about and why would we want to do this, I hear you think – and in fact this is what I get asked a lot, as I often do recommend using Core Boards.
Core boards belong to the category of Augmentative and Alternative Communication (AAC ) and they can be really useful for:
Children or adults who cannot speak at all or who are very hard to understand.
Children who are slow to speak and have difficulty expressing themselves verbally, due to genetic conditions as Down Syndrome, Verbal dyspraxia, Autism or any other learning difficulty that means a child is slow to develop speech.
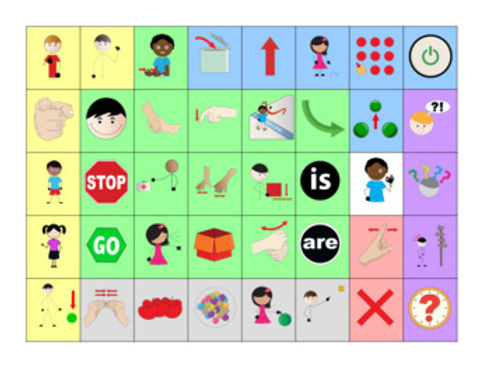
Here is what a Core board might look like, in fact this is one that I love to use. It is made by Beautiful Speech Life, there are a ton of similar boards out there for free. I have also made my own, you can check it out on my Instagram feed.
What is Core Vocabulary/ Core words?
Core vocabulary consists of the most common words used by children throughout a day. In 2003 Banajee and Dicarlo et al found that 50 % of pre-schoolers in their project used nine words consistently across their daily play and meal routines. These words are Core words and are typically the ones you can see on a board, like the one above.
How To Use It
Adults always first need to consistently model and show their child how to use a board. This is key! For example: Adult can point to “YOU” “WANT” ‘MORE” and then point to the cup of Water on the counter. Child could then reply either by shaking his/her head and/or pointing to “NOT” which also stands for “NO”. Then adult can point to “NOT” “MORE” and do an OK sign as well. Eventually Child can initiate a request and point to “I” “ WANT” “MORE” and then point to the cup on the counter.
This is not as cumbersome or limited as it first sounds or appears. Here’s why: As adult you can talk normally and, of course, many words you are using will not be on this board. But some will be, and you will be surprised how many you can find when you start using it. So you could say quite normally: Hey lovely (name of your child) would YOU LIKE some MORE water? The words in capital are on the board which you can point to as you speak normally. Basically, you are showing/saying to your child: “We can speak and these are the pictures we can use to help us; We call this TOTAL COMMUNICATION, as communication is so much more than just words! Great communication can be silent, where we use our facial expression, our smile, our eyes, our hand gestures, body movements and yes, of course, words. But when words fail us, these boards are so helpful.
This still does not answer your original question of: why would I want to do this, I want my child to talk!? You are a SPEECH Therapist, please help my child TALK, not point to pictures, that is not what I had in mind.
Let Me Explain
When speech is difficult for a child it doesn’t mean that there is nothing to talk about! Of course, we want all our children and all people to speak because it is the easiest and most effective way of communicating, no doubt! However, sometimes this is very hard for some children and whilst we are always working towards speech where possible, we also want to make sure that whilst figuring out how to speak, your child has a MEANS TO COMMUNICATE. Using a board like this might well be a temporary strategy but whilst you are using it and working on their speech you will find a reduction in tantrums and frustration as you child is able to express themselves more effectively.
Often we find that as soon as we offer a CORE VOCABULARY like the above sample a child who has had no or very few words suddenly blossoms and starts to point to new words on the board and starts to PRACTICE USING THESE WORDS!! Practice makes perfect, right? Yes it totally does! There is lots of evidence that tells us that using Core Vocabulary Boards ENHANCE AND SUPPORT SPEECH PRODUCTION AND NOT HINDER IT. Using a board like this will only ever be helpful to your child and will never make your child “lazy” – too lazy to speak? NO SUCH THING!
Here is what one of my parents says about the core board we use with her little boy:
“the board has been a game changer, my son is a visual learner so it really helps to have the board as he associates communication so much easier this way. We have incorporated his twin sister who models it’s use and have definitely seen improvement in speech through its support and his frustration around being unable to verbally communicate at times has definitely lessened”
K Connolly, Mother of Tom (aged 3.5 years).
Reading and hearing this makes me so happy!
In addition to general core board above I also sometimes use a Core Board that is specific to an activity, such as for example BLOWING BUBBLES. Below is an example of such a board, which you can use very nicely during a bubble blowing activity and sometimes it is a nice place to start for newcomers, this can be an easy introduction. You can download this and many similar boards on www.widgit.com for free!
There is so much more to say about AAC and using Coreboards, visit my Instagram you can find a bit more information on how I use them.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
Have you ever been told that if your child’s lisp or /R/ sound isn’t improving after months of speech therapy, you should see a myofunctional therapist?
The short answer is: possibly, but not automatically. Whether it will help depends on what is behind your child’s difficulty, and finding that out is exactly what a thorough assessment is for.
I’m a Speech and Language Therapist with nearly 30 years’ experience in speech sound disorders, feeding and swallowing, and I have additional training in myofunctional therapy. Looking at how the mouth works has been an intrinsic part of my assessments for many years, so I’d like to explain what that involves and when it matters.
What is myofunctional therapy?
Myofunctional therapy (often called orofacial myofunctional therapy, or OMT) is about how the muscles of the mouth and face work. It overlaps with what speech and feeding therapists call oro-motor function, although OMT looks more specifically at things like resting posture, breathing and swallowing patterns. Depending on the therapist’s training and your child’s needs, it may include:
tongue movement, resting posture and positioning
lip closure and resting posture
jaw movement and coordination
oral habits, such as thumb sucking or dummy use
swallowing patterns
how oral function, feeding and speech affect one another.
Some children have difficulties across several of these areas. Others have one specific speech sound difficulty and no wider problem with how their mouth works.
Signs it may be worth having your child’s oral function checked
You might want an assessment if your child:
has a lisp or a tricky /R/ that hasn’t changed with therapy
often has their mouth hanging open at rest
pushes their tongue forward against or between their teeth when speaking or swallowing (sometimes called tongue thrust)
is still dribbling or drooling after 18 months
finds chewing difficult, or struggles to move their tongue up, out or from side to side
breathes mostly through their mouth.
If you are worried about tongue-tie, I can assess how your child’s tongue moves for speech and feeding. If a medical or dental opinion is needed, I will explain why, advise you on who to see and work alongside them, for example an ENT consultant or paediatric dentist.
What does a comprehensive assessment look at?
When a child has a speech sound difficulty, I look at their speech alongside how their mouth is built and how it works. Depending on the concern, that may include:
jaw: how steady it is, and how well it moves and coordinates with the lips and tongue
teeth and mouth structure: the position of the teeth, the bite, the palate and anything structural that may be relevant
lips: closure, movement and resting posture
tongue: how well it moves in different directions, where it rests and whether it pushes forward
swallowing: relevant aspects of how your child swallows and where the tongue sits
palate and voice: anything that may need further investigation, such as concerns about how the palate is working or an unusually nasal sound
habits and breathing: things like thumb sucking or mouth breathing, and any signs that a medical or dental check may be needed.
Not every child needs every part of this. The questions we are trying to answer guide what I look at and what happens next.
For example, a child with a lisp may find it hard to coordinate the tongue placement needed for an /S/ sound. They may rest their tongue low in the mouth, or they may have spent years making the /S/ sound with the tongue between the teeth. By looking at how the mouth moves, along with habits and history such as thumb sucking, I can understand what may be contributing and plan therapy accordingly.
The findings help decide whether your child needs direct speech therapy, further assessment, a different approach, or input from another professional such as an ENT consultant, dentist or orthodontist. Assessment isn’t simply about spotting something that looks unusual. It is about understanding what it means for your child and deciding what, if anything, needs to be done. This kind of clinical reasoning is a natural, daily part of my work as a Speech and Language Therapist.
What if my child isn’t making progress in speech therapy?
If your child has been attending therapy for weeks or months without meaningful progress, it is reasonable to ask for a review. In my practice I monitor progress from one session to the next, and if things aren’t moving, I would rather review the plan than simply carry on with the same approach.
Sometimes a child needs more time. Sometimes the approach needs to change. Sometimes we need more information or another professional’s input. Sometimes therapy needs to pause while an underlying issue is looked into.
Whichever it is, you can expect a clear explanation of what we are working towards and how progress will be reviewed. A lack of progress should always prompt a review of the plan.
Does myofunctional therapy help with speech difficulties?
Sometimes. Some children have speech sound difficulties alongside differences in how their mouth works, which is why I assess both and consider whether they are related. A different tongue posture, an open-mouth resting posture or an unusual swallowing pattern is always worth noting, but it is not automatically the cause of a lisp or another speech sound disorder.
For speech sound disorders, treatment should be chosen to match the nature of the speech difficulty and be supported by evidence. The routine use of non-speech oral-motor exercises, meaning exercises that don’t involve practising speech sounds, to improve speech is not supported by the available evidence (the Cochrane review of non-speech oral-motor treatment – Lee & Gibbon, 2015).
That doesn’t mean work on oral function is never appropriate. The important question is what we are trying to achieve. If the aim is clearer speech, therapy needs to work on the speech itself, with plenty of practice of the relevant sounds, syllables and words. If your child also has a separate difficulty with feeding, swallowing or another aspect of oral function, such as resting posture, that may need its own assessment and targeted therapy. This is why I combine evidence-based speech practice with myofunctional assessment and therapy where a child’s oral function needs it, and I will always explain the aim and the reasoning behind what I recommend.
Choosing the right therapist for your child
Whoever you choose, I would encourage you to ask who will be treating your child, what their training covers and whether they are well placed to meet your child’s particular needs. Good clinical practice includes recognising the limits of your own expertise and referring on or working with others when appropriate. No practitioner should feel they have to manage every part of a child’s difficulties alone.
When the main concern is your child’s speech sounds, speech clarity or expressive language, I would recommend starting with an experienced Speech and Language Therapist whose expertise matches your child’s needs. If that therapist also has additional training in myofunctional therapy, so much the better. You can check that any Speech and Language Therapist is registered using the HCPC online register, and it is always fine to ask about a practitioner’s original qualification, clinical experience and the scope of their training.
So that you know who would be working with your child, here is a little about my own training: I am an HCPC-registered Speech and Language Therapist (BSc Clinical Communication Sciences, Royal Central School of Speech and Drama, 1996) with nearly 30 years’ experience, a postgraduate diploma in dysphagia (2000) and certification in the SOS Approach to Feeding (2018) and Orofacial Myofunctional Disorders training in 2026. I also completed IBCLC lactation consultant certification in 2019 (since lapsed, 2024) and worked as a neonatal Speech and Language Therapist and Lactation Consultant at Barnet Hospital in 2019–2020.
Next steps
If your child has a lisp, a tricky /R/, an open-mouth resting posture, a tongue thrust, dribbling or difficulty chewing, I would be happy to look at the whole picture. I assess speech and oral function together, and if your child needs a dentist, orthodontist or ENT consultant, I will tell you.
You can find out more on my Speech and Feeding Difficulties page, or get in touch to arrange an assessment. If you’re not sure whether your child needs one, contact me and we can talk it through.
Sonja McGeachie
Highly Specialist Speech and Language Therapist
Owner of The London Speech and Feeding Practice.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
Reference
Lee AS-Y, Gibbon FE. Non-speech oral motor treatment for children with developmental speech sound disorders. Cochrane Database of Systematic Reviews 2015, Issue 3. Art. No.: CD009383. DOI: 10.1002/14651858.CD009383.pub2.
Book corner with Oi Frog! by Kes Gray and Jim Field.
Books are an engaging way to support your child’s communication development. Even if your little one dislikes reading in the traditional sense. They will become immersed in this adventure, without realising they are taking in language and developing vital communication skills. This is one of my favourite series for children.
Increase fun and interaction
These books are made for fun and excitement! It may seem silly putting on different voices for different characters, but this is one way in which you can engage your child. Why not try to use different intonation patterns (e.g., you may use a deep voice for the dog, and a higher pitch for the cat)? Make your story interactive: you could ‘rawww’ like a lion and see who can make the loudest noise. Make noises to encourage interaction (e.g., when scratching his chin, make a squeaky sound!). You could also relate the experience back to your child (e.g., ‘can you scratch your chin?’).
Time to talk
Talk about what you can see on the front cover (e.g., There’s a frog on a log, how funny!) You could also ask your child to choose the rhyming words on a page in the book. Can your child tell you what rhymes with certain words (e.g., can you guess what a parrot sits on?)? Make use of every page. You could comment on your favourite frog and see if your child can talk about their favourite. You can support them by giving them an example (“my favourite frog is the one swimming backwards because he looks funny”). Then you could use this scaffold to support their answer. Your favourite is [________________] because [_________________]
If your child is reluctant to use language, the use of commenting can take the pressure of them (“look at all those frogs” or “he’s climbing up the stool”) is a powerful way in which you (as parents) can take the pressure off your child. A top tip I like to give is to make sure you pause regularly, which creates opportunities for your child to use language.
This book uses a subject-verb-object sentence structure (e.g., ‘hares sit on chairs’) which allows your child to hear a good model of a sentence. You could also talk about things in the book that belong in a certain category (e.g., animals, food) or begin with a specific sound. See if your child will name any more.
Reap the reward of repetitive language
Oi Frog uses repetitive rhyming language and puts emphasis on these words. This is important because the more your child hears a word, the more likely they are to remember, understand and use it in the correct context.
Emotions matter
Talk about how the animals feel and why they may feel this emotion (e.g., the cat’s feeling annoyed because…, Lions sit on irons, how does the lion feel?). Reasons can be difficult for children with communication difficulties. Support them by giving an example or by giving them an option (e.g., “does the lion feel happy or sad? I think the lion feels sad because he’s burnt his bottom on the iron! It’s too hot!”)
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
A submucous cleft palate (SMCP) is much less obvious than its counterparts, cleft of lip and/or palate, and can profoundly impact a child’s speech development. It leads to often extreme hyper nasal speech and difficulty with producing many sounds (/K/ /G/ /T/ /D/ /P/ /B/ /S/ /Z/ /F/ /V/).
In short, the muscles and bone of the soft palate, and sometimes the hard palate, do not fuse completely during foetal development and the mucous membrane that lines the roof of the mouth remains intact, effectively camouflaging the underlying muscular and bony deficit.
So, while the surface of the palate appears normal, the essential muscle and functions responsible for sealing off the nasal cavity from the oral cavity during speech are compromised. This cleft (or lack of muscle) can be seen as a bluish midline discoloration of the soft palate, often a bifid (split) uvula, and at times a notch in the posterior border of the hard palate can be felt upon palpation. However, these signs aren’t always present or easily discernible, contributing to the difficulty arriving at a diagnosis.
Diagnosing a submucous cleft palate is often akin to searching for a needle in a haystack, especially for the untrained eye. Unlike overt clefts that are visually apparent at birth, an SMCP can go undiagnosed for years, sometimes well into childhood or even adolescence. Paediatricians and even ENT surgeons have been known to miss it during routine checks due to the intact mucosal lining. Parents might notice their child’s speech sounds ‘different’ or ‘nasal’ but struggle to pinpoint the cause. Children might undergo extensive speech therapy without a proper diagnosis, as the underlying structural issue continues to hinder progress.
My experience as a speech therapist in private practice:
Over my years of practice, I have encountered several children presenting with persistent hyper-nasal speech and significant difficulties producing plosive and fricative sounds.
It has been incredibly rewarding, though at times challenging, to successfully diagnose SMCP in a number of these children. My approach often involves:
a meticulous oral motor examination,
careful listening for the specific qualities of hypernasality,
and a deep understanding of the physiological requirements for clear speech sound production.
When I suspect an SMCP, I refer these children to Great Ormond Street Hospital where a fantastic multidisciplinary team, typically including ENT surgeons and a specialist speech-language therapist can conduct more definitive assessments. These assessments often involve instrumental analyses such as videofluoroscopy or nasoendoscopy, which provide objective measures of velopharyngeal function and visual confirmation of the anatomical deficit.
The path to resolution: surgery, therapy, and successful outcomes
Surgery
The journey for these children, once diagnosed, often involves surgical intervention. It’s not uncommon for children with SMCP to undergo multiple operations to achieve optimal velopharyngeal closure. These procedures aim to reconstruct or augment the velopharyngeal mechanism, enabling it to effectively separate the oral and nasal cavities during speech. The specific surgical approach depends on the individual child’s anatomy and the severity of the velopharyngeal insufficiency. It’s a testament to the skill of these specialised surgeons that such intricate repairs can be performed with remarkable success.
Speech therapy
Following surgery these children embark on the crucial phase of speech therapy. While surgery addresses the structural problem, speech therapy helps a child learn to utilise their newly improved anatomy. It involves intensive work on developing oral airflow, establishing correct articulatory placement, and reducing learned compensatory strategies that have developed due to the original structural deficit. It is immensely gratifying to witness the transformation. Children who once struggled to produce basic sounds, whose speech was difficult to understand, gradually develop clear speech.
Next steps?
If you’re a parent concerned about your child’s speech and feeding, you’re not alone. The journey can feel confusing, but professional guidance can make all the difference. Never hesitate to have a second opinion when you have that niggling feeling that there is something that has not yet been explored. At London Speech and FeedingI specialise in being thorough and thinking outside the box.
I am here to provide the support you need. Reach out to schedule a consultation and take the first step towards helping your child communicate and thrive.
Sonja McGeachie
Highly Specialist Speech and Language Therapist
Owner of The London Speech and Feeding Practice.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
Imitation, the act of mirroring someone else’s actions, gestures, sounds, or words, is a fundamental skill that plays a crucial role in human development. It’s how babies learn to wave ‘bye-bye’, how toddlers pick up new words, and how children acquire social skills. But for children with autism imitation can be a significant challenge and understanding why it’s important and how to foster it becomes a key focus for parents, educators, and speech and language therapists.
Why is imitation important?
Imitation is a building block for a wide range of developmental skills:
Social interaction: Imitation is the foundation of social reciprocity. When a child imitates, he or she is engaging in a shared experience, connecting with another person, and learning to take turns in social exchanges.
Communication development: Imitation is closely linked to language acquisition. Children often imitate sounds and words before they can produce them independently. Imitation also helps them understand the meaning of gestures and facial expressions, which are vital for nonverbal communication.
Cognitive development: Imitation plays a role in problem-solving, learning new skills, and understanding cause and effect. By imitating actions, children explore their environment and learn how things work.
Emotional development: Imitation helps children understand and share emotions. When a child imitates a smile, he or she may begin to understand the feeling of happiness.
Imitation challenges in autism
Many children with autism face challenges with imitation, which can affect their development in these key areas. These challenges can manifest in different ways:
Difficulty imitating motor actions: Children with autism may struggle to imitate simple motor movements, such as clapping hands, waving, or playing ‘peek-a-boo’.
Limited vocal imitation: Imitating sounds, words, and phrases can be difficult for some children with autism, which can impact their speech development.
Challenges with social imitation: Imitating social cues, such as facial expressions, gestures, and body language, can be particularly challenging for children with autism, affecting their ability to engage in social interactions.
Why do children with autism struggle with imitation?
The exact reasons for imitation difficulties in autism are complex and not fully understood. However, several factors may contribute:
Neurological differences: Research suggests that differences in brain structure and function, particularly in areas involved in social perception and motor control, may play a role.
Sensory processing differences: Some children with autism may have sensory differences that make it difficult to attend to and process the movements or sounds they are expected to imitate.
Attention and motivation: Challenges with attention, focus, and social motivation can also affect a child’s ability to engage in imitation.
How to foster imitation in children with autism
Fortunately, imitation skills can be developed and improved through targeted interventions and strategies. Here are some approaches that I use in my practice as a speech and language therapist working with autistic children and their families:
Create a playful and engaging environment: Children are more likely to imitate when they are having fun and feel motivated. I use toys, games, and activities that the child enjoys.
Start with simple imitation: Begin by imitating simple motor movements that the child is already capable of and gradually introduce more complex actions.
Imitate the child first: As the Hanen Program emphasises, imitating the child’s actions, sounds, and words can encourage him or her to interact and communicate more.
Use visual supports: Visual aids, such as pictures, photos or videos, can help children with autism understand what is expected of them and make imitation easier.
Break down complex actions: Divide complex actions into smaller, more manageable steps. For example, to teach a child to brush their teeth, break it down into steps like ‘pick up toothbrush’, ‘put toothpaste on brush’, and ‘move brush on teeth’.
Reinforce imitation attempts: Provide positive reinforcement, such as praise, smiles, or preferred activities, when the child attempts to imitate, even if the imitation is not perfect.
Integrate imitation into daily routines: Incorporate imitation into everyday activities, such as imitating sounds during playtime, imitating gestures during songs, or imitating actions during self-care routines.
The role of speech therapy
Speech-language therapists play a crucial role in helping children with autism develop imitation skills, particularly in the areas of vocal and verbal imitation. As part of my therapeutic role, I offer the following:
Assessing a child’s imitation abilities.
Developing individualised therapy plans to target specific imitation goals.
Using a variety of techniques to encourage vocal imitation.
Working with parents and caregivers to provide strategies and support for promoting imitation at home.
Summary
Imitation is a fundamental skill that is essential for social, communication, cognitive, and emotional development. While children with autism may face challenges with imitation, it is a skill that can be developed and improved with targeted interventions and support. By understanding the importance of imitation and using effective strategies to foster it, parents, educators, and therapists can make a significant difference in the lives of children with autism, helping them to connect with others, learn new skills, and reach their full potential.
Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.