Rethinking the PECS Approach

|

I want to talk about some concerns of SLTs, parents and increasingly autistic adults who explain to us how this communication method did not really work so well and why.

What is PECS in a nutshell:

PECS (Picture Exchange Communication System) is based on the idea of exchanging pictures in return for desired items. For more advanced users, it is used to communicate different functions such as emotions, comments, negations using the exchange of a sentence strip. It was founded on the principles of Applied Behavioural Analysis (ABA).

How does that look in practice?

In my experience, having been trained in the approach myself, the overall aim is eventually for the child to spontaneously go and get their picture book (PECS book), open it, look through a range of pages to select the correct picture of what they want to have or say, then go and find their communication partner, and finally place that picture onto the communication partner’s outstretched palm to be rewarded with an item or with a response of some sort. Or the child selects a range of pictures to create a little sentence, such as: ‘the blue fish swims in the sea’, ‘the red bird flies in the sky’ or ‘I see a red bird’ for example. This can be part of a structured table top activity.

The system follows a series of phases, starting from simple picture exchanges to eventually construction of sentences using symbols. PECS’s aim is to promote communication initiation and reduce frustration for those who struggle with speech.

So far so good one might say, why not? Before I go into the various concerns, I would want to add my own working experience with PECS, and whilst it is my opinion, I would say I have NEVER seen a working PECS book being used spontaneously!

My experience

I have seen attempts of stages 1 and 2 done quite well, in schools, and where people knew that I was coming in “to have a look at how PECS is working with child X”. Yes, in those instances an effort was made of course to try and show me how it worked. I must add that have never been very impressed. I cannot recall it used for any other items than: biscuits/quavers/crisps/ raisins and bubbles/puzzle pieces or spinners.

If we want to see a child trained to exchange for these items in a structured setting, i.e., the child sits at a little table with the adult sitting opposite enticing the child with one or other item, then yes that can be done successfully. I have seen children exchange 25 pictures with a crisp on it, for said crisp and they might have asked for another 25 of those crisps given half the chance. Yes. Good. But. I have yet to see a child go to their PECS book and go through all the motions that I mentioned above to get a crisp. In school they don’t need to: they know that crisps are only available when the PECS book is being practised. Otherwise, let’s be honest, it’s fruit at 10.30 am!

So, they don’t get a spontaneous opportunity to ask for highly motivating items as that is not how school works, is it? ‘SIR! Can I have a crisp?’ At 10.02am, in the middle of maths? Didn’t think so… So in reality this does not get practised in my experience.

A few concerns in no particular order:

Limited Generalisation

One issue often raised is the limited generalisation of skills learned through PECS. The structured nature of the program may result in a child only being able to communicate effectively within the specific contexts where they were taught to use the system (as I suggest above: crisps: yes, please let’s do the PECS for it). This limitation can pose challenges when trying to apply communication skills in new or unstructured/spontaneous situations.

Lack of Spontaneity

Critics suggest that PECS can sometimes lead to scripted and less spontaneous communication. This is also what I have observed. Since the method is designed to follow a structured progression, there is a concern that individuals might struggle to initiate communication outside of the established framework, potentially hindering their ability to engage in more natural interactions.

Narrow range of communication functions being practised

While PECS is quite successful in focusing on requesting and naming items, there are many other important communication functions, such as expressing emotions, asking questions, giving opinions or greetings for instance. We can argue that a communication core board where we have a whole range of different core words available lends itself much better to practising a range of communicative functions.

The Pictures are movable

They are attached to the book via Velcro. They are constantly being picked and exchanged and then returned to the book. This means that the pictures tend to be always in different places. This goes against the motor planning that takes place when one is learning a new skill: imagine you want to learn to touch type and the letters always move and are at different places? How can you be quick about finding a letter? You can never get to “automatic” with this type of approach.

Communication is not taught via behavioural means

Only if you say “banana” in the way that I dictate that you should will you get a piece of banana. Who does that? Nobody. Typically, child points to the counter where there is a banana and says: ‘ba’ or ‘ana’ and mother/carer will look over there and say ‘oh banana! You want a banana? Ok there you go have a piece.’ Or something like it. Mother will not say: ‘SAY BANANA or else you won’t get it.’ Child hears mum saying ‘Banana’ each time and with time will point and say ‘banana’ or ‘I want-a-nana’ or something. This is how communication is learned: through the adult modelling it cheerfully all day long and the child hearing it and then gradually copying it.

One other gripe I personally have but I am reliably informed by all my parents that they share this about PECS:

IT IS SO LABOUR INTENSIVE!

There are 10, 50, 100’s of little pictures that first of all need laminating… then velcroing, then finding and replacing. As I said above, it’s a constant moveable feast for one, but also you LOSE them. Yep. You want to find the picture for “trampoline”. ‘Where is it? I saw it yesterday… We had it outside when we practised you asking for the trampoline. I am sure we put it back? Where is it??? Ok. We need to print off a new one.’

It is also labour intensive for the first stage where you need to have TWO adults to ease the exchange (pick up and release of picture into the communication partner’s hand). Who has two adults available for what can be weeks until the child is able to pick up and release by themselves?

YEP. So it’s really not for me you can tell! I much prefer Core boards (see my previous post on using one) or electronic speech generating AAC devices like GRID, or LAMP or TOUCHCHAT. These are all great to use and there is good support out there for introducing these.

Finding a Balance

While the concerns surrounding the PECS approach are valid, it’s fair to note that the method also has some merits. There is anecdotal evidence of many individuals who have successfully improved their communication skills and quality of life through PECS. But, finding a balance between using PECS as a stepping stone and ensuring the development of more comprehensive and SPONTANEOUS communication is key.

As educators and therapists, we need to extend the focus beyond requesting and labelling by incorporating symbols that represent emotions, actions, and more complex ideas. This expansion encourages a broader range of communication functions. When the time is right, gradually transitioning from PECS to more advanced communication methods such as Core boards or electronic AAC tools and speech-generating devices is the way forward.

We want to value all communication equally and our approach ought to be playful and child-led and to focus on intrinsic motivation instead of extrinsic rewards and reinforcers.

If you have any questions or if you are looking for a therapist who endorses play-based and child-led therapy approaches, please do reach out.


Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.


0

Similar Posts

  • · · ·

    Why open cup drinking and good sitting matter for your toddler

    When your baby reaches around 12 months, there is a lot going on developmentally. They are learning to walk, communicate, feed themselves and become increasingly independent. One small but important milestone that can sometimes get overlooked is learning to drink from an open cup.

    Many toddlers continue to have milk from a bottle well beyond their first birthday, and parents are often understandably reluctant to take it away. The bottle may be familiar, comforting and convenient, particularly at bedtime.

    But moving towards an open cup is not simply about changing the way your child drinks. It is part of their development of oral-motor skills, feeding independence and mealtime development.

    And there is another piece of the puzzle that is often overlooked: how your toddler is sitting while they eat and drink.

    The way the body is supported can make a real difference to what the mouth is able to do.

    Why introduce an open cup from around 12 months?

    Babies can begin learning to drink from an open cup much earlier than many parents realise. By around 12 months, most children should be given regular opportunities to practise drinking from an open cup alongside other suitable drinking vessels.

    An open cup encourages your toddler to learn a different pattern of drinking from the sucking pattern they have used with a bottle.

    With an open cup, your child needs to:

    • lean towards the cup and control its position
    • grade how much liquid enters the mouth
    • use their lips to help control the liquid
    • coordinate breathing and swallowing
    • develop increasingly mature tongue and jaw movements
    • learn to take a drink without relying on a teat or nipple.

    These are useful skills for developing efficient eating and drinking.

    This doesn’t mean that a toddler who still has a bottle at 14 or 18 months has somehow ‘missed their chance’. Children develop at different rates, and there is always an opportunity to work towards new skills.

    However, if a bottle remains the main or only way a child drinks for a long time, there can be fewer opportunities to practise these more mature drinking skills.

    What are the pitfalls of staying with a bottle for too long?

    The occasional bottle is not the issue. The concern is when a toddler continues to rely heavily on a bottle and therefore has little reason or opportunity to develop other drinking skills.

    A bottle encourages a sucking pattern which is appropriate for infancy. As children mature, we want to see increasing use of their lips, tongue, jaw and facial muscles in more sophisticated ways.

    Long-term bottle use can also make the transition to an open cup more difficult simply because the child has become very accustomed to the bottle.

    There can also be practical considerations around dental health, particularly when milk is offered frequently throughout the day or overnight.

    For many toddlers, the bottle has also become associated with comfort, sleep or emotional regulation. This can make giving it up feel like a very big change for the whole family.

    So rather than thinking, ‘The bottle has to disappear tomorrow’, think:

    ‘How can I gradually increase opportunities for open-cup drinking?’

    Offer the open cup regularly at meals. Let your toddler experiment. Expect spills. Keep the amount of liquid small initially and provide plenty of encouragement.

    Learning to drink is a skill. And skills need practice.

    But what has sitting got to do with drinking?

    Quite a lot!

    When we think about feeding, we naturally tend to focus on the mouth. We watch what the tongue is doing, whether a child chews, whether they cough or gag and what foods they accept.

    But feeding is a whole-body activity.

    Your child needs a stable body position before they can use their mouth efficiently.

    Think about trying to drink from a cup while sitting on a wobbly stool with your feet dangling in the air. You would probably find it much easier if your body was well supported.

    The same principle applies to toddlers.

    Tripp Trapp® Chair

    A well-designed highchair such as a Tripp Trapp chair can provide a stable base when it is correctly adjusted for the individual child. Ideally, your toddler should have:

    • hips well supported
    • knees comfortably bent
    • feet resting firmly on a footplate
    • a stable pelvis and trunk
    • the table or tray at an appropriate height

    This gives your child a solid foundation from which to move.

    And that matters because stability in the body supports movement and control in the mouth.

    Feet supported = better feeding?

    I sometimes hear parents say, ‘He doesn’t need the footrest don’t worry about it (as I crouch down with my Allenn key to adjust the Tripp Trapp chair) but I always explain it is very important to have his feet supported. Dangling legs can make it much harder to maintain a stable sitting position.

    When the feet are supported, your toddler can push gently through their feet and stabilise their pelvis and trunk. This can help them maintain a more organised position while eating and drinking.

    They can then devote more attention to the job in front of them:

    looking, reaching, grasping, chewing, swallowing and drinking.

    This is particularly important for toddlers who are developing their chewing skills or who find mealtimes physically demanding.

    A stable body supports a busy mouth

    Eating involves an extraordinary amount of coordination.

    Your toddler is managing food in their hands, bringing it to their mouth, biting, chewing, moving food around with their tongue, forming a bolus and swallowing,  often while simultaneously looking around, communicating and interacting with you.

    Drinking from an open cup adds another layer of coordination.

    Good postural support doesn’t teach a child to drink from a cup, but it can give them a much better physical foundation from which to practise the skill.

    This is why, when I assess a toddler’s feeding, I don’t just look inside the mouth.

    I also look at how the child is positioned.

    Making open-cup drinking part of everyday life

    You don’t need a complicated programme.

    At meals, offer a small amount of water in an open cup. You can help your toddler hold the cup initially, tipping it gently towards their lips and allowing them to control the drinking as much as possible.

    Some mess is completely normal!

    You might also use a small, lightweight open cup that is easy for little hands to manage.

    And remember that the goal is not to make every drink perfect. The goal is to give your child regular, positive opportunities to practise.

    If your toddler is struggling with drinking, frequently coughing or choking, refusing cups, relying heavily on a bottle, or experiencing difficulties with chewing and eating, it is worth seeking professional advice from a Speech and Language Therapist with expertise in paediatric feeding.

    The bigger picture

    Open-cup drinking and good sitting are not two unrelated developmental skills.

    They are part of the same picture.

    A stable body provides a foundation for skilled movement. Skilled movement supports feeding. And feeding skills develop through practice and opportunity.

    So as your toddler approaches and moves beyond their first birthday, think beyond simply asking, ‘How much milk are they drinking?’

    Think about how they are drinking, how they are sitting, and what opportunities they have to develop the skills they will need as they grow.

    And if you have a little one sitting beautifully at the table in a well-supported Tripp Trapp chair, remember: you’re not just creating a comfortable seat.

    You’re creating a stable foundation for eating, drinking, learning and growing.

    Do get in touch with me. I would love to hear from you and help your little one develop good sitting and drinking habits.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • Tele-Speechtherapy: Online, connected, and highly effective

    A different kind of therapy. Online, connected, and highly effective

    When parents first enquire about speech and language therapy, many assume it will happen face-to-face, in a clinic room, with a therapist sitting across from their child.

    So when therapy is offered online, it’s natural for questions to arise:

    Can this really work? Will my child engage? Will progress be slower?

    This short video offers a glimpse into what online therapy can look like: calm, interactive, relationship-based, and surprisingly effective.

    Online therapy is not ‘less than’ in the right circumstances

    Teletherapy is not suitable for every child in every situation. However, for many school-aged children, particularly those who enjoy conversation, technology, and shared activities, online therapy can be an excellent fit.

    The child you see in this video is around eight years old and was supported for a persistent lisp. Sessions were primarily online, with the occasional in-person appointment when helpful.

    What made the difference was not the screen. It was the combination of engagement, support, and consistency.

    Parent involvement changes everything

    One of the greatest strengths of online therapy is the way it naturally invites parents in.

    In this case, parents regularly joined the video sessions:

    • Listening in
    • Taking part when appropriate
    • Learning how to support practice gently between sessions

    This meant that therapy didn’t stay ‘on the screen’. Strategies carried over into everyday conversation, making progress faster and more meaningful.

    Speech sound therapy, including support for lisps, relies heavily on awareness, feedback, and confidence, all of which can be supported very effectively at home with the right guidance.

    Therapy through a screen can still be deeply relational

    A common concern is whether connection can truly be built online.

    In reality, many children feel more relaxed in their own home environment. They are often more willing to talk, experiment with sounds, and reflect on their speech when they feel comfortable and supported.

    Online sessions allow:

    • Shared focus and conversation
    • Clear visual feedback
    • Real-life practice in a familiar setting
    • Immediate parent support

    For some children, this actually enhances engagement rather than limits it.

    Real progress, real outcomes

    Over the course of approximately 12 online sessions, alongside a small number of in-person appointments, this child achieved resolution of their lisp.

    Progress was steady, positive, and confidence-building. Importantly, the child remained motivated and proud of their achievements throughout the process.

    While every child’s journey is different, this example highlights what is possible when:

    • The child is ready
    • Parents are involved
    • Therapy is tailored and collaborative

    If you’re considering online therapy

    If you’re unsure whether teletherapy could work for your child, it’s worth remembering that effective speech and language therapy is less about the room you’re in, and more about:

    • Relationship
    • Understanding
    • Consistency
    • Carryover into daily life

    For many families, online therapy offers flexibility, accessibility, and excellent outcomes especially when parents are active partners in the process.

    If you’re at the start of your child’s speech journey and wondering whether online therapy could be the right fit, I’m always happy to talk it through. Sometimes clarity begins with simply understanding what therapy can look like

    Teletherapy: Frequently Asked Questions

    Is online speech and language therapy really effective?

    Yes. For many children, particularly school-aged children, online therapy can be highly effective. Progress depends far more on engagement, consistency, and support than on physical location.

    What age does online therapy work best for?

    Teletherapy often works well for children from around six years and up, especially those who can attend to a screen, enjoy conversation, and follow simple instructions. That said, suitability is always considered individually and often a supportive adult is needed to help guide the child through the activities.

    Can speech sound work (such as a lisp) really be done online?

    Absolutely. Speech sound therapy relies on clear visual feedback, listening skills, and practice all of which can be supported very effectively online. Many children respond particularly well when practising in their own home environment.

    Do parents need to be involved in sessions?

    Parental involvement is strongly encouraged. Parents may sit in, join parts of the session, or support practice between appointments. This involvement often leads to quicker progress and better carryover into everyday speech.

    Will my child still build a relationship with the therapist?

    Yes. Strong therapeutic relationships can and do develop online. Many children feel more relaxed and confident communicating from home, which can actually enhance connection and learning.

    Is online therapy suitable for every child?

    Not in my experience. Some children benefit more from in-person support, or a combination of online and face-to-face sessions. A discussion and initial assessment help determine the best approach for each child.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • · ·

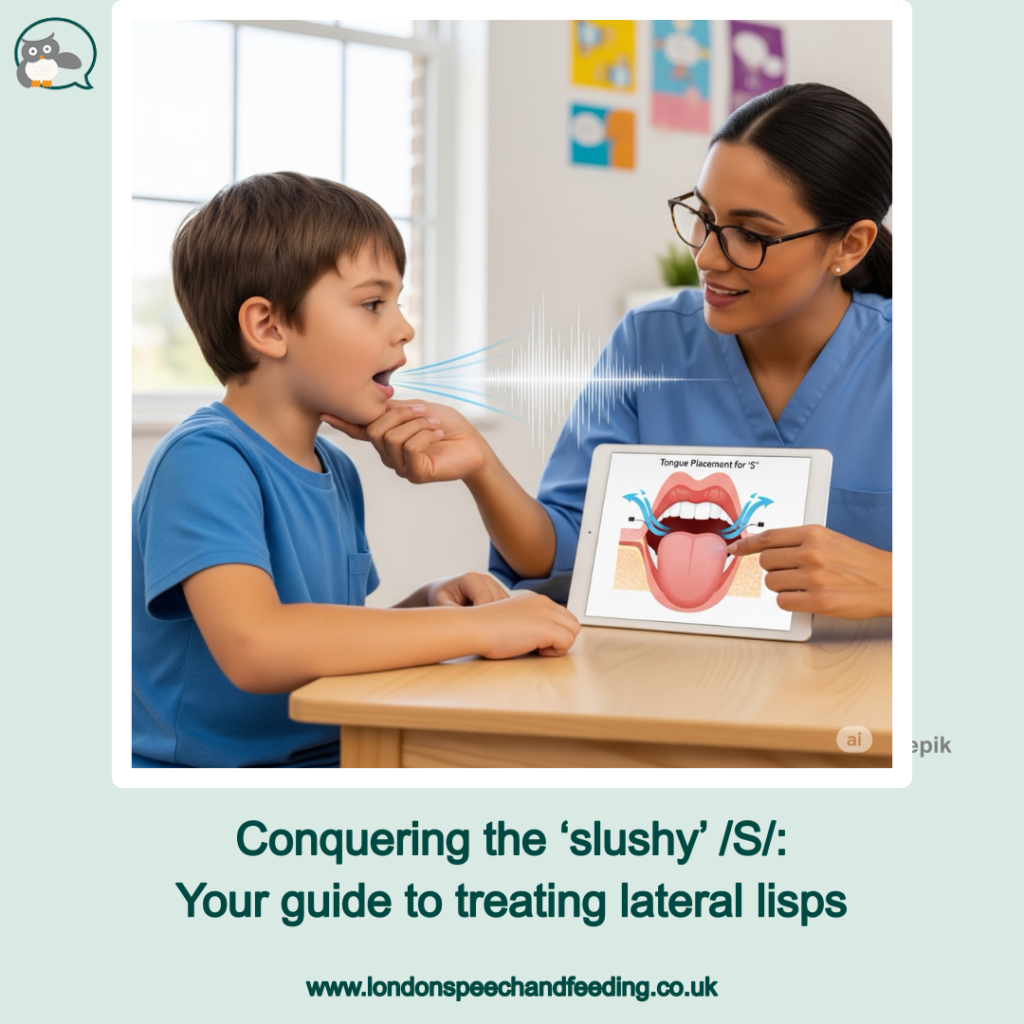
    Conquering the ‘slushy’ /S/: Your guide to treating lateral lisps

    Conquering the ‘slushy’ /S/: Your guide to treating lateral lisps

    As a speech therapist, few things are as rewarding as helping a child find their clear, confident voice. Among the various speech sound disorders, the ‘lateral lisp’ – often described as a ‘slushy’ or ‘wet’ /S/ sound – presents a unique challenge. While it can be tricky to treat, I’m thrilled to share that I’ve had significant success in helping children overcome this particular hurdle.

    What is a lateral lisp?

    Most people are familiar with a frontal lisp, where the tongue protrudes between the front teeth, resulting in a /TH/ sound for an /S/ (e.g., ‘thun’ for ‘sun’). A lateral lisp, however, is different. Instead of the air escaping over the front of the tongue, it escapes over the sides, often giving the /S/ and /Z/ sounds a distinct, muffled, or ‘slushy’ quality. This happens because the tongue is not forming the correct central groove, allowing air to spill out laterally.

    The science behind a perfect /S/ vs. a slushy one

    To understand how to fix a lateral lisp, it’s helpful to understand how a ‘perfect’ /S/ sound is made. Imagine a narrow, focused stream of air. For a clear /S/ sound, your tongue forms a shallow groove down its centre, directing a precise, thin stream of air right down the middle, over the tip of your tongue, and out through a tiny opening between your tongue and the roof of your mouth, just behind your front teeth. This focused airflow creates that crisp, sharp /SSSS/ sound we recognise.

    Now, picture what happens with a lateral lisp. Instead of that neat, central channel, the tongue is often flatter or positioned in a way that allows the air to escape over one or both sides. Think of it like a river overflowing its banks – the air, instead of flowing in a controlled stream, spills out sideways, creating that characteristic ‘slushy’ sound. This lateral airflow is what we need to retrain.

    Why is it tricky to treat?

    Treating a lateral lisp can be challenging for a few reasons:

    • Habitual muscle memory: The way the tongue moves and positions itself for a lateral lisp is deeply ingrained. It’s a motor habit that needs to be unlearned and replaced with a new, more precise movement.
    • Subtle differences: The difference between a lateral lisp and a correct /S/ sound can be quite subtle to perceive, both for the child and sometimes even for parents. This makes it harder for the child to self-monitor and correct.
    • Oral motor control: It requires fine motor control of the tongue muscles to create and maintain that central groove for airflow.

    My success with children aged six years and over

    I’ve found great success in treating lateral lisps, particularly with children aged six years and older. Why this age group? By this age, children typically have:

    • Increased awareness: They are more aware of their speech and often more motivated to make changes. They can better perceive the difference between their ‘slushy’ /S/ and a clear one.
    • Improved cognitive skills: They can understand and follow more complex instructions and strategies.
    • Better self-monitoring: Their ability to listen to themselves and correct their own speech improves significantly.
    • Enhanced oral motor control: Their fine motor skills, including those of the tongue, are more developed, allowing for greater precision.

    My approach focuses on a combination of auditory discrimination, tactile cues, and targeted myofunctional exercises to help children ‘feel’ the correct airflow and tongue placement. We use a variety of engaging activities to make the process fun and effective.

    It is crucial to understand tongue functioning and focusing on correcting improper oral resting posture and muscle function, which are often significant contributors to a lateral lisp. For example, if the tongue rests low and wide in the mouth consistently, or if there’s a tongue thrust during swallowing, these habits can prevent the tongue from achieving the precise, midline placement necessary for a clear /S/ or /Z/ sound. Through targeted exercises I aim to re-educate the oral and facial muscles, promoting correct tongue posture at rest, during swallowing, and, ultimately, during speech production. By strengthening the muscles responsible for tongue lifting and encouraging a more appropriate swallowing pattern we can establish the correct oral motor skills needed to overcome a lateral lisp and achieve clearer articulation.

    The recipe for success: Little and often

    The single most crucial ingredient for success in treating a lateral lisp is daily home practice of all the strategies given. This isn’t about long, arduous sessions; it’s about consistency. Think of it like building a muscle: short, frequent workouts yield better results than sporadic, intense ones.

    My recommended formula is ‘little and often’. This means:

    • Short, focused sessions: Aim for 5-10 minutes of practice, 2-3 times a day. This prevents fatigue and keeps the child engaged.
    • Integrate into daily routines: Practise while waiting for dinner, during a car ride, or before bedtime. Make it a natural part of their day.
    • Positive reinforcement: Celebrate every small success! Encouragement goes a long way in building confidence and motivation.
    • Parental involvement: Parents play a vital role in providing consistent cues and encouragement at home. I equip families with clear, easy-to-follow strategies.

    Overcoming a lateral lisp requires dedication, but with the right guidance and consistent practice, a clear, confident /S/ sound is achievable. If your child is struggling with a ‘slushy’ /S/, please don’t hesitate to reach out. Together, we can achieve success!

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • Learn the benefits of Cycles Phonology Approach in Speech Therapy

    A grey, green and orange circle overlaid with Cycles Phonological Approach
    Cycles Phonogogical approach

    When your child attends Speech and Language Therapy, it can look like your child’s therapist is playing. Therapy needs to be fun, which means carrying out therapy through the medium of play. But remember every approach used has evidence behind it. We need to know that therapy will be successful, so an evidence-based approach is essential.

    One of the approaches used for Speech Therapy (i.e., working on speech sound production) is the Cycles Phonology Approach. This approach focuses on the patterns and processes rather than each individual sound. For example, it may be working on final consonant deletion, so the omission of the final sound in words. As Speech and Language Therapists we understand that children can get frustrated and fatigued working on the same sound every day. This approach attempts to solve that. Hodson suggests, the approach is also useful for children with more speech sound errors, as therapists see progress in areas not targeted.

    How does the Cycles Phonology Approach work?

    Your Speech and Language Therapist will assess your child’s speech development and will then analyse the results. They will also look for which sounds they can produce with support (this is called stimulability). They will analyse patterns in the results and will formulate a plan.

    The Cycles Phonology Approach intervention allows your child to work in blocks. This might mean they work for half a week for 30 minutes on (e.g., clusters). Then the next half they’ll work for 30 minutes on a different process (e.g., omission of sounds at the end of words).

    Research has found that the following error patterns respond well to this approach:

    • Syllables (identifying the different parts in a word e.g., “ae-ro-plane”)
    • Final Consonant deletion (omission of the final sound e.g., “ca” instead of “cat”)
    • Initial consonant deletion (omission of the first sound e.g., “at” instead of “cat”)
    • Fronting (instead of making a sound at the back of the mouth, it’s made at the front e.g., “tat” instead of “cat”)
    • Backing (instead of making a sound at the front of the mouth, it’s made at the back e.g., “gun” instead of “bun”)
    • S blends (e.g., “sl, sm, sn, sk, sw”)
    • Gliding of liquids (e.g., “lellow instead of yellow”, “wabbit instead of rabbit”)

    What does a Speech and Language Therapy session look like when using the Phonology Cycles Approach?

    The format of the session remains the same for whichever speech sound pattern your child is working on. Your child’s Speech and Language Therapist will review the previous session. Then they will use an activity to work on your child hearing the sound several times (this is called ‘auditory bombardment’). Then your child will practise saying the sound. Next, the Speech and Language Therapist will check if your child can say any of the sounds which they haven’t been able to produce before, with support. This is called a stimulability check. After this, your child will take part in an activity which builds their awareness of sounds in words (such as a rhyming or syllable activity). The session will finish with another auditory bombardment task (i.e., hearing their tricky sound repeatedly).

    I will give you advice for practising at home, as it’s vital that your child learns in the correct way. We aim for 100 turns in therapy sessions, so it’s vital your child is motivated.

    Contact me to improve your child’s speech sounds and improve their confidence when talking.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • · ·

    From ‘Nailed it!’ in therapy to ‘Whoops!’ at home: Why generalising speech sounds is tricky

    As a parent, you’ve likely experienced the triumphant feeling when your child, who’s been working so hard on his or her /S/ sound, produces it perfectly in a therapy session. He or she is rocking those ‘sun’ and ‘socks’ words, his or her lisp seemingly a distant memory. You leave feeling elated, confident that all that hard work is finally paying off.

    Then you get home. And within minutes, you hear it: ‘Thooper!’ instead of ‘Super!’ Or maybe the clear /R/ in ‘rabbit’ from therapy reverts to a ‘wabbit’ when his or she is playing with his or her toys. It’s frustrating, confusing, and can feel like you’re back to square one.

    So, what’s going on? Why is it so difficult for children to take those amazing skills learned in a focused therapy session and seamlessly apply them to their everyday conversations? You’re not alone in wondering this. It’s a common challenge in speech therapy and understanding the ‘why’ can help both parents and children navigate this crucial stage.

    The brain’s habits: Old pathways are strong pathways

    Think of your child’s brain as having established ‘pathways’ for how he or she produces certain sounds. If he or she has been lisping his or her /S/ sound for years, that neural pathway is deeply ingrained. It’s like a well-worn path through a field: easy to follow because it’s always been there.

    In therapy, we’re essentially trying to forge a new path. We’re teaching him or her a new, more accurate way to make the sound. This new path is initially faint, like a barely visible trail. It takes conscious effort and repeated practice to strengthen it. Outside of the structured therapy environment, his or her brain often defaults to the old, comfortable, and well-established pathway, even if it’s not the most accurate.

    The demands of daily conversation: A multitasking challenge

    Therapy sessions are designed to be focused and controlled. We isolate sounds, practice them in specific words, and provide immediate feedback. There are minimal distractions, and your child’s full attention is on his or her speech production.

    Now, consider daily conversation:

    • Speed: We speak much faster in natural conversation than we do during structured practice. There is less time to think about individual sounds.
    • Cognitive load: Children are simultaneously thinking about what they want to say, understanding what others are saying, processing social cues, and managing their emotions. Adding the conscious effort of producing a new speech sound correctly on top of all that is a huge cognitive demand.
    • Variety of contexts: In therapy, we might practise ‘sun’ and ‘socks’. In real life, the /S/ sound appears in countless words, in different positions within words, and alongside a vast array of other sounds. Each new word and phonetic context present a fresh challenge.
    • Lack of immediate feedback: In therapy, the speech therapist is right there to provide instant correction and reinforcement. In a playground, during a family dinner, or while playing with friends, that immediate, consistent feedback isn’t present.

    The role of automaticity: Making it second nature

    The ultimate goal of speech therapy isn’t just correct sound production; it’s automaticity. This means producing the sound correctly without having to consciously think about it. It’s like learning to ride a bike. Initially, every pedal stroke and steering adjustment is deliberate. Eventually, it becomes second nature.

    Generalisation is the process of moving from conscious, controlled production to unconscious, automatic production. This takes time, consistent practice, and exposure to a wide variety of real-life speaking situations.

    How can we help? Bridging the gap

    So, what can parents do to help their children bridge this gap between therapy success and everyday speech?

    1. Be patient and positive: This is a marathon, not a sprint. Celebrate the small victories and avoid getting discouraged by setbacks. Your positive reinforcement is crucial.
    2. Practise little and often: Instead of long, infrequent practice sessions, aim for short, consistent bursts throughout the day. ‘Sprinkle’ in opportunities to practise their target sounds in natural conversations.
    3. Create ‘sound awareness’ moments: Gently draw your child’s attention to his or her target sounds in everyday words. For example, if he or she is working on /R/, you might say, ‘Oh, you said ‘wabbit.’ Can you try to make your /RRR/ sound for ‘rabbit’?’
    4. Model correct production: Continue to model the correct production of their target sounds in your own speech.
    5. Collaborate with your speech therapist: Your therapist is your best resource! Ask them for specific strategies and activities you can do at home to support generalisation. They can also provide guidance on when and how to gently correct your child.

    Tips and tricks

    Below I have listed a few good tips and tricks that can help the transition from therapy room to daily life:

    Empowering your child as the ‘sound detective’:

    • ‘Secret sound listener’: Instead of you doing the correcting, make your child the detective. When you’re having a conversation, say ‘your /S/ sounds are sometimes a bit “slippery”’ (or whatever fun, non-judgmental term you like). Ask your child to quietly listen for your /S/ sounds. You can even purposely make a few ‘slippery’ ones (or correct yourself immediately after) and see if they notice. This shifts the focus from being corrected to actively listening and identifying the sound in a non-threatening way.
    • ‘Sound scorecard’: For a short period (maybe 10–15 minutes during a specific activity, like dinner or a game), provide a small notepad and pencil. Explain that your child is going to listen for his or her /S/ sounds and gently mark a tally every time he or she uses it correctly. The goal isn’t perfection, but awareness. This gives your child agency and a visual representation of progress. You can even make it a game: ‘Let’s see how many /S/ sounds we can catch in five minutes!’
    • /S/ sound song/rhyme creation: Work together to create silly songs or rhymes that are packed with /S/ sounds. The sillier, the better! You can sing them in the car, while doing chores, etc.
    • /S/ sound superpower: Frame the new sound skill as a ‘superpower’. ‘You’re getting so good at using your /S/ superpower! It’s going to help you speak so clearly and confidently.’
    • Highlighting successes: Always go out of your way to acknowledge and praise successful /S/ productions in natural conversation. ‘I really understood you clearly when you said ”s_top”.’ or ‘That /S/ sound was perfect when you told me about the “s_tory”!’

    Important considerations:

    • Keep it low-pressure: The goal is generalisation, not perfection. If your child is feeling pressured, he or she will likely revert to old patterns.
    • Focus on awareness, not just correction: Help your child become aware of his or her own speech rather than relying on you for corrections.
    • Short, frequent bursts: A few minutes of subtle focus multiple times a day is more effective than one long, forced session.
    • Acknowledge feelings: If your child expresses frustration about ‘being corrected’, validate these feelings. ‘I understand it can feel like a lot of listening, but we’re just trying to help you use that super /S/ sound all the time!’

    By incorporating these strategies, you can help your child naturally integrate the new /S/ sound into daily speech, fostering independence and confidence without it feeling like constant ‘testing’ or ‘correction’. Generalising new speech sounds is arguably the hardest part of speech therapy, but it’s also the most rewarding. With patience, consistent effort, and a collaborative approach between parents and therapists, children can successfully integrate their new, clearer speech sounds into every aspect of their daily lives.

    Any comments or if you need help and support with your child’s speech please do not hesitate to get in touch with me: simply fill out the contact form here on the website. I endeavour to reply within 48 hours.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • · · ·

    Seeing sounds: How visual gestures boost speech sound learning

    Learning to produce new speech sounds can be a complex process for young children, especially those facing challenges with speech sound disorders or motor planning difficulties. It’s not just about knowing what a sound ‘should’ sound like; it’s about figuring out where to put your tongue, how to shape your lips, and how much air to push out. This is where the power of visual gestures comes in – literally helping children see how to make sounds.

    As speech and language therapists, we frequently use visual cues and hand gestures to teach articulation. These techniques are incredibly effective, particularly when a child is struggling with the motor planning aspect of speech production.

    In the video clip above you see me teaching

    • the /SH/ sound: the hand makes a C-shape and moves forward showing both how the lips are positioned and the air flowing forward
    • the /S/ sound: the index finger shows a snake like movement going forward- also showing the air flow again
    • the /W/ sound: my right hand moves forward and fingers splay out showing that the lips open up at the end of the sound
    • the /K/ sound: my finger points to the back of my throat where the tongue needs to raise.

    An overview of motor planning for speech – what do we mean by that?

    Think about learning to ride a bike or play a musical instrument. You don’t just know how to do it instantly. You have to plan the movements, practise them, and make adjustments. Speaking is similar! Our brains must:

    1. Plan the sequence of movements needed for each sound and word (e.g., /B/ requires lips together, then release, while /T/ requires the tongue tip behind the top teeth, then release).
    2. Execute those plans rapidly and precisely.

    For some children, especially those with conditions like Childhood Apraxia of Speech (CAS) or other severe articulation disorders, this motor planning process is disrupted. They know what they want to say, but their brain struggles to send the correct, consistent messages to their articulators (lips, tongue, jaw, velum). This can make speech sound learning incredibly frustrating.

    Why use visual gestures?

    Visual gestures provide an additional, powerful sensory input that can help bridge the gap between knowing a sound and producing it. Here’s how and why they are so beneficial:

    1.      Providing a visual map:

    • How it helps: Many speech sounds are ‘hidden’ inside the mouth. It’s hard for a child to see where their tongue needs to go for a /K/ sound (back of the tongue to the roof of the mouth) or a /T/ sound (tongue tip behind teeth). A simple hand gesture can visually represent this mouth movement. For example, a hand gesture for /K/ might involve sweeping the hand back towards the throat, while for /T/, it might be a tap on the chin.
    • Why it works: Children are highly visual learners. Seeing a physical representation of an abstract mouth movement gives them a concrete ‘map’ to follow, making the process less mysterious and more manageable.

    2.      Enhancing motor planning and memory:

    • How it helps: When a child simultaneously moves their hand (the visual gesture) and attempts to make the sound, they are engaging multiple sensory systems (visual, tactile, proprioceptive – body awareness). This multi-sensory input strengthens the neural pathways associated with that speech sound.
    • Why it works: This multi-modal learning helps to solidify the motor plan for the sound in the brain. It’s like having more ‘hooks’ to hang the information on, making the sound easier to recall and produce consistently. The gesture becomes a built-in reminder.

    3.      Reducing cognitive load:

    • How it helps: Instead of just hearing the sound and trying to figure out the complex motor sequence, the child has a visual cue to guide them. This reduces the mental effort required to decode the sound production.
    • Why it works: When cognitive load is lower, the child can focus more effectively on the specific motor execution of the sound, leading to faster progress and less frustration.

    4.      Increasing engagement and success:

    • How it helps: Gestures can make therapy more interactive and fun! When a child successfully produces a sound with the help of a gesture, it’s a tangible victory.
    • Why it works: Success is a powerful motivator. When children experience success, they are more likely to stay engaged, participate actively, and feel more confident in their ability to learn new sounds.

    5.      Supporting self-correction:

    • How it helps: Once a child learns the gesture associated with a sound, he or she can use it as a self-monitoring tool. If he or she makes an error, he or she can use the gesture to remind himself or herself of the correct mouth position or movement.
    • Why it works: This promotes independent learning and reduces reliance on constant adult prompting.

    Conclusion

    The journey of speech development can be challenging, but visual gestures offer a powerful and effective tool for teaching new sounds, especially when motor planning is a factor. By providing a clear visual map, strengthening motor memory, reducing cognitive load, and fostering engagement, these gestures pave the way for clearer communication and greater confidence. If your child is struggling with speech sounds, consider talking to a Speech and Language Therapist to get guidance on how visual gestures might be incorporated into the therapy plan. Because sometimes, seeing truly is believing (and speaking!).

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1