Autism – Benefits of Early Assessment and Intervention

| | |
I think my child might be autistic – how can we help?
Image by macrovector on Freepik

Consulting a Specialist Speech and Language Therapist can help you in several ways: assessment, informal and formal observation, discussion and advice, onward referrals, direct intervention, parent coaching, educational support and much more, all geared towards supporting you the parents, and helping your child to flourish and thrive.

First up, we can help you with assessment and advice: with a wealth of expertise in observing childrens’ play and communication, as well as knowledge of the latest research we can see a child’s strengths and areas of struggle very quickly indeed.

Within a short space of time, we can identify the areas we need to focus on and start guiding you towards helping your child to connect, respond, react and feel better.

Early detection is key

If autism is detected in infancy, then therapy can take full advantage of the brain’s plasticity. It is hard to diagnose Autism before 18 months but there are early signs we know to look out for. Let’s have a brief look at the sorts of things we look at.

The earliest signs of Autism involve more of an absence of typical behaviours and not the presence of atypical ones.

  • Often the earliest signs are that a baby is very quiet and undemanding. Some babies don’t respond to being cuddled or spoken to. Baby is being described as a ‘good baby, so quiet, no trouble at all’.
  • Baby is very object focused: he/she may look for long periods of time at a red spot/twinkly item further away, at the corner of the room for example.
  • Baby does not make eye contact: we can often see that a baby looks at your glasses for example instead of ‘connecting’ with your eyes.
  • At around 4 months we should see a baby copying adults’ facial expressions and some body movements, gestures and then increasingly cooing sounds we make; babies who were later diagnosed with autism were not seen to be doing this.
  • Baby does not respond with smiles by about 6 months.
  • By about 9 months, baby does not share sounds in a back-and-forth fashion.
  • By about 12 months baby does not respond/turn their heads when their name is called.
  • By around 16 months we have no spoken words; perhaps we hear sounds that sound like ‘speech’ but we cannot make out what the sounds are.
  • By about 24 months we see no meaningful two-word combinations that are self-generated by the toddler. We might see some copying of single words.

24 months plus:

  • Our child is not interested in other children or people and seems unaware of others in the same room/play area.
  • Our child prefers to play alone, and dislikes being touched, held or cuddled.
  • He/she does not share an interest or draw attention to their own achievements e.g., ‘daddy look I got a dog’.
  • We can see our child not being aware that others are talking to them.
  • We see very little creative pretend play.
  • In the nursery our child might be rough with other children, pushing, pinching or scratching, biting sometimes; or our child might simply not interact with others and be unable to sit in a circle when asked to.

What sort of speech and language difficulties might we see?

Our child might do any of the following:

  • have no speech at all, but uses body movements to request things, takes adults by the hand
  • repeat the same word or phrase over and over; sometimes straight away after we have said it or sometimes hours later
  • repeat phrases and songs from adverts or videos, nursery rhymes or what dad says every day when he gets back from work etc.
  • copy our way of intonation
  • not understand questions – and respond by repeating the question just asked:
    • adult: Do you want apple? child: do you want apple?
  • not understand directions or only high frequency directions in daily life
  • avoid eye contact or sometimes ‘stares’
  • lack of pointing or other gestures

Common behaviours:

  • Hand flapping
  • Rocking back-and-forth
  • Finger flicking or wriggling/moving
  • Lining up items/toys
  • Wheel spinning, spinning around self
  • Flicking lights on and off, or other switches
  • Running back-and-forth in the room, needing to touch each wall/door
  • Loud screaming when excited
  • Bashing ears when frustrated or excited
  • Atypical postures or walking, tip toeing, can be falling over easily, uncoordinated
  • Can be hyper sensitive to noises, smells, textures, foods, clothing, hair cutting, washing etc.
  • Being rigid and inflexible, needing to stick to routines, unable to transition into new environments
  • Food sensitivity, food avoidance, food phobias

I mentioned this to be a ‘brief’ look at the areas and it is: each topic is looked at very deeply and each area is multi-facetted therefore a diagnosis is rarely arrived at very quickly. We want to make sure we have covered all aspects and have got to know your child very well before coming to conclusions.

Early detection is key, because we want to start helping your child to make progress as quickly as is possible. If you feel /know that your child is delayed in their speech and language development and you would like a professional opinion then please do contact me, I look forward to supporting you. It is important to know at this point, that if your child only has one or two of the above aspects it may mean that your child is simply delayed for reasons other than Autism and if that is the case, we will be able to help you iron out a few areas of need so that your child can go on thriving.

If you need help with your child, please do not hesitate to contact me.


Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.


1

Similar Posts

  • ·

    Why structure, high expectations and warmth matter in speech therapy

    If you were to peek through the window of one of my speech therapy sessions, you might notice two things: a room full of engaging games and activities, and a therapist who is carefully guiding a child towards a specific goal.

    Why structure, high expectations and warmth matter in speech therapy. A photo of Sonja McGeachie smiling.

    There will be laughter, encouragement and opportunities to play. But there will also be moments when I ask a child to stop, listen carefully, try a sound again or adjust the way they are producing it.

    To an outside observer, this might sometimes look quite structured. And that raises an important question: does effective speech therapy need to be more than simply playing with a child?

    My answer is yes.

    Play has a valuable place in speech therapy, but when a child is working on a speech sound disorder, we also need clinical expertise, purposeful practice, careful listening and clear goals. Children deserve sessions that are enjoyable and supportive, while also helping them develop the skills they need to communicate more clearly and confidently.

    For me, the key is combining warmth and encouragement with high expectations, appropriate structure and an approach tailored to each individual child.

    Here is why I believe this balance matters.

    1. Speech sound therapy involves learning a new skill

    Learning to produce a speech sound accurately is not simply a matter of telling a child what to do. Speech involves highly coordinated movements, and children who have difficulty producing particular sounds may need considerable support to develop new or more consistent ways of producing them.

    Think about learning to play a musical instrument. Understanding what a note should sound like is not the same as being able to play it accurately. It takes practice, feedback and time to develop the necessary skills.

    Speech sound therapy can be similar. A child may understand that they need to make a /K/ sound, for example, but continue to produce a /T/ sound instead. They may need help to notice the difference, understand where the sound is produced in the mouth and practise the new movement with appropriate support.

    This is where purposeful practice becomes important.

    During a session, I listen closely to how a child produces a sound. I may model the sound, use a visual cue, help the child notice their tongue position or break the task into smaller, more manageable steps.

    Sometimes a child can produce a sound accurately straight away. At other times, we need to slow down, change our approach or practise at an easier level before moving on.

    The aim is not simply to produce lots of sounds. It is to help a child practise in a way that supports accurate, increasingly consistent speech.

    That means I will sometimes ask a child to try again. Not because I expect perfection, but because I want to help them discover what works and build on their successes.

    2. Clear structure can help children know what to expect

    Some children arrive at therapy full of energy. Others may find it difficult to concentrate on a task, manage transitions or persist when something feels challenging.

    Expecting every child to sit still and work in exactly the same way would not be realistic, nor would it be appropriate.

    However, children often benefit from knowing what is happening, what we are working towards and what comes next.

    For example, I might explain:

    ‘First, let’s practise five careful /S/ sounds together. Then we’ll take our turn in the game.’

    This gives the child a clear, achievable goal and a predictable next step. For another child, I might use a visual timetable, shorter practice bursts, movement breaks or a more playful activity to support participation.

    Structure does not mean that every session must look the same. It means that the activities have a purpose and that I am making thoughtful decisions about how best to help the child learn.

    If a child becomes tired, frustrated or overwhelmed, I may need to adapt the task rather than simply insist that they continue. Sometimes a short break or a different approach is exactly what enables the child to return to the activity successfully.

    My responsibility is to recognise what the child needs while keeping sight of the therapeutic goal.

    3. Warmth and high expectations belong together

    I believe one of the most important qualities of a good speech and language therapist is the ability to combine a positive relationship with clear clinical guidance.

    Children need to feel safe enough to try something difficult, make mistakes and have another go. They also need a therapist who can recognise when they are ready for the next step and help them work towards it.

    In my sessions, encouragement might sound like this:

    ‘That was a good try. Let’s see if we can make that sound even clearer together.’

    ‘I know this sound is tricky. Let’s slow it down and find the mouth position that works.’

    ‘You did that one really carefully! Can you remember what you did with your tongue?’

    These are small moments, but they matter. They help children understand that speech sounds can take practice, that mistakes are part of learning and that they can make progress with the right support.

    I celebrate genuine achievements, whether that means producing a difficult sound accurately for the first time, becoming more aware of how a sound feels, or managing to use a new skill more consistently.

    I also want children to understand that they are not expected to get everything right immediately. My job is to guide them, give them appropriate feedback and help them develop their skills step by step.

    High expectations should never mean expecting every child to progress at the same pace. They mean taking each child’s potential seriously and giving them the support they need to move forward.

    4. Play can be powerful when it has a purpose

    I love using games and playful activities in therapy. They can motivate children, create opportunities for interaction and make repeated practice much more enjoyable.

    But the game itself is not the therapy. It is one of the ways I help a child engage with the therapeutic task.

    For example, a simple board game might provide opportunities to practise a target sound in carefully chosen words. A picture activity might help a child listen for the difference between two sounds. A motivating toy might encourage a child to practise a word several times without the session feeling repetitive.

    While the child is playing, I am listening, observing, adjusting the level of difficulty and deciding what support to offer next.

    If a child is not yet able to produce a sound accurately in a particular word, I may return to an easier level of practice. If they are achieving the target consistently, I may begin to introduce more challenging words or activities that help them use the sound in a wider range of situations.

    The activities may look simple, but the clinical reasoning behind them is important.

    Parents should be able to understand what their child is working on, why a particular approach has been chosen and how progress is being monitored.

    For me, effective therapy is about making the session purposeful, responsive and productive.

    5. Progress takes clinical expertise, practice and partnership

    When parents seek specialist speech and language therapy, they understandably want to see progress. They want their child to be understood more easily, to feel more confident communicating and to experience fewer frustrations when speaking.

    My role is to assess the child’s speech carefully, identify the areas that need support and develop an appropriate plan.

    Depending on the child’s needs, this may involve working on individual speech sounds, helping them distinguish between sounds, addressing patterns that affect several sounds, or using a more specialised approach where speech motor planning is a concern.

    There is no single programme that suits every child. The type of intervention, the amount of practice and the pace of progress will depend on the child’s individual profile and response to therapy.

    I monitor how a child is progressing and adjust my approach accordingly. I also explain what we are working towards and, where appropriate, suggest practical ways parents can support learning between sessions.

    Home practice is particularly valuable, and it needs to be realistic and manageable for each family. Even a short period of well-supported practice provide useful opportunities to build on what a child has been learning in therapy.

    Ultimately, I want parents to feel informed and involved, with a clear understanding of their child’s goals and the steps we are taking to work towards them.

    The takeaway: Structure with warmth

    I believe children deserve speech therapy that combines a warm, trusting relationship with skilled clinical intervention.

    I will encourage a child, celebrate their achievements and make sessions enjoyable. I will also listen carefully, give feedback, revisit difficult sounds and help them work towards their goals.

    Sometimes that means asking for another attempt. Sometimes it means changing the activity, taking a break or approaching the task in a completely different way.

    The important thing is understanding when to encourage, when to challenge and when to adapt.

    High expectations are not about making children comply. They are about believing in their capacity to learn while giving them the individual support they need to succeed.

    For me, that is the balance at the heart of effective speech sound therapy: warmth, structure, clinical expertise and a genuine commitment to helping every child make meaningful progress.

    Looking for specialist speech sound therapy?

    If your child has difficulty producing particular speech sounds, is difficult to understand or is becoming frustrated when trying to communicate, an individual assessment can help clarify their needs and identify appropriate next steps.

    At London Speech and Feeding, I provide tailored speech and language therapy with clear goals, careful clinical guidance and an approach that recognises each child as an individual.

    Get in touch to arrange an initial assessment and discuss how I may be able to help your child.

    Sonja McGeachie

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • ·

    Discover more about Verbal Dyspraxia

    What is Verbal Dyspraxia?

    Apraxia or dyspraxia is a difficulty in motor planning, which sometimes can be seen in both gross and fine motor skills, as well as speech. Gross motor refers to difficulties in coordinating the whole body (e.g., bumping into things frequently, often falling over hurting themselves or others through being “clumsy” or unsteady). Fine motor movements refer to smaller, more precise movements (e.g., difficulties doing anything with their hands such as holding a spoon or pen).

    Verbal dyspraxia

    In Dyspraxia of Speech, instead of seeing a coordinated smooth way of talking, we see the articulators (tongue, lips, cheeks) and voice coordinating very smoothly. The voice can be very quiet or very loud. Muscle tone can be weaker at times. Speech sounds are very unintelligible, with a flat voice that can sound forced. It may be that the timings of verbalisation appear random and that children can say a certain word once and never again. This is often what we hear from parents.

    It is interesting to note that many of our autistic clients are either non-speaking or are reluctant speakers. Sometimes they say a word once and then never again. Others say lots of words but the words are very hard to make out. Did you know that about 40% of autistic people have verbal dyspraxia? (Richard, 1997). Because the problem is one of motor planning, not of automatic motor execution, once a plan has become automatic, it is easier to get back to it and this is why we often see repetitive patterns that can be called ‘stims’ (Marge Blanc, 2004).

    How can Speech and Language Therapy help?

    Children with verbal dyspraxia can make great progress!

    We provide frequent and appropriate speech movement opportunities and with time and the right support, children will move forward and begin to speak more fluently and with greater intelligibility. It is important to know this can take time.

    We provide Oral Motor Therapy using a variety of approaches to practise breathing, vocalising on the outbreath, and sequencing our speech movements.

    We design carefully tailored programmes focusing on words that have a lot of power (e.g., NO, GO, UP, IN, OUT, LET’S GO, STOP).

    We offer shared enjoyment, and laughter. This helps a child find their voice. Other ways of finding our voices include singing or humming, or even yelling/shouting!

    The most difficult phase of verbal dyspraxia is initiation, that is to start talking, to start producing a word. Frequent “automatic” repetition supports children with initiation because it removes the element of “thinking to start”. I often ask a child to repeat a word 5-10 times (with rewards at the end. A little game works well). You can see that with repetition the act of initiating is taken out of the equation as you are “on a roll “as it were.

    Once a child starts to find their voice, we will be able to hear them talk lot… And if we give them credit and presume that what they are saying has meaning, we will find in time that their words become clearer and more intelligible. If we listen carefully, we can detect real words and phrases.

    For more tips and support, please get in touch!


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    0
  • Using AAC – Augmentative and Alternative Communication for non-verbal and early verbal children

    Using a Core Vocabulary Board

    Your Speech Therapist might have been advising you to introduce words to your child with the help of a CORE BOARD. What on earth is she talking about and why would we want to do this, I hear you think – and in fact this is what I get asked a lot, as I often do recommend using Core Boards.

    Core boards belong to the category of Augmentative and Alternative Communication (AAC ) and they can be really useful for:

    • Children or adults who cannot speak at all or who are very hard to understand.
    • Children who are slow to speak and have difficulty expressing themselves verbally, due to genetic conditions as Down Syndrome, Verbal dyspraxia, Autism or any other learning difficulty that means a child is slow to develop speech.

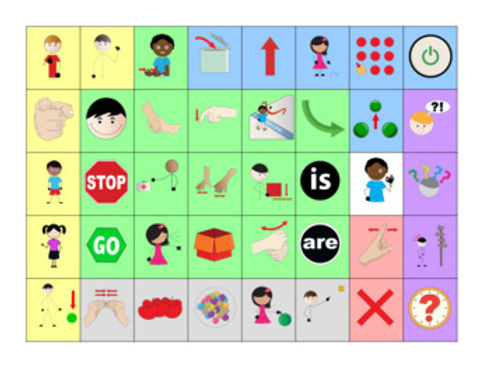
    Here is what a Core board might look like, in fact this is one that I love to use. It is made by Beautiful Speech Life, there are a ton of similar boards out there for free. I have also made my own, you can check it out on my Instagram feed.

    Using a Core Vocabulary Board

    What is Core Vocabulary/ Core words?

    Core vocabulary consists of the most common words used by children throughout a day. In 2003 Banajee and Dicarlo et al found that 50 % of pre-schoolers in their project used nine words consistently across their daily play and meal routines. These words are Core words and are typically the ones you can see on a board, like the one above.

    How To Use It

    Adults always first need to consistently model and show their child how to use a board. This is key! For example: Adult can point to “YOU” “WANT” ‘MORE” and then point to the cup of Water on the counter. Child could then reply either by shaking his/her head and/or pointing to “NOT” which also stands for “NO”. Then adult can point to “NOT” “MORE” and do an OK sign as well. Eventually Child can initiate a request and point to “I” “ WANT” “MORE” and then point to the cup on the counter.

    This is not as cumbersome or limited as it first sounds or appears. Here’s why: As adult you can talk normally and, of course, many words you are using will not be on this board. But some will be, and you will be surprised how many you can find when you start using it. So you could say quite normally: Hey lovely (name of your child) would YOU LIKE some MORE water? The words in capital are on the board which you can point to as you speak normally. Basically, you are showing/saying to your child: “We can speak and these are the pictures we can use to help us; We call this TOTAL COMMUNICATION, as communication is so much more than just words! Great communication can be silent, where we use our facial expression, our smile, our eyes, our hand gestures, body movements and yes, of course, words. But when words fail us, these boards are so helpful.

    This still does not answer your original question of: why would I want to do this, I want my child to talk!? You are a SPEECH Therapist, please help my child TALK, not point to pictures, that is not what I had in mind.

    Let Me Explain

    When speech is difficult for a child it doesn’t mean that there is nothing to talk about! Of course, we want all our children and all people to speak because it is the easiest and most effective way of communicating, no doubt! However, sometimes this is very hard for some children and whilst we are always working towards speech where possible, we also want to make sure that whilst figuring out how to speak, your child has a MEANS TO COMMUNICATE. Using a board like this might well be a temporary strategy but whilst you are using it and working on their speech you will find a reduction in tantrums and frustration as you child is able to express themselves more effectively.

    Often we find that as soon as we offer a CORE VOCABULARY like the above sample a child who has had no or very few words suddenly blossoms and starts to point to new words on the board and starts to PRACTICE USING THESE WORDS!! Practice makes perfect, right? Yes it totally does! There is lots of evidence that tells us that using Core Vocabulary Boards ENHANCE AND SUPPORT SPEECH PRODUCTION AND NOT HINDER IT. Using a board like this will only ever be helpful to your child and will never make your child “lazy” – too lazy to speak? NO SUCH THING!

    Here is what one of my parents says about the core board we use with her little boy:

    “the board has been a game changer, my son is a visual learner so it really helps to have the board as he associates communication so much easier this way. We have incorporated his twin sister who models it’s use and have definitely seen improvement in speech through its support and his frustration around being unable to verbally communicate at times has definitely lessened”

    K Connolly, Mother of Tom (aged 3.5 years).

    Reading and hearing this makes me so happy!

    In addition to general core board above I also sometimes use a Core Board that is specific to an activity, such as for example BLOWING BUBBLES. Below is an example of such a board, which you can use very nicely during a bubble blowing activity and sometimes it is a nice place to start for newcomers, this can be an easy introduction. You can download this and many similar boards on www.widgit.com for free!

    Using a Core Vocabulary Board

    There is so much more to say about AAC and using Coreboards, visit my Instagram you can find a bit more information on how I use them.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • · ·

    The picky eater’s plate: Introducing solids to toddlers with ARFID

    Designed by Freepik

    Mealtimes can be a battleground for parents of picky eaters, especially toddlers with Avoidant/Restrictive Food Intake Disorder (ARFID). I see a great number of toddlers with Autism traits and many of my clients are picky eaters from mild to severe. Take a look at my blog for an outline of what the issues are and how to try and help.

    ARFID goes beyond typical ‘picky eating’ and can significantly impact a child’s growth, nutrition, and social-emotional well-being. If your toddler is resistant to trying new foods or has a very limited diet, here are some strategies to navigate the introduction of solids:

    1. Understand ARFID:

    ARFID is a diagnosable eating disorder characterised by:

    • Limited food variety: Eating only a small range of foods, often with specific textures or colours.
    • Fear of new foods: Intense anxiety or aversion to trying unfamiliar foods.
    • Sensory sensitivities: Heightened sensitivity to taste, smell, texture, or appearance of food.
    • Lack of interest in eating: May show little interest in food or mealtimes.

    2. Seek professional guidance:

    • Paediatrician and/or gastroenterologist: Rule out any underlying medical conditions.
    • Registered dietitian: Assess nutritional needs and create a balanced meal plan.
    • Speech and language therapist (SLT): If oral-motor skills or sensory sensitivities are contributing to feeding difficulties.
    • Occupational therapist (OT): If sensory processing challenges are affecting mealtime behaviours.
    • Child psychologist: If anxiety or emotional factors are contributing to ARFID.

    3. Strategies for introducing solids:

    • Start small: Introduce one new food at a time, in small amounts, alongside familiar favourites.
    • Patience is key: It can take multiple exposures (up to 10–15 times!) for a child to accept a new food. Don’t give up!
    • Positive reinforcement: Praise and encouragement for any interaction with the new food, even just touching or smelling it.
    • No pressure: Avoid forcing or pressuring the child to eat. This can create negative associations with food.
    • Make it fun: Present food in playful ways, use cookie cutters for fun shapes, or involve the child in food preparation.
    • Sensory exploration: Encourage exploration of food through touch, smell, and sight before tasting.
    • Role modelling: Show the child that you enjoy eating a variety of foods.
    • Use fun utensils: your child might like characters from ‘Frozen’ or ‘Dinosaurs’ or ‘Diggers’ there are a host of character-based cutlery and cups/plates to be had. Also, I really rate these two items very highly they are so good so I want to share these with you. Both are available online. But warning: the cup is outrageously expensive as it comes from the United States and is sold by a small scale company. But I feel this is cup very worth trying, I have had good results with this.
    • Gradual desensitisation: Start with foods that are similar in texture or taste to accepted foods, then gradually introduce more challenging options.
    • Food chaining: Introduce new foods that are similar in taste, texture, or appearance to accepted foods.

    4. Mealtime Environment:

    • Positive and relaxed: Create a calm and enjoyable mealtime atmosphere.
    • No distractions: Minimise distractions like TV or toys.
    • Consistent schedule: Offer meals and snacks at regular times.
    • Child-sized portions: Offer small, manageable portions to avoid overwhelming the child.
    • Involve the child: Let the child choose their utensils, plate, or cup.

    5. Remember:

    • Every child is different: What works for one child may not work for another.
    • Progress takes time: Be patient and celebrate small victories.
    • Focus on the positive: Praise any positive interaction with food.
    • Seek support: Connect with other parents or support groups.

    Introducing solids to toddlers with ARFID can be challenging, but with patience, persistence, and professional guidance, you can help your child develop a healthier relationship with food.

    Get in touch with me via my contact form if you need support

    Sonja McGeachie

    Early Intervention Speech and Language Therapist

    Feeding and Dysphagia (Swallowing) Specialist The London Speech and Feeding Practice

    The London Speech and Feeding Practice


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • · ·

    Using AAC in daily life

    Communication is a fundamental human right, a bridge that connects us to the world and each other. For many, spoken language is the primary mode, but for individuals with complex communication needs, Augmentative and Alternative Communication (AAC) offers a powerful pathway to expression and connection. This guide will demystify AAC, highlight the crucial role of modelling, and provide practical examples of how low-tech AAC can be seamlessly integrated into everyday activities.

    What is AAC in a nutshell?

    AAC encompasses a wide range of tools and strategies that supplement or replace spoken language. It’s not about replacing speech, but rather about providing additional ways for individuals to communicate effectively. Think of it as a spectrum:

    • Unaided AAC: This involves using only your body, such as gestures, facial expressions, body language, and sign language.
    • Aided AAC: This involves external tools or devices. These can range from low-tech options like picture boards and communication books to high-tech speech-generating devices (SGDs) and apps on tablets.

    The beauty of AAC lies in its flexibility and personalisation. It empowers individuals to express their wants, needs, thoughts, and feelings, fostering independence and participation in all aspects of life.

    Modelling is KEY: Showing, not just telling

    Imagine trying to learn a new language without ever hearing it spoken. It would be incredibly difficult, right? The same principle applies to AAC. Modelling is the single most important strategy for teaching and supporting AAC users. It means actively using the AAC system yourself while talking, demonstrating how to navigate the system and express messages.

    Here’s why modelling is so vital:

    • It’s how we learn language: Typically developing children learn language by hearing it constantly around them. AAC users need the same immersion.
    • It reduces pressure: When you model, you’re not asking the individual to communicate, you’re just showing them how it’s done. This takes the pressure off and makes learning more enjoyable.
    • It expands vocabulary and concepts: By modelling a variety of words and phrases, you introduce new vocabulary and demonstrate how to combine symbols to create more complex messages.
    • It demonstrates purpose: Modelling shows that AAC is a functional and effective way to communicate, not just a set of pictures.

    So, how do you model? It’s simple: point to the symbols on the communication board or device as you speak the words. For example, if you say, ‘Time to eat breakfast,’ you might point to ‘time’, ‘eat’, and ‘breakfast’ on the board.

    Low-tech AAC in action: Everyday activities

    Low-tech AAC, such as communication boards, books, or single-page displays, is incredibly versatile and can be easily incorporated into daily routines. These can be as simple as printed pages with symbols, laminated for durability.

    Let’s explore how low-tech AAC can be used throughout a typical day, with examples of symbols:

    1. Getting ready for nursery

    Mornings can be busy, but they also offer rich communication opportunities. A ‘Getting Ready’ communication board can help sequence activities and offer choices.

    Activity example:

    ‘Time to get up!’ (point to GET UP). ‘What do you want to wear today, the blue shirt or the red shirt?’ (point to GET DRESSED) ‘Then, we brush teeth’ (point to TOOTHBRUSH) and so on.

    AAC mornings symbol examples

    2. Breakfast Time

    Mealtimes are perfect for making choices, expressing preferences, and commenting. A ‘Breakfast’ communication board can focus on food items, actions, and social comments.

    Example symbols:

    AAC meal times symbol examples

    Activity example:

    ‘What do you want to eat for breakfast?’ (point to EAT). ‘Do you want cereal or toast?’ (point to CEREAL or TOAST). If they finish their milk, you could say, ‘Are you ALL DONE or do you want MORE MILK?’ (point to symbols).

    3. Catching the Bus

    Even routine transitions like catching the bus can be communication rich. A small, portable ‘Travel’ board can be useful.

    Example symbols:

    AAC catching the bus symbol examples

    3. Being on the playground

    The playground is a dynamic environment perfect for commenting, requesting actions, and engaging in social play.

    AAC playground symbol examples

    Activity example:

    ‘Let’s PLAY!’ (point to PLAY). ‘Do you want to go on the SWING or the SLIDE?’ (point to symbols). If they are on the swing, you can say, ‘Do you want to go FAST or SLOW?’ (point to symbols) and ‘Push AGAIN!’ (point to PUSH) You can also model social language like ‘It’s MY TURN.’

    Beyond the symbols: Key takeaways

    • Consistency is key: Use AAC consistently across all environments and with all communication partners.
    • Be patient: Learning a new language takes time. Celebrate small successes.
    • Make it fun: Integrate AAC into play and enjoyable activities.
    • Follow the individual’s lead: Respond to all communication attempts, even if they are imperfect.

    In the video below I model how to integrate AAC into everyday activities with a few more examples and I discuss the difference between AAC and PECS.

    If you need some inspiration with using AAC or would like your child assessed for the right type of AAC then please get in touch.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • · · ·

    How parent coaching turns story time into a communication success

    We often hear from parents who are trying their best to connect with their child, especially when reading books, but are met with frustration. They’ll say, ‘I read the book exactly as it’s written, but my child can’t focus for very long and just runs off!’ or ‘my child just flicks through the pages then turns it upside down and runs off with it’ or similar.

    It’s a common story. Traditional reading—going through the text from cover-to-cover—has its place of course, but for little ones with a language delay or autism it can move too quickly and place all the focus on the book’s words, not on the interaction.

    But what if I told you that story time could become one of the most fun and productive times for your child’s communication development?

    Watch the fantastic little video clip above! You can see the pure joy and connection between this dad and his son. This is the same family who, just a few weeks ago, felt defeated when trying to read a book, with their child quickly losing interest and leaving the reading/book corner.

    What changed?

    The power of parent coaching and Hanen principles

    The difference you see in the video is the direct result of parent interaction therapy, or parent coaching, based on the internationally recognised Hanen principles.

    I didn’t ‘fix’ the child. Instead, I coached the parents in a few simple, powerful strategies that completely changed the dynamic of their interaction. Instead of being a time for teaching and instruction, story time became a back-and-forth conversation.

    Here are the four major transformations that coaching helped this family achieve:

    1. From reader to play partner

    Before coaching, the parents felt their job was to read the text and to teach the words in it to their child. Now, their job is to follow their child’s lead. They learned to Observe, Wait, and Listen (OWL). If the child points to the tree or the badger on the page, the parent talks about the tree or the badger.

    The result

    The child is now initiating and leading the conversation! He is sharing what he finds interesting, which makes him feel powerful and keeps him deeply engaged.

    2. Building connection and attention

    When parents focus solely on reading, they often forget to make frequent eye contact and use animated facial expressions. The principles taught them to put the text aside and prioritise connection.

    The result

    Our little boy is looking at his dad more frequently, making great eye contact, and clearly having fun! When the interaction is fun, the child’s attention span naturally lengthens, allowing him to attend to the book and the interaction for a much longer time.

    3. Creating opportunities for communication

    The parents learned simple ways to prompt communication without pressure. They stopped asking knowledge-based questions (‘What colour is that? Or point to the pig!’), which can feel like a test.

    Instead, they learned to use techniques like ‘Saying less and pausing’ or ‘copying their little one’s echolalia ‘, signalling that they are very interested in what he is saying and that his communication matters!

    The result

    The child is now spontaneously using strings of sounds and gestures to communicate his needs and interests, knowing and enjoying his parents’ enthusiastic responses.

    This video is a testament to the fact that you are your child’s best therapist. With the right tools and coaching, you can transform everyday routines, like reading a book, into the most joyful and effective communication sessions.

    4. Acknowledging and interpreting echolalia

    In the video, you may hear the little boy repeat a phrase from the book or from what his dad just said. This is called echolalia, and for a long time, it was often dismissed or discouraged.

    However, a core principle of our parent coaching is that echolalia is communication. For children who are ‘Gestalt Language Processors,’ these memorised phrases (or ‘gestalts’) are their building blocks of language.

    The key is not to stop the repetition, but to become a ‘language detective’ and ‘interpreter’!

    By modelling the correct, first-person phrase right after the echo, parents/caregivers are teaching a child how to break down the ‘chunk’ and use the individual words functionally. They are showing their child: ‘I heard you. Your communication makes sense to me.’

    This strategy is a game-changer because it:

    1. Validates the child’s communication: It honours the child’s natural way of learning language, which boosts their confidence and willingness to communicate.
    2. Facilitates language development: It provides the child with the next step—a meaningful, functional phrase—to move them from repeating language to generating their own spontaneous sentences.

    Look at the child’s face again in the video. When his dad acknowledges and interprets his communication, you see that spark of joy and connection—that’s the moment when true, functional language learning happens!

    Ready to unlock the potential in your family’s story time? Contact me to learn more about our parent coaching programs.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.
    2

