Strategies to support children with eating difficulties

| |

where the cause is NOT a swallowing problem, but we are having a “fussy eater” in the family, seeming for no obvious reason

When parents have a child who find mealtimes or eating difficult, it can put pressure on the whole family dynamics. Once we have observed a child’s eating and drinking skills and found that they are not swallowing impaired, but are for want of a better word “fussy” or “picky”, we can then start to look at what might be underpinning the food aversions/picky eating/food avoidance. Two of the main questions parents have (of course) are:

  • ‘is my child getting the right nutrition?’
  • ‘how can I have less anxiety-provoking and stressful mealtimes?’

We all tend to have an image in our minds about the ‘perfect mealtime’, and how mealtimes ‘should’ be. Speech and Language Therapists with a Feeding Specialism are the perfect professionals to help you unpick feeding issues. We are trained to look at swallowing and oral skills and we also know a lot about feeding behaviours and sensory difficulties which could be causing your child’s eating avoidance.

Here are some strategies that can support children with their eating:

  1. Create and maintain a mealtime culture that suits your home and lifestyle. Then stick to that. We all need some routine in our lives to thrive. Mealtimes are no different. It might be that you eat in the same place for every meal, with the same knives and forks, concentrating on maintaining good posture. Children learn by repetition so the more familiar it is, the easier they will find it. In the physical sense, our bodies also need preparing for food, regardless of whether we are eating with our mouths or we are tube-fed. We want every child to connect all the dots of the process. It starts with their eyes, noses, expectations, memories of past experiences, feelings and then finally their mouths….
  2. Be an excellent role model. Children learn through watching others, so your child will be observing you without you knowing. Ensure that you are positive about the food you are all eating, and talk about how delicious, tasty, juicy, and yummy the foods are. Make the atmosphere around the dinner table light hearted. Even though you are secretly stressed about your child not eating, try and not show this. Instead pick a topic or put on some nice music, or talk about something your child might be interested in, and try and avoid coercing your child to eat. Leave small finger foods on their plates and have a range of foods available on the table so that your child can see that everyone is eating a range of foods and enjoying them.
  3. Use positive reinforcement. Try and think of mealtimes as fun and motivating. Children who are happy will likely be more inclined to try foods and take part in family mealtimes. Reward all interactions around food, so if your child merely touches a new food then praise this behaviour. Or if your child licks a food just once, again make a nice comment and praise your child for touching and licking the food. The takeaway here is to try and keep all messages positive around food.
  4. Keep offering all types of food. What often happens is that parents stop serving foods they know will not be eaten. This makes sense in a way; we don’t want wastage! However, try and keep the doors open and re-offer all types of foods, even the ones that your child has not wanted in the past. Try and give your child one food they will like and one food they have tasted before and liked before, even a little, and then one new food to try. So, your child always has something to fall back on and they can join in with eating. But they can also try (or at least look at and think about trying) other foods that you and perhaps the siblings are eating.

Take a look at this website, I find it very helpful in showing parents what types of foods and how big a portion to offer

Have a go and try and implement some of the ideas above, and should you get stuck please get in touch!


Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.


0

Similar Posts

  • · ·

    Support your autistic child’s communication by learning the stages of Gestalt Language Processing

    If your child is using echolalia and/or has a diagnosis of autism, then your child’s way of processing language is most likely different to the classic way children typically learn language. We call this process Natural Language Acquisition or Gestalt Language Processing.

    Speech Therpaist in London
    Step by Step guide to Gestalt Learning

    Let’s explore the following stages of Gestalt Processing:

    Stage 1: communicative use of whole language gestalts

    (e.g., “let’s get out of here”)

    Children and young people in this stage use echolalia. They need to hear more gestalts or scripts. So, your job is to model, model, model and to use functional language that your child can repeat back.

    Stage 2: mitigated into chunks and re-combining these chunks

    (e.g., “let’s get” + “some more”) and (e.g., “let’s get” + “out of here”)

    This is when you take parts of gestalts or phrases and then combine it with other parts.

    Stage 3: further mitigation (single words recombining words, formulating two-word phrases)

    (e.g., “get…more”)

    They are going beyond their gestalts. Furthermore, they may begin to label different objects.

    Stage 4: formulating first sentences

    (e.g., “let’s get more toys”)

    You may see more grammatical errors during this phase as they are creating unique sentences. Please don’t worry about this, it means they are playing and experimenting with language. As communication partners, you could model the correct form of the sentence.

    Stages 5 & 6: formulating more complex sentences

    (e.g., “how long do you want to play inside for?”)

    You can see that language learning is a process, that is trialled and tested, used in different contexts for children to be able to learn and use language appropriately.

    My next blog will give you activities ideas and how you might use them specifically with a Gestalt Language Processor.

    Remember early intervention is vital. So, if you have any concerns, please seek the advice of a Speech and Language Therapist.

    Contact me, Specialist Speech and Language Therapist Sonja here.

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • ·

    The great air debate: How different swallowing patterns impact breastfeeding and reflux

    The great air debate

    As a Speech and Language Therapist specialising in infant feeding, I often hear from worried mums describing their breastfed baby’s fussiness. ‘My baby is so burpy and gassy,’ ‘might it be reflux?’ or ‘she just seems uncomfortable after every feed’. While these concerns are incredibly valid and distressing for both baby and mum (and dads!), the underlying cause isn’t always what you might think. Often, the culprit isn’t primarily a digestive issue, but rather a mechanical one: how effectively your baby is managing air during feeding.

    Many parents are told their baby has ‘colic’ or ‘reflux’ and are offered solutions that don’t quite hit the mark because they overlook a fundamental aspect of feeding: the suck-swallow-breathe sequence. Understanding this intricate dance can be the key to unlocking a calmer, happier feeding experience for your baby and you.

    Understanding the suck-swallow-breathe sequence

    Your baby’s mouth, tongue, jaw, and throat muscles work together in a precise rhythm like a beautifully orchestrated symphony. First your baby draws milk, then swallows it, and then takes a breath, all without interruption. This is the ideal suck-swallow-breathe (SSB) sequence.

    When the SSB sequence functions optimally, a baby latches deeply, creates good suction, draws milk, swallows efficiently, and then pauses just long enough to take a gentle breath before the next suck. This smooth, coordinated process minimises the amount of air swallowed.

    However, for various reasons (it could be a shallow latch, oral motor challenges, an uncoordinated suck, or even an overly fast milk flow) this sequence can get a bit out of sync. Instead of a smooth rhythm, you might see:

    • Suck-suck-swallow-gasp!: Too much air pulled in with the swallow.
    • Rapid, shallow sucking followed by gulping: Inefficient milk transfer and air intake.
    • Clicking noises during feeding: Loss of suction, indicating air entry.
    • Frequent detaching and re-latching: Often to ‘catch a breath’ or because of discomfort.

    Each of these patterns can lead to increased air intake.

    The root cause: Air trapping leading to a gassy breastfed baby

    When a baby swallows too much air during a feed, that air must go somewhere. It builds up in the stomach, causing bloating, discomfort, and often leads to the familiar reflux-like symptoms parents describe: arching, spitting up, burping excessively, or simply appearing distressed.

    It’s a common misconception that all gassiness or reflux symptoms in a breastfed baby are due to something in the mother’s diet or a genuine digestive disorder. While these can be factors, as an SLT, we first look at the mechanics of the feed. If a baby is constantly struggling to maintain a seal, sucking inefficiently, or having to gulp to keep up with flow, he or she is inevitably swallowing air. This air then creates pressure, which can push milk back up (silent reflux) or out (visible reflux).

    Think of it like trying to drink through a straw with a hole in it. You’re sucking, but you’re also pulling in air, making it harder to get the liquid and leaving you with more bubbles in your stomach.

    Why mechanical speech therapy assessment is key

    This is where the distinction between a medical diagnosis (true gastro oesophageal reflux disease or GORD) and a functional feeding challenge becomes critical. A paediatrician will assess for medical causes and may prescribe medication to reduce stomach acid. This can be appropriate for severe cases of GORD.

    However, if the primary issue is air being trapped due to a suboptimal suck-swallow pattern, medication only treats the symptom (acid burning) and not the root cause (air intake). This is precisely where a Speech and Language Therapist specialising in infant feeding comes in.

    My role is to meticulously observe and assess your baby’s oral motor skills, latch, tongue function, and the efficiency of their SSB sequence. I look for subtle signs of inefficiency that contribute to excessive air swallowing.

    • Is the tongue elevating correctly to create suction?
    • Is the jaw stable, or is it excessively moving?
    • Is the latch deep enough to prevent air leaks?
    • Can the baby coordinate suck, swallow, and breathe without gasping?

    By identifying these mechanical challenges, I can then implement targeted strategies to improve feeding efficiency and reduce air intake, often leading to a significant reduction in reflux-like symptoms and overall discomfort.

    Strategies to optimise air management during breastfeeding

    The good news is that many babies can learn to feed more efficiently with the right support. Here are some general strategies we might explore:

    1. Optimise latch and position: A deep, asymmetric latch is crucial. Experiment with different positions that allow for a deeper latch and better head/neck alignment, such as laid-back feeding or upright positions.
    2. Paced feeding (even at the breast): If your milk flow is very fast, consider removing your baby from the breast briefly if you hear excessive gulping or see him or her struggling to breathe. This allows him or her to catch up and manage the flow.
    3. Support the jaw and cheeks: Sometimes, gentle support to the baby’s jaw or cheeks can help them maintain a more stable, efficient suck. I can demonstrate specific techniques for this.
    4. Burping effectively: While burping won’t get rid of all swallowed air, upright burping positions and gentle back rubs can help release some of it.
    5. Pre-feed oral preparation: Gentle oral massage or stretches before a feed can sometimes ‘wake up’ the oral muscles and improve coordination.

    Addressing the ‘Great Air Debate’ isn’t about blaming anyone; it’s about empowering parents with a deeper understanding of their baby’s feeding mechanics. By focusing on the how, not just the what, we can often resolve persistent feeding challenges, reduce discomfort, and make breastfeeding a more joyful, peaceful experience for both you and your little one.

    If you suspect your baby’s gassiness or reflux symptoms are related to how they are managing air during feeds, don’t hesitate to reach out for a specialist assessment.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    2
  • · ·

    Navigating the exciting 9–18 months journey: Your baby’s communication milestones

    Between 9 and 18 months, your little one undergoes a remarkable transformation, blossoming from a curious explorer into a budding communicator. This period is filled with exciting milestones in speech, language, and social development. Let’s delve into what you can expect.

    9–12 months: The world opens up

    Communication takes flight

    • Babbling becomes more complex with a wider range of sounds. By babbling we mean syllables like: pa ga ka ma da and then ‘baba’ gohgoh’. First we hear one and two syllables together and then longer and longer strings! This is so exciting!
    • First words! One day around the 12 months–14 months mark we hear a first word! My older son’s first word was ‘Licht’ which is the German word for ‘light’ as literally every time I carried him along the corridors in our home, I pointed out the light switches to him and turned them off and on a few times. And each time I said ‘Licht!’ and it stuck! PS: sadly I cannot remember what my younger son’s first word was… poor second and third babies they just have to muddle along and call loudly to get noticed!
    • Understanding grows! Baby now understands simple instructions like ‘where is your ball’ and responds by looking to the ball across the room!

    Social butterflies

    • Your baby now starts to show interest in other children, and may try to copy their actions. Now we are getting proper traction with simple social games like peek-a-boo and patty-cake. Whilst your baby is generally interested in other people and children he or she may show separation anxiety when mum or dad or other familiar person suddenly leaves the room and they feel alone with strangers.

    Fine motor skills

    • Pincer grasp develops. This is where your child puts an index finger to the thumb in order to pick up of small objects, hold them and transfer them to either a box, back on the floor or into the other hand.
    • Your baby may start to explore objects by banging, shaking, and mouthing.

    12–15 months: Words are taking shape

    • Language explosion: From our early words we now suddenly see baby’s vocabulary expanding, with new words added each week. I would highly recommend parents keep a little journal of all the words they hear. If nothing else this is a wonderful aide-memoire for years down the road when you might like to reminisce about the first ten words. I promise you otherwise you won’t recall! (especially for second and third babies; I would do this now, had I the time again).
    • Understanding grows:
      • By about 15 months our baby can follow simple two-step instructions like ‘Go get your shoes and bring them here.’
      • Begins to understand the concept of ‘no.’ and that’s a very useful thing. Though before you breathe a sigh of relief… your toddler may well show you that he is understanding a ‘no’ though he may not stop doing what he is doing or come down off the table!
    • Playtime gets interactive:
      • Now we engage in more complex play, such as stacking blocks, pretending to eat with a spoon, and imitating actions.
      • Many toddlers now start showing an interest in picture books.

    15–18 months: Communication blossoms

    • Words combine: Towards 18 months or around about then your toddler may start to put two words together, such as ‘more milk’ or ‘bye-bye dada.’
    • Gestures and sounds: Now we also use gestures to communicate, such as pointing, shaking head ‘no,’ and waving ‘bye-bye.’
    • Exploration and curiosity:
      • Your toddler is now EVERYWHERE! Turn your back and he or she is gone! Your toddler now shows a strong sense of curiosity and explores their environment with enthusiasm.
    • Copying
    • Look out for actions and gestures your toddler will copy such as clapping hands or patting a cushion or banging a spoon on the table .

    Remember

    • Every child develops at his or her own pace.
    • These are just general guidelines, and some children may reach certain milestones earlier or later than others.
    • If you have any concerns about your child’s development, please consult with your speech and language therapist. We are always keen to hear from parents and happy to help promote all those lovely early skills.

    General tips to encourage communication if you feel your child needs a little more help

    • Talk, talk, talk! Engage in frequent chatting with your child.
    • Listen to your child: Allow for periods of silence when playing with your child to allow them to say something or make sounds which you can then copy and respond to.
    • Read aloud regularly. Use books with simple words and pictures.
    • Play interactive games: Hickory Dickory Dock, Row Row the boat, Old McDonalds, 5 little monkeys jumping on the bed, chasing and catching, tickling games.
    • Respond to your child’s babbling and gestures. You can copy them or if your toddler says long strings of babbling you cannot understand you could just say: ‘Oh ok!? ‘yes that’s great!’ ‘who knew!’ ‘wow you’ve got much to say!’ as if you understood.
    • Limit screen time or if your child is very passionate about watching clips then sit and watch with your child so that you can see what is the best bit, which songs they like the best and what sort of phrases they love hearing.

    This exciting period of rapid growth and development is a precious time for both you and your child.

    By providing a loving, stimulating, and responsive environment, you will naturally nurture their communication skills! Any more questions, please get in touch!

    Sonja McGeachie

    Early Intervention Speech and Language Therapist

    Feeding and Dysphagia (Swallowing) Specialist The London Speech and Feeding Practice

    The London Speech and Feeding Practice


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • ·

    Correcting a lisp

    Correcting A Lisp

    This is a surprisingly common speech error and it can be corrected really well in my experience. I have helped lots of children of all ages learn how to control their tongue movements and produce clear, sharp /S/ sounds and good /SH/ sounds.

    Initial consideration

    There are some factors which need to be considered before we can dive into therapy proper and these are they, in a nutshell:

    1. The student is not currently displaying negative oral habits such as thumb sucking or excessive sucking on clothing. This is because thumb sucking exerts pressure on the teeth and therefore can, over time, push teeth out of their natural order/position.
    2. The student does not have a restricted lingual frenulum or tongue tie which can cause at times restricted movements of the tongue (pending on how tight the frenulum is attaching the tongue to the base of the oral cavity); equally a labial frenulum or lip-tie can restrict lip movement and therefore physically restrict good speech sound production.
    3. The student does not have enlarged tonsils as they can sometimes push a tongue forward and also cause open mouth posture and open mouth breathing.
    4. The student’s motivation to change their speech pattern is high. (this is an important factor though with younger students I can get round this with a lot of fun games and good parental involvement!)

    When I do an Oral Assessment of my student these are the first factors I want to look at and consider. Often I will refer to other agencies such as Orthodontists, dentists or ENT specialists to advise and help with some of these factors before we can get going. However, there are strategies that we can work on almost straight away.

    Most of my Lisp students present with an open mouth posture: that is where the student has their mouth always slightly open for breathing. Over time the tongue starts to fall forward and rests on the front teeth or the bottom lip instead of finding a comfortable resting place either at the alveolar ridge (the bumpy spot behind the upper front teeth) or, alternatively, resting at the bottom of the mouth behind the lower front teeth.

    Another common problem is that the tongue is not moving independently from the jaw and so is reluctant to pull back or lift up inside the mouth as the tongue is guided in movement by the jaw.

    Combine those two factors and your tongue is not pulling back, or lifting up or doing very much at all without the jaw moving as well. This makes for unclear speech sounds, especially all the sounds we make at the front with our tongue or with our lips: /B/ /P/ /L/ /N/ and of course /S/ and /SH/ are particularly hard to make. We often also struggle with the /Y/ sound so ‘LELLOW’ instead of ‘yellow’.

    Do not fear!

    But no fear, these problems can be treated over time for sure! We often start with lip, tongue, and jaw exercises that help to move the tongue independently from the Jaw, our student learns that the tongue is a muscle and can be trained to do amazing acrobatic things in the mouth! WOW! It can actually pull back, lift up, and come down again all on its own!

    We work on breathing, holding our breath for a bit then pushing it out and then holding it again.

    And when it comes to the actual /S/ sound I often try and go a NEW route bypassing the Snake-Sound route if that is what had previously been tried and failed so that we can create completely new sound patterns in our brain and think about our sounds in a completely new way.

    We then work on producing the sound /S/ on its own for a bit, at the end of words, then on either side of complimentary sounds, for instance : ‘EASY” – the sound patterns here are EEE-S–EE : the /EEE/ sound is complimentary to the /S/ sound as the tongue is at the right hight for the /S/ already once you have it in place for /EEE/ -……see?! EASY!

    And gradually we work towards saying the /S/ sound clearly at the front of short words, then phrases and then sentences.

    The process takes some time and it depends on how ready the student is. This varies of course hugely so I can never promise the exact number of sessions we will take to get that Lisp fixed. A lot depends on home practice in between sessions, and this is of course crucial to all therapy! Every day 15-20 mins practice is a good average time to aim for and when this is done it shortens the therapy block drastically.

    I always give plenty of home work so there is never a chance of it getting boring or there being “nothing to do”!

    Do contact me. I really enjoy working with this type of student and get a great kick out of FIXING THAT LISP!


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • · ·

    Why auditory memory matters (especially for little ones!)

    Why auditory memory matters (especially for little ones!)

    Have you ever stopped to think about how we learn to speak, understand, and communicate effectively? It’s a complex dance of various cognitive skills, and one often overlooked but absolutely crucial player in this orchestra is auditory memory. It’s not just about remembering sounds. It’s about remembering sequences of sounds, which is fundamental to language development.

    What exactly is auditory memory?

    At its core, auditory memory is our ability to take in, process, store, and recall information that we hear. Think of it as your brain’s internal recording studio. When someone speaks to you, your auditory memory is busy at work, capturing the individual sounds, the order in which they appear, and the rhythm and intonation of the words. This isn’t just for long-term recall; it’s also vital for working auditory memory, which allows us to hold onto a small amount of auditory information for a short period, just long enough to make sense of it.

    For speech and language, auditory memory is essential for:

    • Understanding spoken language: To comprehend a sentence, we need to remember the beginning of the sentence by the time we hear the end.
    • Following instructions: Remembering a sequence of commands relies heavily on auditory memory.
    • Learning new words: We hear a word, remember its sound, and connect it to its meaning.
    • Developing phonological awareness: This is the ability to recognise and manipulate the sounds in spoken language, a critical precursor to reading. Auditory memory helps children distinguish between similar-sounding words (e.g., ‘cat’ vs. ‘bat’) and segment words into individual sounds.
    • Producing clear speech: To articulate words correctly, we need to recall the precise sequence of sounds that make up that word.
    • Developing conversational skills: Remembering what was just said helps us formulate appropriate responses.

    When auditory memory falls short: The impact on speech

    When auditory memory is poor, particularly in young children, the ripple effects on speech and language development can be significant. Children might struggle with:

    • Following multi-step directions: ‘Put on your shoes, get your coat, and meet me at the door’ can become an overwhelming jumble of sounds.
    • Learning new vocabulary: They might hear a new word repeatedly but struggle to retain its sound pattern, making it difficult to recognise or use later.
    • Understanding stories or conversations: Missing key details or losing the thread of a narrative because they can’t hold enough information in their working memory.
    • Developing phonological skills: Difficulty with rhyming, identifying initial sounds in words, or blending sounds together to form words, which can impact early literacy.
    • Speech production: They might mispronounce words, omit sounds, or struggle with the correct sequencing of sounds within words.
    • Social communication: Difficulty participating in group discussions, remembering names, or recalling what their peers have said.
    • Academic performance: Auditory memory challenges can impact a child’s ability to learn in a classroom setting, where much of the instruction is delivered verbally.

    It’s important to note that poor auditory memory isn’t a sign of low intelligence, but rather a specific processing challenge that can be addressed with targeted support.

    Nurturing auditory memory in under 5s: Preparing for schooling

    The good news is that auditory memory is a skill that can be strengthened and developed, especially during the crucial early years. For children under five, laying a strong foundation in auditory memory is an invaluable gift as they prepare for the demands of formal schooling. Here’s what we can do to help:

    1. Read aloud regularly: This is perhaps one of the most powerful tools. As you read, encourage your child to listen for specific words, predict what happens next, and retell parts of the story. Vary your voice, use different intonations, and pause to emphasise key words.
    2. Play auditory memory games:
      • ‘Simon says’: This classic game is fantastic for following multi-step instructions. Start with one command and gradually increase the number.
      • ‘I Spy’ with sounds: Instead of colours, describe sounds. ‘I spy with my little ear something that goes “moo”.’
      • Rhyming games: Sing rhyming songs, read rhyming books, and encourage your child to come up with words that rhyme.
      • Sound matching: Use everyday objects to make sounds (e.g., shaking keys, tapping a spoon) and have your child identify or match them.
      • ‘Memory chain’: Start a sentence and have your child add to it, remembering everything that came before: ‘I went to the market and bought an apple.’ ‘I went to the market and bought an apple and a banana.’
    3. Sing songs and nursery rhymes: Repetitive songs and nursery rhymes are excellent for developing auditory memory, rhythm, and phonological awareness. The predictable patterns help children anticipate and remember sequences of sounds and words.
    4. Give multi-step instructions (and praise!): Start with two-step instructions and gradually increase the complexity as your child’s skills improve. Always give positive reinforcement when they succeed. ‘Please pick up the red block and put it in the box.’
    5. Engage in active listening: Model good listening skills yourself. When your child is speaking, give them your full attention. Ask clarifying questions to encourage them to elaborate and organise their thoughts.
    6. Reduce background noise: A quiet environment makes it easier for young children to focus on auditory information. Minimise distractions like TV or loud music during activities that require listening.
    7. Use visual cues: While we’re focusing on auditory memory, sometimes pairing auditory information with visual cues can be helpful, especially initially. For example, when giving instructions, demonstrate the action as you say it.
    8. Be patient and consistent: Developing auditory memory takes time and consistent practice. Celebrate small victories and create a playful, supportive environment for learning.

    By actively engaging in these strategies, we can empower our youngest learners to build robust auditory memory skills, setting them up for success not only in speech and language development but also in their overall academic journey. It’s an investment that truly pays dividends in their future communication and learning abilities.

    Any comments or if you need help and support with your child’s speech please do not hesitate to get in touch with me: simply fill out the contact form here on the website. I endeavour to reply within 48 hours.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • Could mouth breathing be affecting your child’s speech, sleep and development?

    Could mouth breathing be affecting your child's speech, sleep and development?

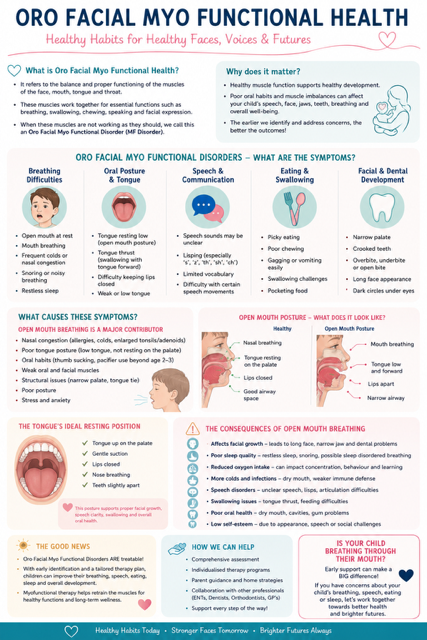
    Understanding Orofacial Myofunctional Disorders (OMDs)

    Many parents contact me at London Speech and Feeding because they are worried about their child’s speech. Perhaps their child is difficult to understand, has a persistent lisp, struggles with feeding, snores at night, or always seems to have their mouth open.

    What many families don’t realise is that these concerns may all be connected.

    Increasingly, research and clinical experience are highlighting the important role of Orofacial Myofunctional Health, the way the muscles of the face, mouth, tongue and airway work together to support breathing, eating, sleeping and communication.

    When these muscles are not functioning optimally, children may develop what are known as Orofacial Myofunctional Disorders (OMDs).

    What Is Orofacial Myofunctional Health?

    Orofacial Myofunctional Health refers to the healthy function and coordination of the:

    • lips
    • tongue
    • jaw
    • cheeks
    • facial muscles
    • airway.

    These structures play a vital role in:

    • breathing
    • swallowing
    • chewing
    • speaking
    • facial growth
    • dental development
    • sleep quality.

    When everything is working well, the lips remain gently closed at rest, breathing occurs through the nose, and the tongue rests against the roof of the mouth.

    This seemingly simple posture has a profound influence on how a child’s face, teeth and airway develop.

    What is an Orofacial Myofunctional Disorder?

    An Orofacial Myofunctional Disorder occurs when there is an abnormal pattern of muscle function involving the face, mouth, tongue or airway.

    Children with OMDs may experience difficulties with:

    • speech
    • feeding
    • swallowing
    • sleep
    • breathing
    • dental development
    • facial growth.

    In many cases, these difficulties are linked to chronic mouth breathing.

    Signs your child may have an Orofacial Myofunctional Disorder

    Breathing and sleep signs

    • mouth open at rest
    • mouth breathing during the day
    • snoring
    • noisy breathing
    • restless sleep
    • frequent waking
    • dark circles under the eyes
    • chronic congestion
    • fatigue despite a full night’s sleep.

    Speech signs

    • lisping
    • unclear speech
    • distorted speech sounds
    • difficulty producing certain sounds
    • persistent articulation difficulties
    • reduced speech intelligibility.

    Feeding and swallowing signs

    • picky eating
    • messy eating
    • food remaining in the cheeks
    • gagging easily
    • difficulty chewing
    • long mealtimes
    • tongue thrust swallowing.

    Facial and dental signs

    • narrow palate
    • crowded teeth
    • open bite
    • overbite
    • underbite
    • long face appearance
    • receding chin
    • poor lip seal.

    If several of these signs sound familiar, a comprehensive assessment may be worthwhile.

    Why does mouth breathing matter?

    Many parents assume mouth breathing is simply a habit.

    In reality, mouth breathing is often a symptom that something is preventing efficient nasal breathing.

    Common causes include:

    • enlarged tonsils
    • enlarged adenoids
    • allergies
    • chronic nasal congestion
    • recurrent infections
    • structural airway differences
    • tongue tie
    • prolonged dummy use
    • thumb sucking
    • poor oral posture.

    When nasal breathing becomes difficult, children naturally begin breathing through their mouths.

    Over time, this can affect how the face, jaws and airway develop.

    What does healthy oral posture look like?

    Healthy oral posture is surprisingly simple:

    • lips
      • gently closed
    • tongue
      • resting against the roof of the mouth
    • teeth
      • slightly apart
    • breathing
      • through the nose.

    This posture helps guide healthy jaw growth, facial development and airway formation.

    Think of the tongue as a natural orthodontic support system. When it rests in the correct position, it helps shape the upper jaw and supports healthy facial growth.

    The consequences of chronic mouth breathing

    1. Speech difficulties

    Children who breathe through their mouths often have altered tongue posture and reduced oral stability.

    This can contribute to:

    • lisping
    • distorted sounds
    • reduced speech clarity
    • difficulty learning new speech sounds.

    2. Feeding and swallowing difficulties

    A low tongue posture may affect:

    • chewing efficiency
    • swallowing patterns
    • food management
    • oral motor coordination.

    Many children develop a tongue thrust swallow, where the tongue pushes forward instead of moving efficiently during swallowing.

    3. Poor sleep quality

    Mouth breathing can contribute to:

    • snoring
    • restless sleep
    • frequent waking
    • daytime fatigue
    • reduced concentration.

    Poor sleep can have a significant impact on learning, behaviour and emotional regulation.

    4. Changes to facial growth

    Over time, chronic mouth breathing may influence:

    • jaw development
    • facial proportions
    • dental alignment
    • airway size.

    This can result in:

    • narrow palates
    • crowded teeth
    • long facial appearance
    • increased orthodontic needs.

    5. Oral health concerns

    The nose acts as a natural filter and humidifier.

    When children breathe through their mouths:

    • The mouth becomes dry.
    • Saliva protection is reduced.
    • Risk of tooth decay increases.
    • Gum health may be affected.

    Why this matters for speech therapy

    Speech does not develop in isolation.

    The tongue, lips, jaw and airway work together to support clear communication.

    At London Speech and Feeding, we look beyond speech sounds alone.

    A child who presents with:

    • persistent speech difficulties
    • lisping
    • feeding challenges
    • open mouth posture
    • snoring
    • poor sleep

    may benefit from an assessment that explores underlying orofacial myofunctional factors.

    Addressing these foundations can often support more effective progress in speech and feeding therapy.

    How London Speech and Feeding can help

    A comprehensive assessment may include observation of:

    • breathing patterns
    • lip posture
    • tongue posture
    • swallowing function
    • feeding skills
    • speech sound development
    • sleep concerns
    • oral structures.

    Where appropriate, recommendations may include:

    • orofacial myofunctional therapy
    • speech therapy
    • feeding therapy
    • home programmes
    • ENT referral
    • orthodontic referral
    • collaborative multidisciplinary support.

    The good news

    Orofacial Myofunctional Disorders are often highly treatable when identified early.

    Supporting healthy breathing, tongue posture and oral muscle function can positively influence:

    If your child regularly breathes through their mouth, snores, struggles with speech clarity or has feeding difficulties, a specialist assessment may help identify the underlying cause.

    • speech clarity
    • feeding skills
    • sleep quality
    • facial growth
    • dental development
    • overall wellbeing.

    At London Speech and Feeding, we are passionate about looking beyond symptoms and understanding the whole child. Contact me!

    Sometimes the key to clearer speech starts with a simple question:

    ‘Is my child breathing through their nose?’

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.

    Frequently Asked Questions

    Can mouth breathing cause speech problems?

    Yes. Mouth breathing can alter tongue posture, lip strength and oral stability, which may contribute to articulation difficulties and lisps.

    Should I be worried if my child snores?

    Regular snoring is not considered normal in children and may indicate airway obstruction or sleep-disordered breathing.

    Can enlarged tonsils affect speech?

    Yes. Enlarged tonsils may affect resonance, tongue positioning, swallowing and breathing patterns.

    What age can children be assessed?

    Children of all ages can be assessed if parents have concerns about speech, feeding, breathing or oral development.

    What is Orofacial Myofunctional Therapy?

    Orofacial Myofunctional Therapy focuses on improving breathing patterns, tongue posture, lip seal and oral muscle function to support overall health and development.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3