Managing mealtime sensory overload at holiday gatherings: Supporting children with allergies and feeding differences

| | | |
Managing mealtime sensory overload at holiday gatherings: Supporting children with allergies and feeding differences

Holiday meals are meant to be joyful and something we all look forward to. But for many children and their families, these occasions can be overwhelming and be the cause of dread and worry. The combination of new smells, unfamiliar foods, loud environments, social expectations, and allergy anxieties can quickly turn what should be a festive time into a stressful one.

For parents of children with sensory processing differences, selective eating challenges, or food allergies, holiday gatherings often require careful planning and a big dose of tolerance and compassion. The good news is that with awareness and a few gentle strategies, you can support your child to feel safe, regulated, and included during festive meals without pressure, tears, or discomfort.

Let’s explore how to make holiday mealtimes calmer, safer, and more connected this season.

🎄 Why holiday meals feel so overwhelming

Holiday gatherings usually combine several sensory triggers all at once:

  • Noisy, chaotic rooms
  • Strong smells from a mix of foods we don’t normally cook
  • Multiple conversations happening at once
  • Bright lights, Christmas décor, flickering candles
  • Unfamiliar foods with unexpected textures
  • Expectations to ‘try everything’ or ‘enjoy it’s sooo good!’
  • New environments, seating arrangements, or routines

For children with sensory sensitivities, this can feel like a tidal wave of input. Research shows that children who are sensory-sensitive often have heightened responses to smell, taste, and texture, which may lead to avoidance or distress at mealtimes (Cermak, Curtin, & Bandini, 2010).

Add food allergies into the picture and anxiety increases even further for both children and parents. A 2020 study by DunnGalvin et al. found that children with food allergies experience significantly higher stress in shared eating environments, especially when food preparation or contamination risk is hard to control.

So, if your child becomes tearful, shuts down, or refuses to sit at the festive table, it isn’t ‘bad behaviour.’ It’s sensory overload, heightened vigilance, or discomfort communicating through their body.

🌟 Preparing your child for a calmer festive meal

Preparation is especially important for sensory-sensitive or allergy-aware children. Here’s how to set them up for success:

1. Offer predictability through previewing

Before the event, show your child pictures of:

  • where you’re going
  • who will be there
  • the types of foods that might be served
  • where they might sit

A visual schedule or social story can help reduce anxiety and give your child a sense of control.

2. Pack safe foods without apology

If your child has allergies or selective eating, bring:

  • ‘Safe foods’ you know they will eat
  • Backup snacks
  • A separate (their own) plate, if needed
  • Emergency medication

Announce clear, firm boundaries such as:

‘Ok people, these are Jamie’s safe foods — we’ll stick with these today.’ This will help relatives understand without pressure or judgement.

3. Choose seating that supports sensory regulation

If possible, seat your child:

  • at the end of the table
  • near a familiar adult
  • away from the kitchen (strong smells)
  • away from noise clusters
  • give them their favourite toy or fidget whilst waiting

Let them take breaks when needed. This isn’t ‘rude,’ it’s self-regulation.

🍽️ Supporting children during the meal

1. Focus on connection, not consumption

The holidays are not the time to expand your child’s food range. Keeping mealtimes low-pressure actually supports long-term progress.

In fact, the research is clear: pressuring children to eat decreases acceptance and increases refusal (Galloway et al., 2006).

So instead of ‘Just try it!’ try:

  • ‘You don’t have to eat it, you can look at it.’
  • ‘You’re in charge of what goes in your mouth.’
  • ‘You can keep your safe foods on your plate.’

2. Protect your child’s allergy safety

Holiday meals often include:

  • cross-contamination risks
  • shared utensils
  • buffets
  • homemade dishes without ingredient lists

Use gentle but firm scripts:

  • ‘Because of Ellie’s allergies, we’ll keep her plate separate.’
  • ‘We’ll serve her food ourselves to make sure she stays safe.’

Confidence in your boundary helps others respect it.

3. Manage sensory load in real time

Offer:

  • headphones
  • a small chew or fidget toy
  • a designated ‘calm corner’
  • time outside for fresh air
  • a predictable signal for breaks (e.g., a hand squeeze or card)

Remember, sensory regulation is healthcare, not ‘giving in.’

4. Model calm eating

Children learn most from watching.

Slow, happy bites and relaxed facial expressions tell the nervous system: ‘This environment is safe’.

💛 What to say to well-meaning relatives

Families often have big feelings about food. You can prepare nice phrases like:

  • ‘We’re focusing on helping him feel safe around food today.’
  • ‘She has allergies, so we’re sticking to our plan.’
  • ‘We’re avoiding pressure because it helps him eat better long term.’
  • ‘We’re celebrating together, eating is not the goal today.’

Setting expectations ahead of time can reduce awkward moments later.

🎁 The bigger picture: It’s about safety, not ‘picky eating’

Children with allergies, sensory differences, or feeding challenges aren’t trying to be difficult. They are trying to stay safe, regulated, and comfortable.

Your calm presence, gentle boundaries, and preparation create the conditions for a holiday that feels peaceful, not pressured.

Sonja McGeachie

Highly Specialist Speech and Language Therapist

Owner of The London Speech and Feeding Practice.


Health Professions Council registered
Royal College of Speech & Language Therapists Member
Member of ASLTIP

Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

📚Research References

Cermak, S. A., Curtin, C., & Bandini, L. G. (2010). Food selectivity and sensory sensitivity in children with autism spectrum disorders. Journal of the American Dietetic Association, 110(2), 238–246.

DunnGalvin, A. et al. (2020). APPEAL-2: A pan-European qualitative study to explore the burden of peanut-allergic children, teenagers and their caregivers. Clinical & Experimental Allergy, 50(11), 1238–1248.

Galloway, A. T., Fiorito, L. M., Francis, L. A., & Birch, L. L. (2006). ‘Finish your soup!’ Counterproductive effects of pressuring children to eat on intake and affect. Appetite, 46(3), 318–323.

2

Similar Posts

  • ·

    What Is Echolalia And Does It Have A Function? How Can Speech Therapy Help With Echolalia?

    What Is Echolalia And Does It Have A Function? How Can Speech Therapy Help With Echolalia?

    Echolalia is a term used when assessing or treating children with Autism. The term refers to the repetition or echoing of utterances, either our own or others’. It can also be echoing phrases heard on television, advertising jingles or catchy repeat phrases used in tv programmes or nursery rhymes and songs. Whilst we all use echolalia occasionally and it can be observed in typically developing children, we tend not to see/hear it beyond the age of 2.5 years old. Children with ASD, however, do use echolalia often into late childhood.

    There are generally two types of Echolalia:

    Immediate echolalia

    Here the repeated phrases or words are produced immediately after someone has spoken the original words or within two conversational turns of the original utterance.

    Delayed echolalia

    The repeat echoing of the original utterance occurs sometime later, more than two conversational turns or with a much longer time delay. Due to the delay it can be hard to interpret the meaning of the echolalic utterance as it may refer to something that happened long ago and in a different context to the originally utterance.

    (Stiegler, 2015, Fay 1967, Blanc 2014)

    There are other unconventional speech behaviours which include:

    • Perseveration of Speech – persistent repetition of speech
    • Repetitive questioning – persisting even though answers were given
    • Vocalisations such as: humming, whistling, clicking, squealing etc.

    Much research has gone into the meaning and treatment of Echolalia and the following list consists of possible functions that have been identified:

    • Information sharing
    • Responding to answers
    • Labelling
    • Drawing attention to self
    • Protesting
    • Requesting
    • Giving instructions
    • Self-regulation, calming

    (Stiegler 2015, Prizant 1983)

    Echolalia does have a function and is part of the Gestalt Learning Process (where longer units of speech are memorised and then used as a whole without the individual words being meaningful).

    As a Speech and Language Therapist I promote sound and proven Intervention based on the Hanen Programme which helps provide a highly facilitative Interaction Style and I will tell you a bit more in my next blog how the “More Than Words” approach can help children with echolalia move through their Gestalt Learning into more analytic processing of language, grammar and meaning.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

  • · ·

    The picky eater’s plate: Introducing solids to toddlers with ARFID

    Designed by Freepik

    Mealtimes can be a battleground for parents of picky eaters, especially toddlers with Avoidant/Restrictive Food Intake Disorder (ARFID). I see a great number of toddlers with Autism traits and many of my clients are picky eaters from mild to severe. Take a look at my blog for an outline of what the issues are and how to try and help.

    ARFID goes beyond typical ‘picky eating’ and can significantly impact a child’s growth, nutrition, and social-emotional well-being. If your toddler is resistant to trying new foods or has a very limited diet, here are some strategies to navigate the introduction of solids:

    1. Understand ARFID:

    ARFID is a diagnosable eating disorder characterised by:

    • Limited food variety: Eating only a small range of foods, often with specific textures or colours.
    • Fear of new foods: Intense anxiety or aversion to trying unfamiliar foods.
    • Sensory sensitivities: Heightened sensitivity to taste, smell, texture, or appearance of food.
    • Lack of interest in eating: May show little interest in food or mealtimes.

    2. Seek professional guidance:

    • Paediatrician and/or gastroenterologist: Rule out any underlying medical conditions.
    • Registered dietitian: Assess nutritional needs and create a balanced meal plan.
    • Speech and language therapist (SLT): If oral-motor skills or sensory sensitivities are contributing to feeding difficulties.
    • Occupational therapist (OT): If sensory processing challenges are affecting mealtime behaviours.
    • Child psychologist: If anxiety or emotional factors are contributing to ARFID.

    3. Strategies for introducing solids:

    • Start small: Introduce one new food at a time, in small amounts, alongside familiar favourites.
    • Patience is key: It can take multiple exposures (up to 10–15 times!) for a child to accept a new food. Don’t give up!
    • Positive reinforcement: Praise and encouragement for any interaction with the new food, even just touching or smelling it.
    • No pressure: Avoid forcing or pressuring the child to eat. This can create negative associations with food.
    • Make it fun: Present food in playful ways, use cookie cutters for fun shapes, or involve the child in food preparation.
    • Sensory exploration: Encourage exploration of food through touch, smell, and sight before tasting.
    • Role modelling: Show the child that you enjoy eating a variety of foods.
    • Use fun utensils: your child might like characters from ‘Frozen’ or ‘Dinosaurs’ or ‘Diggers’ there are a host of character-based cutlery and cups/plates to be had. Also, I really rate these two items very highly they are so good so I want to share these with you. Both are available online. But warning: the cup is outrageously expensive as it comes from the United States and is sold by a small scale company. But I feel this is cup very worth trying, I have had good results with this.
    • Gradual desensitisation: Start with foods that are similar in texture or taste to accepted foods, then gradually introduce more challenging options.
    • Food chaining: Introduce new foods that are similar in taste, texture, or appearance to accepted foods.

    4. Mealtime Environment:

    • Positive and relaxed: Create a calm and enjoyable mealtime atmosphere.
    • No distractions: Minimise distractions like TV or toys.
    • Consistent schedule: Offer meals and snacks at regular times.
    • Child-sized portions: Offer small, manageable portions to avoid overwhelming the child.
    • Involve the child: Let the child choose their utensils, plate, or cup.

    5. Remember:

    • Every child is different: What works for one child may not work for another.
    • Progress takes time: Be patient and celebrate small victories.
    • Focus on the positive: Praise any positive interaction with food.
    • Seek support: Connect with other parents or support groups.

    Introducing solids to toddlers with ARFID can be challenging, but with patience, persistence, and professional guidance, you can help your child develop a healthier relationship with food.

    Get in touch with me via my contact form if you need support

    Sonja McGeachie

    Early Intervention Speech and Language Therapist

    Feeding and Dysphagia (Swallowing) Specialist The London Speech and Feeding Practice

    The London Speech and Feeding Practice


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • Could mouth breathing be affecting your child’s speech, sleep and development?

    Could mouth breathing be affecting your child's speech, sleep and development?

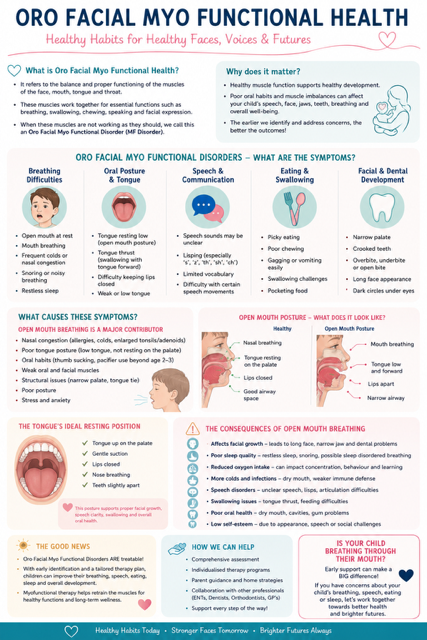
    Understanding Orofacial Myofunctional Disorders (OMDs)

    Many parents contact me at London Speech and Feeding because they are worried about their child’s speech. Perhaps their child is difficult to understand, has a persistent lisp, struggles with feeding, snores at night, or always seems to have their mouth open.

    What many families don’t realise is that these concerns may all be connected.

    Increasingly, research and clinical experience are highlighting the important role of Orofacial Myofunctional Health, the way the muscles of the face, mouth, tongue and airway work together to support breathing, eating, sleeping and communication.

    When these muscles are not functioning optimally, children may develop what are known as Orofacial Myofunctional Disorders (OMDs).

    What Is Orofacial Myofunctional Health?

    Orofacial Myofunctional Health refers to the healthy function and coordination of the:

    • lips
    • tongue
    • jaw
    • cheeks
    • facial muscles
    • airway.

    These structures play a vital role in:

    • breathing
    • swallowing
    • chewing
    • speaking
    • facial growth
    • dental development
    • sleep quality.

    When everything is working well, the lips remain gently closed at rest, breathing occurs through the nose, and the tongue rests against the roof of the mouth.

    This seemingly simple posture has a profound influence on how a child’s face, teeth and airway develop.

    What is an Orofacial Myofunctional Disorder?

    An Orofacial Myofunctional Disorder occurs when there is an abnormal pattern of muscle function involving the face, mouth, tongue or airway.

    Children with OMDs may experience difficulties with:

    • speech
    • feeding
    • swallowing
    • sleep
    • breathing
    • dental development
    • facial growth.

    In many cases, these difficulties are linked to chronic mouth breathing.

    Signs your child may have an Orofacial Myofunctional Disorder

    Breathing and sleep signs

    • mouth open at rest
    • mouth breathing during the day
    • snoring
    • noisy breathing
    • restless sleep
    • frequent waking
    • dark circles under the eyes
    • chronic congestion
    • fatigue despite a full night’s sleep.

    Speech signs

    • lisping
    • unclear speech
    • distorted speech sounds
    • difficulty producing certain sounds
    • persistent articulation difficulties
    • reduced speech intelligibility.

    Feeding and swallowing signs

    • picky eating
    • messy eating
    • food remaining in the cheeks
    • gagging easily
    • difficulty chewing
    • long mealtimes
    • tongue thrust swallowing.

    Facial and dental signs

    • narrow palate
    • crowded teeth
    • open bite
    • overbite
    • underbite
    • long face appearance
    • receding chin
    • poor lip seal.

    If several of these signs sound familiar, a comprehensive assessment may be worthwhile.

    Why does mouth breathing matter?

    Many parents assume mouth breathing is simply a habit.

    In reality, mouth breathing is often a symptom that something is preventing efficient nasal breathing.

    Common causes include:

    • enlarged tonsils
    • enlarged adenoids
    • allergies
    • chronic nasal congestion
    • recurrent infections
    • structural airway differences
    • tongue tie
    • prolonged dummy use
    • thumb sucking
    • poor oral posture.

    When nasal breathing becomes difficult, children naturally begin breathing through their mouths.

    Over time, this can affect how the face, jaws and airway develop.

    What does healthy oral posture look like?

    Healthy oral posture is surprisingly simple:

    • lips
      • gently closed
    • tongue
      • resting against the roof of the mouth
    • teeth
      • slightly apart
    • breathing
      • through the nose.

    This posture helps guide healthy jaw growth, facial development and airway formation.

    Think of the tongue as a natural orthodontic support system. When it rests in the correct position, it helps shape the upper jaw and supports healthy facial growth.

    The consequences of chronic mouth breathing

    1. Speech difficulties

    Children who breathe through their mouths often have altered tongue posture and reduced oral stability.

    This can contribute to:

    • lisping
    • distorted sounds
    • reduced speech clarity
    • difficulty learning new speech sounds.

    2. Feeding and swallowing difficulties

    A low tongue posture may affect:

    • chewing efficiency
    • swallowing patterns
    • food management
    • oral motor coordination.

    Many children develop a tongue thrust swallow, where the tongue pushes forward instead of moving efficiently during swallowing.

    3. Poor sleep quality

    Mouth breathing can contribute to:

    • snoring
    • restless sleep
    • frequent waking
    • daytime fatigue
    • reduced concentration.

    Poor sleep can have a significant impact on learning, behaviour and emotional regulation.

    4. Changes to facial growth

    Over time, chronic mouth breathing may influence:

    • jaw development
    • facial proportions
    • dental alignment
    • airway size.

    This can result in:

    • narrow palates
    • crowded teeth
    • long facial appearance
    • increased orthodontic needs.

    5. Oral health concerns

    The nose acts as a natural filter and humidifier.

    When children breathe through their mouths:

    • The mouth becomes dry.
    • Saliva protection is reduced.
    • Risk of tooth decay increases.
    • Gum health may be affected.

    Why this matters for speech therapy

    Speech does not develop in isolation.

    The tongue, lips, jaw and airway work together to support clear communication.

    At London Speech and Feeding, we look beyond speech sounds alone.

    A child who presents with:

    • persistent speech difficulties
    • lisping
    • feeding challenges
    • open mouth posture
    • snoring
    • poor sleep

    may benefit from an assessment that explores underlying orofacial myofunctional factors.

    Addressing these foundations can often support more effective progress in speech and feeding therapy.

    How London Speech and Feeding can help

    A comprehensive assessment may include observation of:

    • breathing patterns
    • lip posture
    • tongue posture
    • swallowing function
    • feeding skills
    • speech sound development
    • sleep concerns
    • oral structures.

    Where appropriate, recommendations may include:

    • orofacial myofunctional therapy
    • speech therapy
    • feeding therapy
    • home programmes
    • ENT referral
    • orthodontic referral
    • collaborative multidisciplinary support.

    The good news

    Orofacial Myofunctional Disorders are often highly treatable when identified early.

    Supporting healthy breathing, tongue posture and oral muscle function can positively influence:

    If your child regularly breathes through their mouth, snores, struggles with speech clarity or has feeding difficulties, a specialist assessment may help identify the underlying cause.

    • speech clarity
    • feeding skills
    • sleep quality
    • facial growth
    • dental development
    • overall wellbeing.

    At London Speech and Feeding, we are passionate about looking beyond symptoms and understanding the whole child. Contact me!

    Sometimes the key to clearer speech starts with a simple question:

    ‘Is my child breathing through their nose?’

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.

    Frequently Asked Questions

    Can mouth breathing cause speech problems?

    Yes. Mouth breathing can alter tongue posture, lip strength and oral stability, which may contribute to articulation difficulties and lisps.

    Should I be worried if my child snores?

    Regular snoring is not considered normal in children and may indicate airway obstruction or sleep-disordered breathing.

    Can enlarged tonsils affect speech?

    Yes. Enlarged tonsils may affect resonance, tongue positioning, swallowing and breathing patterns.

    What age can children be assessed?

    Children of all ages can be assessed if parents have concerns about speech, feeding, breathing or oral development.

    What is Orofacial Myofunctional Therapy?

    Orofacial Myofunctional Therapy focuses on improving breathing patterns, tongue posture, lip seal and oral muscle function to support overall health and development.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • One book, dozens of therapy opportunities: What speech therapy really looks like

    As speech and language therapists, some of the most effective moments in therapy don’t come from flashcards, worksheets, or even drilling sounds (though to be fair I do drill quite a lot too! needs must…😊).

    By and large they happen in natural interaction — during shared attention, laughter, storytelling, and connection.

    This short video clip captures that.

    In under two minutes, while simply reading a book together with a three-year-old child, we naturally work on:

    • Speech sounds
    • Vowel production
    • Early phonological patterns
    • Motor planning
    • Signing and total communication
    • Visual cueing
    • Repetition and practice
    • Confidence building
    • And engagement through play

    To many people, it may just look like ‘reading a book’.

    But underneath that moment are years of specialist training, clinical decision-making, preparation, and therapeutic skill.

    Therapy hidden inside play

    One of the most important parts of paediatric speech therapy is knowing how to embed targets into meaningful interaction.

    Books are one of my favourite therapy tools! Why: because as speech therapists we need to prepare for our child and our sessions. And having a book gives me the structure to know beforehand what kind of sounds or words might be coming up. Then I can be prepared for providing extra support for them. As you can see in this clip, I had the sound cards just there because I had anticipated what might be coming up!

    A single story can provide opportunities for:

    • Speech sound practice
    • Vocabulary development
    • Sentence building
    • Turn-taking
    • Symbolic understanding
    • Attention and listening
    • Gesture and signing
    • Motor speech cueing
    • And social communication

    In this clip, I follow my little one’s interests while carefully weaving in her individual therapy targets.

    It looks relaxed and spontaneous — and it is — but it is also highly intentional.

    Catching opportunities in the moment

    One lovely example in the clip is when she says ‘yes’.

    She is now starting to say the final /S/ sound, so I immediately model and draw attention to it using the ‘snake sound’ visual cue, giving her positive feedback that she can now also try using this sound at the start of words.

    My gently shaping the word ‘yeSSSS.’ gives her:

    • Auditory feedback
    • Visual support
    • And an achievable opportunity to try again

    A few seconds later, we naturally practise it again.

    That’s responsive therapy.

    Speech therapists are constantly listening, analysing, adapting, and deciding:

    • When should I model?
    • When should I pause?
    • When should I repeat?
    • When should I let it go?
    • How can I keep confidence high while still targeting speech?

    These decisions happen in seconds.

    Working on speech without ‘stopping the play’

    Another moment in the clip focuses on the word ‘out’, where the vowel sound is one of her speech targets.

    Then we move into practising the word ‘open’, a word she has previously found difficult.

    Within this one word, we can support:

    • Sequencing
    • Motor planning
    • Lip shape
    • Vowel production
    • And speech sound accuracy

    We also briefly practise the /K/ sound — a sound produced at the back of the mouth which can be particularly tricky to produce.

    Instead of explaining it verbally (which is often too abstract for young children), I use:

    • Visual demonstration
    • Exaggerated mouth movements
    • Gesture/sign support
    • And playful modelling

    Children learn through seeing, hearing, doing, and experiencing.

    That is why Speech Therapists use multiple layers of cueing simultaneously.

    Why I use signs alongside speech

    Throughout the clip, I also use signs such as ‘book’ and ‘pig’.

    Using signs does not stop children talking.

    In fact, for many children, signs:

    • Reduce frustration
    • Support understanding
    • Increase participation
    • Reinforce vocabulary
    • And help bridge the gap while speech is developing

    Communication always comes first.

    Speech is only one part of communication.

    When children feel successful communicating, they are far more likely to keep trying.

    The skill behind ‘natural’ therapy

    One thing I often hear from parents is:

    ‘You make it look so easy.’

    That is actually one of the biggest compliments a therapist can receive. (Though we also often feel we need to justify our very existence with these thoughts because we don’t just play/just read but we know it can look like that!) 😊 this is the reason for this blog…

    High-quality paediatric therapy should feel warm, playful, responsive, and natural.

    But underneath that natural interaction is:

    • Clinical knowledge
    • Phonological analysis
    • Motor speech understanding
    • Language development expertise
    • Sensory awareness
    • Relationship-building
    • And careful session planning

    Before this session even began, I already knew:

    • Which speech patterns to target
    • Which words would likely appear in the book
    • What visual cues might help
    • Which signs to model
    • And how to adapt depending on the child’s responses

    That preparation allows therapy to stay child-led without losing therapeutic focus.

    Following the child while leading the therapy

    The best therapy is rarely rigid.

    Children do not learn communication through pressure or endless correction. They learn through interaction.

    That is exactly what this short clip demonstrates.

    One book.
    One conversation.
    Hundreds of tiny therapeutic decisions.

    And all within a joyful moment shared together.

    Because good speech therapy should never feel like hard work for a child.

    It should feel like connection, confidence, success — and fun.

    If you’re concerned about your child’s speech and language or wondering whether they might benefit from speech therapy, feel free to get in touch.

    Sonja McGeachie

    Highly Specialist Speech and Language Therapist

    Owner of The London Speech and Feeding Practice.


    Health Professions Council registered
    Royal College of Speech & Language Therapists Member
    Member of ASLTIP

    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    3
  • · ·

    LAMP Words for Life: A revolutionary AAC system

    Introduction

    When working with non-speaking or minimally speaking children the LAMP Words for Life AAC (Augmentative and Alternative Communication) system is my absolute go-to every time. For me it stands out as a revolutionary system that has transformed the lives of many of my non-speaking students. LAMP Words for Life is a ROBUST, comprehensive language-based AAC system and it is designed to help any user to express their thoughts, feelings, and needs effectively, thereby achieving maximal independence in their daily life. A winner!

    There is a whole host of AAC apps and systems out there and each has their own advantages and benefits for sure. I have tried a good number of other systems. I do also like certain features of other AAC systems for sure. For example GRID: I love the versatility of GRID and the ease of editing the system is fantastic.

    Why I think it works so well

    However, strangely I always return to LAMP when push comes to shove. I have thought very carefully about it and so here are my thoughts on why this is and why it works so well:

    1. Intuitive interface: LAMP Words for Life features are for me really user-friendly and it is easy to navigate and understand (this is very important for non-techy people). I think it makes sense and it is accessible to users of all ages and abilities. Yes the pictures are a little bit different to other symbol systems we use, especially here in the UK to be sure, and this is one of the reasons why it is good to have a variety of systems available, so that we can cater for students who are used to other symbols or do very well with specific symbol core boards. I have learned though that the pictures are not that important when using LAMP because the entire system is based on MOTOR PLANNING. And once one knows the motor plan to find a picture it is in our brain and we do not look at the picture any more. So, the motor plan to find a word is much more important when using LAMP than worrying about what the picture looks like.
    2. Comprehensive vocabulary: The system offers a vast vocabulary of words and phrases, covering a wide range of topics and contexts. This enables users to express themselves effectively on a variety of subjects. That said, almost every time I use LAMP there is a little word I need and it’s not on there. But that’s not a problem: for example, I was looking for ‘sunglasses’ the other day. Sure, there is ‘sun’ and ‘glasses’ but that would be two separate motor plans and for my student that would be too many for now, so it was very easy to quickly add the new word ‘sunglasses’ under ‘accessories’ or ‘beach wear’ — I added it within less than one minute. Likewise, there are a ton of words which cater for the US market, and I tend to change them to fit the UK vocabulary like ‘nappy’ for ‘diaper’. Or I delete them entirely if I feel my child will never need to use a certain word like ‘conference’ or ‘nun’. PS: should they get to a point of using the system as an adult independently then these words can surely be added again, or if my student ever moves to the US then the words can be changed back to US terms again without any problem.
    3. Grammar support: LAMP provides built-in grammar support, helping users construct grammatically correct sentences. This can be particularly beneficial for individuals with language processing difficulties. But what I love about the way LAMP is organised here is that, in contrast with other systems I have used, it does not PREDICT what you want to say, it lets the user decide and find the right grammatical structure. I appreciate this because, just like I hate my phone or email offering predictive text or offer corrections to my words, I really do not get the systems that offer automatically a grammar change which mostly I don’t want. Where that is the case, I am often confused and hindered in finding the correct wording. I love the simplicity of LAMP and at the same the complexity that can be achieved gradually with practice. LAMP is fully designed to enable a user to build up not only vocabulary but a full language system. On a course recently I was able to hear adult LAMP users speaking to the audience in full and quick grammatically well-rounded sentences on a host of topics.
    4. Customisation: LAMP can be customised to meet the individual needs of each user. This includes options for adjusting the vocabulary, layout, and accessibility features. It is not as easy to edit as GRID I will say and that can cause me a little bit of frustration at times, but on balance I still vastly prefer the system as a whole. It can also be customised quite well for Gestalt Language Processors. It takes a little bit of practice and thinking about how best to do this but I have found a way that works well which I demonstrate in the short video clip.
    5. Community support: LAMP Words for Life has a thriving community of users on Facebook and this is so valuable and inspiring. Therapists and families of LAMP users alike share experiences, provide resources, and offer encouragement. This can be a valuable source of support for both users and their families.
    6. Comprehensive support: LAMP Words for Life offers quick and thorough support services, including training, resources, and ongoing assistance. This is invaluable and reassuring for both users and caregivers.
    7. Research-based: The development of LAMP Words for Life is based on extensive research and evidence-based practices. This ensures that the system is grounded in sound scientific principles.

    Conclusion

    To conclude LAMP Words for Life is a powerful AAC which provides us with a means of effective communication, language development, and social interaction. Whether you are a parent of a non-speaking child or a speech therapist looking for innovative AAC solutions, LAMP Words for Life is worth exploring.

    Example on how to use AAC at story time

    Feel free to contact me if you need help with your child.

    Sonja McGeachie

    Early Intervention Speech and Language Therapist

    Feeding and Dysphagia (Swallowing) Specialist The London Speech and Feeding Practice

    The London Speech and Feeding Practice


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1
  • Learn the benefits of Cycles Phonology Approach in Speech Therapy

    A grey, green and orange circle overlaid with Cycles Phonological Approach
    Cycles Phonogogical approach

    When your child attends Speech and Language Therapy, it can look like your child’s therapist is playing. Therapy needs to be fun, which means carrying out therapy through the medium of play. But remember every approach used has evidence behind it. We need to know that therapy will be successful, so an evidence-based approach is essential.

    One of the approaches used for Speech Therapy (i.e., working on speech sound production) is the Cycles Phonology Approach. This approach focuses on the patterns and processes rather than each individual sound. For example, it may be working on final consonant deletion, so the omission of the final sound in words. As Speech and Language Therapists we understand that children can get frustrated and fatigued working on the same sound every day. This approach attempts to solve that. Hodson suggests, the approach is also useful for children with more speech sound errors, as therapists see progress in areas not targeted.

    How does the Cycles Phonology Approach work?

    Your Speech and Language Therapist will assess your child’s speech development and will then analyse the results. They will also look for which sounds they can produce with support (this is called stimulability). They will analyse patterns in the results and will formulate a plan.

    The Cycles Phonology Approach intervention allows your child to work in blocks. This might mean they work for half a week for 30 minutes on (e.g., clusters). Then the next half they’ll work for 30 minutes on a different process (e.g., omission of sounds at the end of words).

    Research has found that the following error patterns respond well to this approach:

    • Syllables (identifying the different parts in a word e.g., “ae-ro-plane”)
    • Final Consonant deletion (omission of the final sound e.g., “ca” instead of “cat”)
    • Initial consonant deletion (omission of the first sound e.g., “at” instead of “cat”)
    • Fronting (instead of making a sound at the back of the mouth, it’s made at the front e.g., “tat” instead of “cat”)
    • Backing (instead of making a sound at the front of the mouth, it’s made at the back e.g., “gun” instead of “bun”)
    • S blends (e.g., “sl, sm, sn, sk, sw”)
    • Gliding of liquids (e.g., “lellow instead of yellow”, “wabbit instead of rabbit”)

    What does a Speech and Language Therapy session look like when using the Phonology Cycles Approach?

    The format of the session remains the same for whichever speech sound pattern your child is working on. Your child’s Speech and Language Therapist will review the previous session. Then they will use an activity to work on your child hearing the sound several times (this is called ‘auditory bombardment’). Then your child will practise saying the sound. Next, the Speech and Language Therapist will check if your child can say any of the sounds which they haven’t been able to produce before, with support. This is called a stimulability check. After this, your child will take part in an activity which builds their awareness of sounds in words (such as a rhyming or syllable activity). The session will finish with another auditory bombardment task (i.e., hearing their tricky sound repeatedly).

    I will give you advice for practising at home, as it’s vital that your child learns in the correct way. We aim for 100 turns in therapy sessions, so it’s vital your child is motivated.

    Contact me to improve your child’s speech sounds and improve their confidence when talking.


    Find a speech and language therapist for your child in London. Are you concerned about your child’s speech, feeding or communication skills and don’t know where to turn? Please contact me and we can discuss how I can help you or visit my services page.

    1